# Payerset - Full Content Export > Payerset is a healthcare price transparency data company. We turn payer > Transparency in Coverage (TiC) files and Hospital Price Transparency > machine-readable files (MRFs) into clean, analyzable contracted-rate and claims > data so health systems, providers, health-tech teams, employers, and researchers > can benchmark reimbursement, prepare for managed care contract negotiations, and > understand competitive rates in their market. This file (llms-full.txt) is a full-text export of Payerset's reference material and articles, intended for AI and retrieval engines. For a curated index of the site, see https://payerset.com/llms.txt. Content is generated from the live site and updated on every deploy. --- # Glossary ## Allowed Amount The allowed amount (or allowed charge) is the maximum dollar amount a health plan considers payable for a covered service. For in-network care it equals the plan's negotiated rate; for out-of-network care it is a plan-determined amount. The allowed amount, not the provider's list price, is the basis for calculating plan payment and patient cost-sharing. ## Billing Code A billing code is a standardized identifier for a medical service, procedure, drug, or supply used on healthcare claims and in price transparency files. Common code systems include CPT, HCPCS, ICD-10, DRG, and NDC. Negotiated rates in machine-readable files are reported per billing code, which is why accurate code mapping is essential to comparing rates. ## CPT and HCPCS Codes Current Procedural Terminology (CPT) codes, maintained by the American Medical Association, describe medical, surgical, and diagnostic services. The Healthcare Common Procedure Coding System (HCPCS) extends CPT to cover items such as drugs, supplies, and equipment. Together they are the primary code sets used to report and price professional and outpatient services. ## Diagnosis-Related Group (DRG) A Diagnosis-Related Group (DRG) is a classification that groups inpatient hospital stays with similar clinical characteristics and resource use into a single payment category. Payers often reimburse inpatient care as a fixed amount per DRG rather than per individual service, making DRG-based rates a key benchmark for hospital inpatient contracting. ## Hospital Price Transparency Hospital Price Transparency is a U.S. federal rule, effective January 1, 2021, that requires every hospital to publish a machine-readable file of standard charges (gross charges, discounted cash prices, and payer-specific negotiated rates) along with a consumer-friendly display of shoppable services. CMS has progressively strengthened the required file format and enforcement. ## In-Network Rate An in-network rate is the price a health plan and a provider have contractually agreed to for a covered service when the provider participates in the plan's network. In-network rates are typically lower than a provider's billed charges and are disclosed in Transparency in Coverage machine-readable files. ## Machine-Readable File (MRF) A machine-readable file (MRF) is a structured data file, usually JSON or CSV, that payers and hospitals publish to comply with price transparency rules. MRFs list negotiated rates by payer, provider, and billing code. Their large size, inconsistent schemas, and data-quality issues make them difficult to analyze without significant normalization and enrichment. ## Negotiated Rate A negotiated rate is the dollar amount a health plan and a healthcare provider have agreed to as payment for a specific covered service. These rates were historically confidential but are now disclosed under federal price transparency rules, forming the basis for reimbursement benchmarking and managed care contract negotiations. ## National Provider Identifier (NPI) A National Provider Identifier (NPI) is a unique 10-digit number assigned to U.S. healthcare providers, both individuals and organizations, by CMS. NPIs identify which providers a negotiated rate applies to in machine-readable files, making them essential for linking rates to specific physicians, facilities, and health systems. ## Out-of-Network Rate An out-of-network rate refers to the amounts payers report for care delivered by providers outside their contracted network. Under Transparency in Coverage, plans publish historical out-of-network allowed amounts and billed charges, which help reveal payment patterns where no negotiated contract exists. ## Payer A payer is an organization, typically a health insurance company, group health plan, or third-party administrator (TPA), that finances or reimburses the cost of healthcare services. Payers negotiate rates with providers and are required to publish those rates under the Transparency in Coverage rule. ## Reimbursement Benchmarking Reimbursement benchmarking is the practice of comparing a provider's negotiated rates against those of peers and competitors across payers, services, and geographies. Using price transparency data, organizations benchmark rates to see where they stand, identify underpaid services, and build evidence for contract negotiations. ## Taxpayer Identification Number (TIN) A Taxpayer Identification Number (TIN) is the IRS-issued number that identifies the business entity billing for healthcare services. In price transparency files, TINs help associate negotiated rates with the organization (such as a medical group or hospital) that holds the payer contract, complementing the provider-level NPI. ## Transparency in Coverage (TiC) Transparency in Coverage (TiC) is a U.S. federal rule requiring health insurers and group health plans to publish their in-network negotiated rates and out-of-network allowed amounts as machine-readable files, updated monthly. Effective for plan years beginning in 2022, TiC files cover nearly every commercial plan and are the most comprehensive public source of payer rate data. --- # The Price Transparency Project - Articles --- ## Verification Has Replaced Belief: What Self-Funded Employers Can Now Check, and What Happens When They Do - URL: https://payerset.com/pricetransparencyproject/blog/verification-has-replaced-belief/ - Published: September 15, 2026 - Author: Andrew Gordon - Section: The Price Transparency Project Self-funded employers are opening renewal letters that would have been unthinkable a few years ago. One mid-sized employer's plan came back at a 39 percent increase. Another absorbed years of single digit increases, then a 33 percent year, and then a 100 percent increase on its PPO plan. At that scale, an employer starts asking what the plan is even paying for (and to whom). ![Renewal increases three self-funded employers reported: 39 percent, 33 percent, and 100 percent on a PPO plan](/images/blog/verification-has-replaced-belief/renewal-shock.jpg) For most of the last two decades that question had no answer an employer could check. If a broker said the network discount was good, it was up to the employer to decide whether to believe it, and the conversation ended there. The negotiated rates behind the discount are now published, and so is what the plan's vendors are paid. **Verification has replaced belief as the starting point**. ![What an employer can now check: network rates, what vendors earn, and the plan's own claims, each with what was available before and what is published now](/images/blog/verification-has-replaced-belief/what-you-can-check.jpg) ## Where the cost is going Hospitals have two payers of consequence, government and employers, and the government side is shrinking. One physician who runs a direct care practice put the arithmetic plainly. Federal reconciliation has cut what Medicaid pays. He cited the Congressional Budget Office estimate of roughly $321 billion in reduced Medicaid reimbursement and expects the realized figure to run higher. Enhanced exchange subsidies are ending, and on his numbers roughly eight million more people become uninsured, arriving at hospitals through emergency departments without the benefit of preventive care. Hospitals absorbing that population are looking for ways to recover the difference, and commercial contracts are one of the few places left to do so. **Employers will see the result in renewal cycles they are not party to negotiating.** ## The discount, checked against the files Some of this is observable before it reaches a renewal letter. Under the Transparency in Coverage rule, payers publish machine readable files carrying their negotiated rates by payer, plan, provider, and billing code, refreshed monthly. These are public datasets, which means the rate a health system charges a competitor's plan is no longer private information. Changes to commercial rates appear in those files as they are refreshed, so an employer watching the systems in its own footprint can see movement before a renewal letter arrives. What that looks like in practice is a single chart. Take one market, one large commercial payer, and one common procedure. In Phoenix, UnitedHealthcare's published files carry what it has agreed to pay each of the large hospital systems for a hip or knee replacement without major complications, and those rates can be lined up as a multiple of what Medicare pays the same hospital for the same admission. ![UnitedHealthcare's negotiated inpatient rate for MS-DRG 470 at four Phoenix hospital systems, as a percent of each hospital's Medicare payment: Abrazo Central 135 percent, HonorHealth Scottsdale Shea 220 percent, Dignity Health St. Joseph's 250 percent, Banner University Medical Center Phoenix 284 percent](/images/blog/verification-has-replaced-belief/phoenix-knee-rates.jpg) **The spread between the lowest and highest system in a single market is the number an employer never sees on a renewal letter.** In Phoenix, the same admission under the same network pays about $25,200 at Abrazo Central and about $54,800 at Banner University Medical Center, 135 percent of Medicare at one end and 284 percent at the other. The network discount is presented as one figure. The rates behind it vary by facility, and an employer whose members concentrate at the most expensive system is paying for that concentration whether or not anyone has shown them the chart. One advisor has a question for the industry that grew up without that chart.
When did the industry become faith-based?A benefits advisor
Transparency in Coverage files and hospital price transparency files changed the terms of that conversation. The underlying rates are published, so an employer can compare what a network pays a given facility against what a direct contract offer puts on the table before signing anything. **The employers who made a move describe a year of diligence, line by line contract review, and questions put to every vendor involved in the plan.** ## What the plan's vendors earn The same instinct to verify is showing up in how employers handle what their brokers and vendors are paid. The compensation disclosures that make this possible exist because the Consolidated Appropriations Act of 2021 required brokers and consultants to disclose direct and indirect compensation to plan fiduciaries. [1] One advisor estimates that a large majority of the disclosures his firm reviews are not clear enough to be useful, because they describe how a fee is calculated without ever stating the dollar amount. Another puts the standard plainly.
A disclosure of a methodology is not a disclosure. A disclosure of an amount is.A benefits advisor, on broker compensation
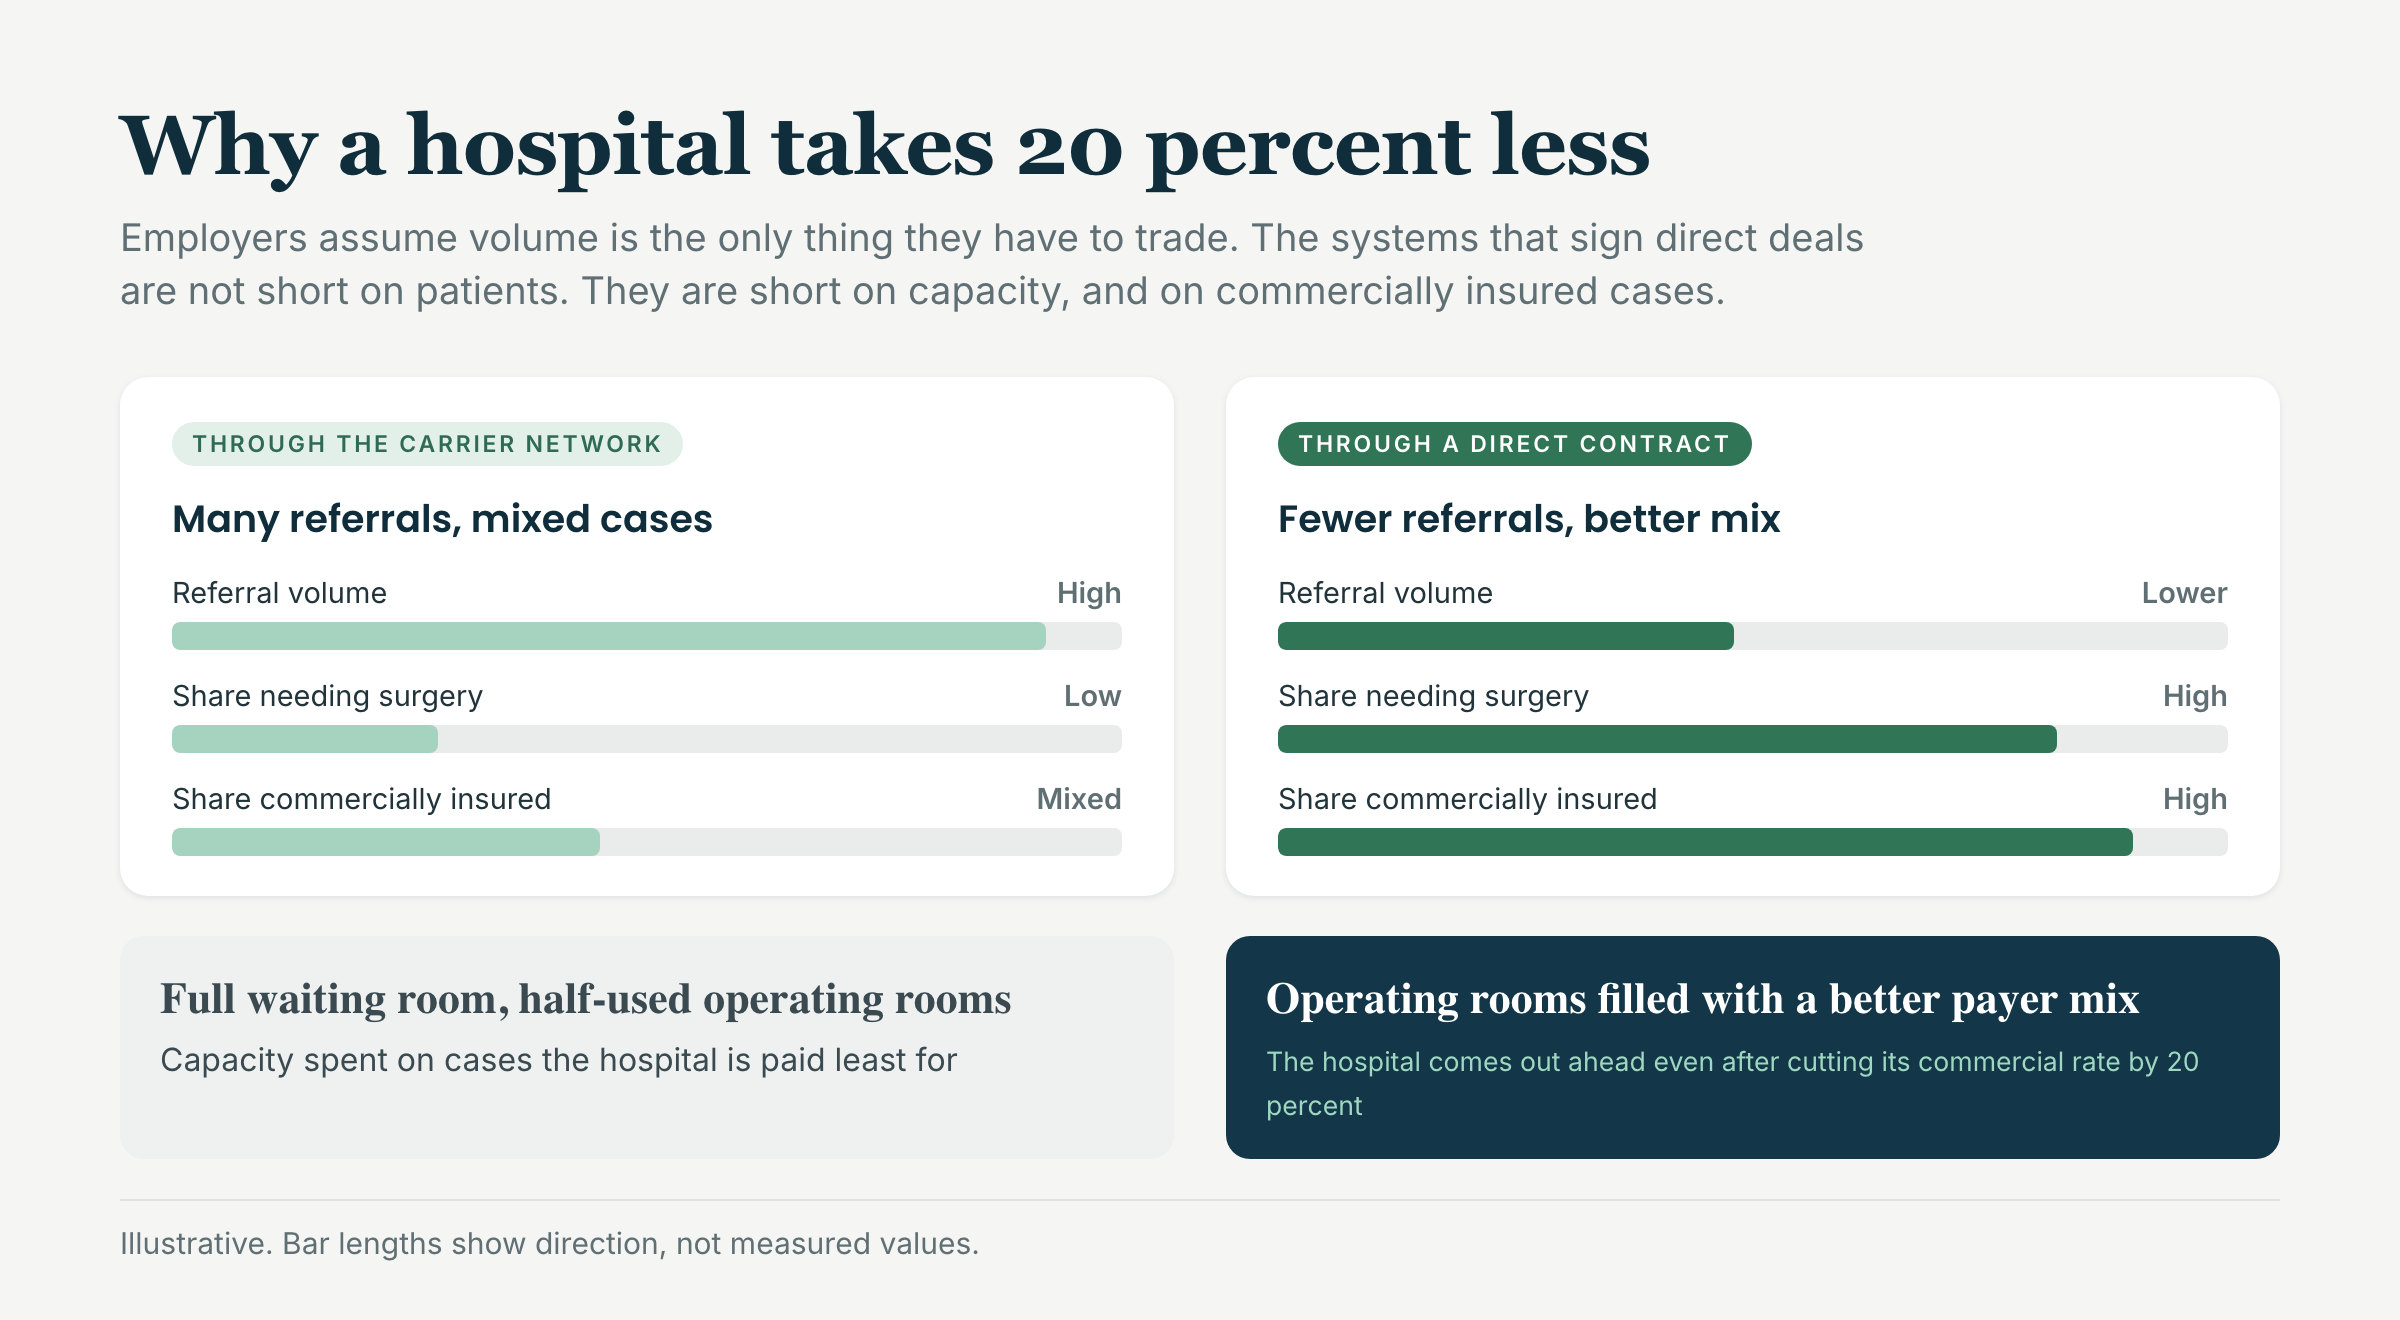
He described taking over a plan and finding an arrangement that paid the brokerage firm $8 for every prescription filled. On a plan filling 50,000 prescriptions a year, that came to $400,000 a year in compensation the employer had never been told about. ![Eight dollars per prescription, multiplied by fifty thousand prescriptions a year, is four hundred thousand dollars a year the employer had never been told about](/images/blog/verification-has-replaced-belief/disclosure-math.jpg) Federal rules moved further in the same direction this year. Fee disclosure obligations under ERISA now extend to entities providing pharmacy benefit management services, and rebates have to be passed through to the plan. [2] A proposed Department of Labor rule would require those entities to disclose direct and indirect compensation to plan fiduciaries before a contract is signed, with audit rights attached, though it has not been finalized. [3] A wave of fiduciary lawsuits against large plan sponsors over pharmacy spending has made the stakes concrete. **For a plan sponsor, the practical effect is that asking what a vendor earns is a fiduciary obligation.** ## What verification makes possible Direct contracting means an employer, or a plan acting on its behalf, negotiates rates straight with a hospital or physician group instead of accepting the rates a carrier has already agreed to inside its network. Until recently that took the staff and administrative capacity of a very large employer. Advisors are now assembling networks of directly contracted clinicians for mid-sized clients, and plans built on this model are signing hospital agreements market by market, including in smaller markets that have never had a direct contracting option. Why would a hospital agree to a lower rate? Because employers often assume patient volume is the only thing they have to trade. One direct care organization's first hospital system partner agreed to cut its negotiated commercial rates by 20 percent, knowing the arrangement would send that hospital fewer referrals overall. ![Why a hospital accepts a lower direct-contract rate: fewer referrals, but a higher share of them surgical and commercially insured, so operating rooms fill with a better payer mix](/images/blog/verification-has-replaced-belief/hospital-math.jpg) **The trade works because these systems are not short on patient demand.** They are constrained on capacity, and on the share of their patients who carry commercial insurance. If a direct arrangement sends a smaller number of referrals but a higher share of them arrive needing surgery and covered commercially, the hospital fills its operating rooms with a more favorable payer mix and can come out ahead even after the rate reduction. ## One district's numbers What this looks like from inside a plan is easiest to see in one employer's numbers. Under the same 2021 law, plan sponsors can no longer be bound by gag clauses that block access to their own claims and cost data, and every plan has to attest each year that it is not. [4] That is the legal footing for what one school district found. The superintendent of a Wisconsin high school district described what changed once he had his own claims data. Moving to a self-funded structure dropped his plan's maximum liability by $333,000 before a single claim was filed. He returned about half of that to employees through plan design, and they noticed the benefit in their paychecks and at the point of care. The other half went back into the district. ![A Wisconsin school district after moving to self-funding: maximum liability down $333,000 before the first claim, half returned to employees, and the discovery that five percent of members drive sixty percent of cost](/images/blog/verification-has-replaced-belief/district-case.jpg) What changed underneath was visibility. He found that five percent of his members drive about 60 percent of his cost, a distribution nobody had ever shown him. He now watches pharmacy trend month to month. None of that was available to him under a fully insured arrangement, and both findings let him tailor the plan to his population and his bottom line. He took ownership of his own claims data first, checked what it showed against what he had been told, and acted on the difference. ## Questions to bring to your next renewal The employers who rebuilt did not start with a vendor change. They started with questions. These are the ones that come up most. 1. **Do we have our claims data, and can we get it in a form we can analyze?** Your plan's gag clause attestation says you are entitled to it. Ask your carrier or third party administrator for the file, not a dashboard. 2. **What does every party in our plan earn, in dollars?** Ask brokers, consultants, and pharmacy benefit managers for the amount, not the formula. A per-script or per-member fee should be multiplied out. 3. **What does our network actually pay the five facilities where our members go most?** The negotiated rates are public. Ask for them as a multiple of Medicare so they can be compared across systems and against any direct offer. 4. **Which of our members drive most of our spend, and what are they being treated for?** A small share of members usually accounts for most of the cost, and plan design should be built around them. 5. **Is a direct arrangement available in our market, and at what rate?** Direct contracting has moved down market. If a hospital or physician group will contract directly, the transparency files tell you whether the offer is a discount to what the network already pays. ## Notes 1. U.S. Department of Labor, Employee Benefits Security Administration. Field Assistance Bulletin 2021-03: Group health plan service provider disclosures under ERISA section 408(b)(2)(B). December 30, 2021. 2. Risk Strategies. PBM Reform: Recent Developments Under the CAA 2026 and DOL Proposed Rule. 2026. 3. U.S. Department of Labor, Employee Benefits Security Administration. Improving Transparency into Pharmacy Benefit Manager Fee Disclosure, proposed rule. 91 Fed. Reg. 4045. January 30, 2026. 4. Centers for Medicare & Medicaid Services. Gag Clause Prohibition Compliance Attestation, required annually under section 201 of the Consolidated Appropriations Act, 2021. 5. Quotations and figures attributed to employers, advisors, and physicians are as reported by the speakers at a self-insured employer and advisor summit in St. Louis, September 2, 2026, and checked against the recordings. Speakers are identified by role. The figures are the speakers' own numbers, not independent audits. --- ## Gaining Leverage by Uncovering Contract Structures - URL: https://payerset.com/pricetransparencyproject/blog/gaining-leverage-uncovering-contract-structures/ - Published: August 18, 2026 - Author: Matt Phillips, Mac Howard & Andrew Gordon - Section: The Price Transparency Project Data analysts and contracting experts understand price transparency data from opposite ends. Data teams can sift through the numbers fluently, but they don't live inside the contracts. Managed care veterans know the contract language cold but are not data analytics experts. Getting the most value out of price transparency data sits in the overlap, where a reader can pull contract logic straight out of the published data. Part one of a series on pulling contract structure out of price transparency data, starting with the inpatient DRG base rate. ## Thousands of prices. Is each one really negotiated? There are tens of thousands of billable codes in play, and working through them one at a time is not a practical use of either side's time. Both sides tend to agree instead on a structure: a small number of negotiated figures that generate thousands of published prices. Three common structures show up time and again: 1. Inpatient DRG base rate 2. Clinical Laboratory Fee Schedule (CLFS) multiplier 3. Outpatient surgical groupers Let's start by breaking down the base rate. We'll concentrate on hospital services, specifically inpatient care, but the principles apply more broadly.


Terminology
Diagnosis-related group (DRG) The code that describes an entire inpatient stay. Rather than pricing each service delivered during an admission, hospital inpatient billing rolls the whole stay into one MS-DRG that reflects the diagnosis, the major procedure, and whether complications were present. There are roughly 770 in the current CMS list.
DRG weight A number CMS assigns to each MS-DRG reflecting the resources a stay is expected to consume relative to other stays. A stay weighted 2.0 is expected to take roughly twice the resources of a stay weighted 1.0. Published annually in Table 5 of the inpatient prospective payment system final rule and identical for every hospital.
Base rate A single negotiated dollar amount that large portions of published rates are built off of. Payment is the base rate multiplied by the DRG weight, so a published rate divided by its weight backs into the base rate.
Case rate One payment covering an entire episode rather than each line item on the claim. An inpatient DRG payment is a case rate that scales with the weight, which is what distinguishes it from a flat rate.
Carve-out A service pulled out of the base rate grid and priced on its own terms, such as a transplant, a burn admission, or a specific set of orthopedic procedures.
## What a DRG prices For each MS-DRG, CMS assigns a relative weight to the code. Each fiscal year, CMS republishes the full list in Table 5 of the Inpatient Prospective Payment System final rule, which anyone can download directly from CMS. The weight is not a price and not a score on a fixed scale. It states expected resource use relative to other stays, so a stay weighted 2.0 is expected to consume roughly twice what a stay weighted 1.0 consumes. The same procedure appears at several weights depending on severity, which is what the abbreviations in a DRG title record. A major complication or comorbidity (MCC) carries the highest weight, a complication or comorbidity (CC) carries a lower one, and a stay without either carries the lowest. Spinal fusion runs across all three. The weights are public, and they are the same for every hospital in the country. Medicare applies locality adjustments to the payment, after the weight, not to the weight itself. So when a commercial contract is built on these weights, payments may differ, but benchmarking becomes a practical exercise. ## The base rate behind published prices Because the weights are fixed and public, oftentimes much of the published rates can be traced back to one number. The payer and the hospital agree on a base rate across a bucket of DRGs, and within that bucket each price follows from it: **published rate equals the base rate multiplied by the DRG weight.** That one figure can price a lot of the inpatient grid. A hospital with a $22,568 base rate collects $22,568 for a stay weighted 1.0, about $45,000 for a stay weighted 2.0, and about $479,000 for a stay weighted 21.2. Rather than settling hundreds of prices one at a time, both sides settle the base rate and the published weights do the rest. How a payer arrives at a particular base rate reflects the hospital's service mix, claims volume, and whatever has happened for potentially decades at the negotiation table. The current number is an adjustment to one that has been carried forward through contract cycles for years. Why does this matter? Price transparency data has *a lot* of information. Hospital A vs. Hospital B's prices will always differ. But where the specific areas for leverage in benchmarking sit is what matters. Breaking down the variations into rates tied to a single base rate, and then additional potential leverage points that sit outside this structure, can help focus a negotiation strategy. ## An example of base rates in transparency data Let's walk through a real example. Take a large general acute care hospital in Chicago and one payer: Aetna. To hold the comparison steady, we'll anchor to a single Aetna PPO plan, since different plans under the same payer can carry different negotiated terms even at the same facility. If we pull their rates and look at a handful of DRGs, no major surprises. Each of these reads as its own negotiated number. Nothing in the file tells you whether it was priced on its own or actually maps back to a consistent, underlying structure: a single base rate. | MS-DRG | Description | Negotiated Rate | | :----- | :---------- | --------------: | | 470 | Major hip and knee joint replacement or reattachment of lower extremity without MCC | $33,775 | | 871 | Septicemia or severe sepsis without MV >96 hours with MCC | $34,013.20 | | 291 | Heart Failure & Shock w MCC | $22,479.30 | | 193 | Simple pneumonia and pleurisy with MCC | $23,015.10 | To find out, we can map each of these published rates and billing codes to their CMS relative weight. We can then divide each published rate by the DRG's CMS relative weight: | MS-DRG | Negotiated Rate | CMS Weight | Implied Base Rate | | :----- | --------------: | ---------: | ----------------: | | 470 | $33,775 | 1.9289 | $17,510 | | 871 | $34,013.20 | 1.9425 | $17,510 | | 291 | $22,479.30 | 1.2838 | $17,510 | | 193 | $23,015.10 | 1.3144 | $17,510 | Looking at those same common four DRGs, each one maps to the same underlying $17,510 base rate. In fact, zoom out to the hospital's full DRG list for this plan: **94%** of all published rates divide back to that same base rate. We can now better identify which portions of our competitors' published rates fall into the base rate structure, and the remaining percentage (6% of rates in this case) are potential additional leverage points that you can use in your strategy. Oftentimes, high-cost procedures like transplants are carved out, and you will see those as different structures or in potentially different areas of the files altogether. Breaking a competitor's files down like this can help remove a lot of the noise in these large files, so you can focus on the areas that require deeper investigation and probably warrant it. We ran this same analysis for a peer academic institution within the same city and the pattern applied almost identically. **Hospital B's implied base rate was $22,675 compared to Hospital A's $17,510, a leverage point in and of itself.** ## Summary It goes without saying, but it's worth reiterating: contracts are complex, and they are unique to every payer-provider relationship. Complexity grows over decades alongside ever-changing policies. This concept is one of many that allows you to combine your real-world experience in contracting and managed care with the insights available through price transparency data. Removing noise is step one. This will really uncover a new level of insights versus cherry-picking codes or wading through a lot of noise, which we know exists in these files. In part two, we'll look at more contract structures and how they show up in the transparency data as well. --- ## Same Surgery, Different Price: Who Owns the ASC Predicts What the Payer Pays - URL: https://payerset.com/pricetransparencyproject/blog/same-surgery-different-price/ - Published: July 13, 2026 - Author: Payerset Team - Section: The Price Transparency Project In metro Atlanta, the same total knee replacement, performed in the same kind of facility, carries very different prices depending on who owns the surgery center. Across the market's freestanding ambulatory surgery centers (ASCs), the average commercial institutional (facility) reimbursement for the procedure runs about $12,200 at independently owned centers, about $15,100 at private equity owned centers, and about $21,200 at system-owned centers. The operation is identical, the type of facility is identical, and the institutional rate is measured on the same procedure. **What moves the price is ownership.** Holding the procedure and the ASC setting constant turns ownership into the variable under test. In Atlanta, the negotiated rate moves with the market power of the owner. ## The question on cost When one facility is paid more than another for the same service, the explanation offered is cost. In any industry, understanding what it costs to run an operation is difficult without being on the inside, and healthcare is no different. The usual version of that explanation points to the setting: a hospital outpatient department carries standby capacity and institutional overhead that a freestanding office does not, so it is paid more. That explanation cannot do the work here, because the setting is held constant. Every facility in this analysis is a freestanding ambulatory surgery center, billing the institutional facility rate for the same procedure. The buildings are comparable and the procedure is identical. **The difference that remains is ownership, and the question is what ownership is worth in the negotiated rate.** Site of service still sets the floor and the ceiling. The same procedure moves up a predictable ladder, from an independent office with no facility fee, to a freestanding surgery center, to a hospital outpatient department, to a full inpatient stay, with the institutional component growing at each step. **This analysis holds at one rung of that ladder, the ambulatory surgery center, and varies the owner instead.** It isolates the part of the rate that the building cannot explain. ## What determines the value A rate that tracks cost and a rate set by negotiation behave differently. When a hospital system or a private equity platform acquires an independent surgery center, the building, the staff, and the procedure can stay the same while the negotiated rate moves. What changes is the owner, and the negotiating position the owner brings to the contract. The research on consolidation points in the same direction. Vertical acquisitions of physician practices by hospitals have been associated with price increases near 14 percent for the same services. [1] Prices at facilities with no local competition run about 12 percent above markets with several rivals, after adjusting for the care provided. [2] Outpatient prices at system-affiliated facilities have historically run above independent ones. [3] In each case, what changed was market position and billing classification. **A larger owner also has more purchasing power with suppliers and a broader base to spread fixed costs across.** If the rate tracked cost, that scale should push it down. The Atlanta data moves in the other direction, with the largest owners commanding the highest rates, which is difficult to reconcile with a purely cost-based explanation. How much of the difference is margin could be measured against public cost-report data. ## The data: ownership in one market Payerset analyzed commercial institutional rates at freestanding ambulatory surgery centers in metro Atlanta for three orthopedic procedures: rotator cuff repair, billed as CPT 23410 and 23412, and total knee replacement, CPT 27447. Each center was sorted into one of three ownership categories. 1. **System centers** are owned by a large hospital system. 2. **Private equity centers** are owned by a private equity backed platform. 3. **Regional centers** are independently held, owned by a single practice or group. Across all three codes, the average rate rose in the same order: regional lowest, private equity in the middle, system-owned highest. ![Average commercial facility rates by owner type across metro Atlanta ambulatory surgery centers, for CPT 23410, 23412, and 27447](/images/blog/same-surgery-different-price/ownership-premium-chart.jpg) **The pattern is consistent across procedures, and the gap widens with the size of the bill.** On rotator cuff repair, the system average runs about 40 percent above the independent average. On total knee replacement, where the dollars are larger, the system average of about $21,200 is roughly 73 percent above the independent average of about $12,200, with the private equity average sitting between them. Each category contains named owners that a reader in this market would recognize. ![Owners and representative surgery centers represented in each ownership category: regional and independent, private equity, and health system](/images/blog/same-surgery-different-price/owners-by-category.jpg) ## How this was measured The figures are average commercial institutional rates, the facility side of the bill, with no professional or modifier components, drawn from Payerset claims and rate data across UnitedHealthcare, Aetna, and Elevance. System ownership is identifiable directly in the data. Private equity and regional ownership were confirmed through secondary research on portfolio holdings and practice records. Rates below the Medicare outpatient allowable were excluded as likely misreported professional fees, and rates above 500 percent of Medicare were excluded as likely hospital rates misattributed to surgery centers. Claims data was used to identify Atlanta as a strong market for the analysis and to confirm that the selected procedures are ones these surgery centers bill, so the comparison reflects services performed at each facility. ## Reading the market Two things stand out inside the averages. **The system category is not uniform, and rates within it range widely, which reflects the different market positions of the systems involved.** The private equity category contains at least one platform whose knee replacement rates approach the system level, well above the other private equity owners in the sample. Ownership type tracks the rate, and so does the scale and reach of the specific owner. When a small number of systems and platforms own most of the surgery centers in a market, the variation does not describe open competition. It describes a market where a few owners set the price, and where the procedure rate follows the market position of whoever owns the room it is performed in. [7] **The fewer the participants, the wider the possible range of outcomes, and the harder it is for an outside party to tell whether a given rate reflects the cost of care or the standing of its owner.** If the rate measured the value of the surgery, it would not change with the name on the building. The procedure is the same in all three settings. What changes is the negotiating position behind it, and the size of the gap is the distance between what the surgery is worth and what it is paid. ## What policy reaches Policy has mostly approached this through site of service. **Federal site-neutral rules, which aim to pay the same for a service regardless of where it is delivered, sit inside Medicare and address the gap between hospital and non-hospital settings.** [4] They do not reach commercial contracts, and they do not address variation among facilities of the same type. New York's Fair Pricing Act takes a different approach, capping a set of routine commercial services at 150 percent of the Medicare non-hospital rate and targeting the rate itself. [5] A Brown University analysis estimated a cap of that kind could have saved more than $1 billion in a single year across part of the state's commercial population. [6] Neither framework directly addresses the ownership-based variation visible in the Atlanta data, where every facility is already a surgery center. ## Reading the rate before the next contract For anyone benchmarking these rates, ownership is a variable to track. Two surgery centers a few miles apart, performing the same procedure, can carry rates that differ by half or more, and the difference follows who owns them. Benchmarking that accounts for ownership, alongside site of service and code, surfaces a part of the rate that a blended average will bury. **The rate a facility commands for a standard procedure can be read as a signal of its owner's market power.** It does not prove cost or position to the dollar, and the data has limits. The regional sample is small, ownership of independent centers is harder to confirm because system ownership shows up directly in the data and independent ownership does not, and a single owner's rates can swing the average in a thin category. What the data shows plainly is that in one concentrated market, for three standard procedures, the price of surgery rose with the market power of whoever owned the center. **For a team preparing for the next contract, that is the place to start.** ## Notes 1. Yale News. Hospital takeovers of physician practices drive up health care prices, study finds. August 2025. 2. Cooper, Craig, Gaynor, and Van Reenen. The Price Ain't Right? Hospital Prices and Health Spending on the Privately Insured. *Quarterly Journal of Economics*, 2019. 3. Health Care Cost Institute. Outpatient hospital prices are higher among system-affiliated, for-profit, and urban hospitals. 4. Congressional Research Service. Medicare's Site-Neutral Payment Policy. In Focus IF13233. 2026. 5. New York State Senate. Bill S705 / Assembly A2140 (Fair Pricing Act), 2025-2026. 6. Brown University, Center for Advancing Health Policy through Research. Estimating savings from the Fair Pricing Act and commercial site-neutral payment. 7. MedPAC. Hospital consolidation and its implications for Medicare. --- ## Updates to Hospital Price Transparency Requirements and the April 1st Enforcement Deadline - URL: https://payerset.com/pricetransparencyproject/blog/updates-to-hospital-price-transparency-requirements-and-the-april-1st-enforcement-deadline/ - Published: April 3, 2026 - Author: Andrew Gordon - Section: The Price Transparency Project The Price Transparency Requirements for Hospitals to Make Standard Charges Public is the CMS rule implementing Section 2718(e) of the Public Health Service Act, enacted as part of the Affordable Care Act and codified at [45 CFR Part 180](https://www.ecfr.gov/current/title-45/subtitle-A/subchapter-E/part-180). It has been updated with a meaningful set of changes. If your team works with [hospital machine-readable files](/post/making-sense-of-hospital-price-transparency-data/) for benchmarking, contract analysis, or price transparency research, these updates are in effect now and worth understanding before you draw conclusions from the data. CMS finalized a new round of updates with a January 1, 2026 effective date. Enforcement was delayed to give hospitals more time to comply. That window closes April 1, 2026. Here is what changed. For the primary source documents, see the [CMS Federal Register notice](https://www.federalregister.gov/documents/2025/11/25/2025-20907/medicare-program-hospital-outpatient-prospective-payment-and-ambulatory-surgical-center-payment) and the [CMS GitHub repository for the hospital price transparency schema](https://github.com/CMSgov/hospital-price-transparency?tab=readme-ov-file). ## From estimated amounts to actual allowed amounts The biggest structural change in version 3.0.0 of the standardized template is replacing the "estimated allowed amount" with actual dollar-based data. Under the prior framework, when a hospital's contract with a payer was expressed as a percentage of charges rather than a flat fee schedule rate, the hospital was required to publish an estimated allowed amount. Those estimates were often inconsistent, hard to validate, and varied depending on the methodology the hospital used to generate them. The new requirement is more specific. For any payer-specific negotiated charge that cannot be expressed as a single dollar amount because it is based on a percentage or formula, hospitals must now publish three figures: the median allowed amount, the 10th percentile allowed amount, and the 90th percentile allowed amount. They also have to include the total number of remittance observations used to calculate those figures. All three values must come from actual EDI 835 electronic remittance advice data, covering a lookback period of at least 12 months and no more than 15 months before the file is posted. ### Why three numbers instead of one A reasonable question when you first see this requirement is: why a distribution? If a contract says "pay 42% of charges," shouldn't the allowed amount be consistent for a given service at a given hospital? In theory, yes. In practice, the dollar output tends to vary even under a fixed percentage contract, because the charges themselves vary by encounter. Billed amounts vary because hospitals set their own chargemaster rates for each code, those rates can change over time, and the mix of services billed across claims for the same procedure is not always consistent. Add in coordination of benefits situations, secondary payer scenarios, and outlier provisions, and you end up with a distribution of outcomes rather than a single repeatable figure. The percentile structure is CMS acknowledging that reality and requiring hospitals to represent it directly rather than collapse it into a single estimate. From an analytical standpoint, the three-number format gives you more to work with than a point estimate does. A tight band between the 10th and 90th percentile suggests a relatively stable, predictable contract. A wide band signals that something more complex is happening underneath, whether that is charge variation, secondary billing patterns, or contract provisions that produce meaningfully different outcomes depending on the case. That context is helpful when you are using MRF data to benchmark or validate a rate. One definition worth keeping in mind: the "total allowed amount" in these calculations is the hospital's gross charge minus all contractual adjustments, and it includes both what the health plan paid and any patient cost-sharing. It reflects total reimbursement received, not just the payer's portion. When comparing figures across hospitals, keep in mind that the allowed amount includes both the insurer's payment and any patient cost-sharing; a split that can vary considerably from claim to claim. ## Two other requirements in the update **Revised attestation language.** The prior template included an affirmation statement. The new version requires a formal attestation confirming that the hospital has included all applicable payer-specific negotiated charges that can be expressed as a dollar amount, and that for charges that cannot be expressed as a dollar amount, it has included all information necessary for the public to derive one. The hospital must also name the CEO or other designated senior official responsible for overseeing the accuracy of the data. **Organizational NPI encoding.** Hospitals must now encode their Type-2 (organizational) NPI associated with an active hospital taxonomy code directly in the MRF. This is a standardization measure intended to improve comparability across files and connect hospital MRF data more reliably to other provider datasets. The NPI requirement addresses one of the more persistent friction points in price transparency work. Identifying which entity in a payer's MRF corresponds to a specific hospital facility has been genuinely difficult, particularly for large health systems that appear across dozens of NPIs. Having the organizational NPI encoded in the hospital's own file creates a cleaner bridge between data sources. ## For hospitals preparing for April 1 From the provider side, compliance with the version 3.0.0 template means more than reformatting a file. Hospitals need to pull 12 to 15 months of EDI 835 remittance data, calculate median, 10th percentile, and 90th percentile allowed amounts for each payer-specific negotiated charge that is expressed as a percentage or formula, and encode those figures accurately alongside remittance observation counts. For hospitals with large payer mixes and many percentage-based contracts, that is a meaningful operational lift. The attestation requirement adds another layer. By signing off with a named senior official, the hospital is taking on formal accountability for the accuracy of what is published. That changes the internal calculus around data quality review before the file goes out. ## Using the new data in practice The estimated allowed amount was a real limitation in the prior framework. Its value depended entirely on the methodology the hospital used to produce it, which was applied inconsistently and was difficult to audit. The shift to percentile-based actual remittance data closes that gap considerably for percentage-based contracts, and it makes [benchmarking work more reliable](/pricetransparencyproject/blog/a-practical-look-at-reimbursement-benchmarking-with-price-transparency-data/) when you are comparing reimbursement across hospitals. That said, there are some real limits to what the new data can tell you. The percentile values are backward-looking. They reflect what was actually paid over the prior 12 to 15 months, not what a future claim will pay. For contracts that have been renegotiated or for hospitals that have updated their chargemasters recently, the historical distribution may not reflect current economics. The observation count field matters a lot here. When a hospital publishes P10/median/P90 figures based on a small number of remittances, those figures carry more uncertainty than figures backed by hundreds or thousands of observations. We look at volume alongside the rate itself when drawing conclusions from this data, and that practice becomes even more relevant under the new framework. One scoping note worth keeping in mind: these requirements apply to hospitals as defined under 45 CFR Part 180, not to all provider types. Ambulatory surgery centers, physician groups, and diagnostic labs that operate under separate licenses and billing structures are not subject to the same MRF template requirements, regardless of ownership. This is a meaningful distinction for managed care teams doing multi-setting analysis. The percentile data and attestation requirements described here are specific to the hospital MRF. For teams doing multi-setting analysis that includes ASCs, physician groups, or other non-hospital providers, payer MRFs are the more comprehensive source. They cover all in-network providers regardless of facility type and often carry more rate detail. For fee-schedule-based contracts, the changes are less dramatic. A flat dollar rate is still a flat dollar rate, and the single-value reporting structure remains. The percentile requirement applies specifically to charges that cannot be expressed as a direct dollar amount. ## Enforcement begins April 1 The original hospital price transparency rule took effect in January 2021, requiring hospitals to publish machine-readable files for the first time. Since then, CMS has progressively tightened the requirements through multiple rulemaking cycles, adding the standardized template format in 2024, strengthening the affirmation requirement, and now replacing estimated amounts with actual remittance-based data. Each update has pushed the data closer to reflecting what hospitals are actually paid rather than what they estimate they might be paid. The version 3.0.0 changes are the most significant methodological update to the hospital MRF since the rule's inception, and they set a higher floor for what rigorous price transparency analysis can do. CMS delayed enforcement of the January 1 effective date to give hospitals additional time to update their files. That window closes April 1, 2026. Hospitals that have not yet moved to the version 3.0.0 template and encoded the required percentile data, attestation language, and organizational NPIs will be out of compliance. Non-compliance carries real financial consequences. CMS can issue civil monetary penalties of up to $300 per day for smaller hospitals and up to $5,500 per day for larger ones, and the agency has been actively issuing penalties since late 2023. Enforcement activity has continued to increase since then. For anyone consuming hospital MRF data for benchmarking or analysis, April 1 is also a useful moment to audit your sources. Files published before that date may still reflect the old format. After enforcement begins, you should start seeing the new structure more consistently, though file quality and completeness will continue to vary across hospitals as it always has. We have written about [what payer compliance looks like when a major schema update takes effect](/pricetransparencyproject/blog/transparency-in-coverage-tic-schema-2-0-is-live-updates/), and the same dynamic applies here on the hospital side. We are watching how the new fields roll out across the files we work with and will share what we find. --- ## Part 2: A Practical Look at Reimbursement Benchmarking with Price Transparency Data - URL: https://payerset.com/pricetransparencyproject/blog/a-practical-look-at-reimbursement-benchmarking-with-price-transparency-data/ - Published: March 16, 2026 - Author: Jacob Little - Section: The Price Transparency Project This is Part Two of a series on using price transparency data for benchmarking. You can take a look at [Part 1 here](/pricetransparencyproject/blog/how-to-analyze-hospital-price-transparency-data-for-reimbursement-benchmarking/). We recently helped a customer work through one of the most common questions we hear in managed care: am I getting paid more or less for emergency visits than the other hospital in my market? It sounds like a simple question. It turns out to be anything but. The conversation started because an analysis had been circulating comparing commercial emergency visit reimbursement between two competing health systems in the same city. The conclusion was clean and quotable: Hospital A receives 1.5x more than Hospital B for emergency visits from the same commercial payer. Attention-grabbing for sure. But when we worked through the methodology behind it, the numbers told a very different story. We want to be upfront about something. We are not sharing this to point fingers at anyone. Price transparency data is genuinely new territory, and figuring out how to use it well is a challenge the whole industry is working through together. What we can offer is what we have learned from doing this work with customers over time. ## The Problem with Single-Code Comparisons We are going to use Emergency visits as an example, but the lessons in this post apply to a variety of different services. The original analysis pulled one billing code, 99284 (a Level 4 emergency visit), directly from hospital machine-readable files and compared the estimated reimbursement between two hospitals. That seems like a reasonable starting point. In practice, it produced a conclusion that was the opposite of what the full picture showed, for two reasons: First, it only captured a piece of total charges. An emergency visit generates two separate components: a facility fee and a professional fee. The facility fee covers the hospital's resources, the room, the nursing staff, the equipment. The professional fee covers the physician or clinician who evaluates and treats the patient. These can appear on separate claims, be negotiated separately, involve physician groups, and vary independently from one organization to another. The original analysis looked only at the facility reimbursement for 99284 and left the professional component out entirely. Second, a 99284 is rarely the only code billed for an emergency visit. It's often one line item. When a patient comes in with chest pain, the 99284 is just the starting point. What follows is a cascade of additional services: blood draws, an EKG, imaging, IV access, medications, and more. The professional charges for a physician-patient evaluation can originate from an independent physician group partnered with the hospital. Each of those generates its own billing code, and each of those codes can be negotiated separately. The reimbursement differences across those codes, especially in labs, can end up being far larger than anything you would see on the E/M code alone. Comparing two hospitals on 99284 in isolation is like comparing two restaurants on the price of one ingredient and calling it a full meal comparison. You will get a number, but it rarely tells you the entire story. ## What a Real Comparison Looks Like: Start with the Bundle When we work through questions like this with customers, the first thing we do together is define what we are actually pricing before touching any data. For an emergency visit, that means building a clinically grounded bundle of billing codes that reflects how a real visit is actually billed. For a standard Level 4 ED visit with a chest pain and cardiac workup presentation, here's an example of a core bundle we would work with: ![Sample bundle of an emergency visit](/images/blog/a-practical-look-at-reimbursement-benchmarking-with-price-transparency-data/ed-visit-bundle.png) Worth noting: several of those codes split into both a professional and a facility component, specifically the E/M visit itself. Some hospitals bill EKGs globally using 93000, while others split them into the technical (93005) and interpretation (93010) components. Understanding how each organization actually bills is part of the work, and it matters for the comparison. Once you have your bundle, you need to price it across three separate data sources. Not one, not two. All three. ## The Three Data Sources You Need to Triangulate **Payer Machine-Readable Files (Transparency in Coverage)** Commercial carriers are required by law to publish negotiated rates in these files, broken out by plan. This is the closest thing we have to ground truth on what a payer has contractually agreed to pay. Payers are required to post accurate, complete data in these files, and consistent enforcement of that requirement is essential to making price transparency work the way it should. Several challenges continue to exist as we look to make meaningful use of the information. A couple examples include massive file sizes (several Terabytes and millions of rows per file), expiring access links, API rate throttling, data complexity, and instances of data duplication. **Hospital Machine-Readable Files (Hospital Price Transparency)** Hospitals publish their own pricing files and are required to affirm the accuracy and completeness of their MRFs as of July 1, 2024. These include standard charges, payer-specific negotiated rates, and estimated amounts. We regularly use this data as a cross-check and a supplemental reference as opposed to a primary source. Estimated amounts in hospital MRFs can be tough to decipher, particularly when complex contract structures are involved. For example, a complex rate analysis occurs if a hospital operates under a percent-of-billed-charges contract. In these cases, the file shows a percentage rather than a dollar amount. You see "68% of billed charges" and still cannot calculate what that means in dollars without knowing the hospital's actual charge. While these types of arrangements are becoming less common, it's during times like this that the other sources come in handy. **Claims Data** This is a great sounding board that strengthens hospital benchmarking. Remittance data (835 files) shows the billed amount, allowed amount, paid amount, adjustments / denials, and the patient responsibility across real transactions. When we have several observed remittances for a given set of billing codes, we have a high-confidence picture of what those codes are actually reimbursing in practice. For percent-of-charge contracts: the payer MRF gives you the rate as a percentage, claims data tells you what the hospital typically charges, and multiplying those together gives you a reliable estimated reimbursement. You then validate that against the actual remittances you have observed. That is where the real picture comes into focus. ## What We Found With a Comprehensive Approach Here is how this plays out with real data. We worked through a comparison of two competing hospitals in the same market: Hospital A and Hospital B, both serving a similar commercial payer mix. We focused on commercial PPO reimbursement using the bundle above. The original analysis had claimed Hospital A receives more than Hospital B. Here is what we found when we applied the full methodology. **Head-to-Head Bundle Comparison: Commercial PPO** ![Sample breakdown of a real emergency visit comparing two hospitals](/images/blog/a-practical-look-at-reimbursement-benchmarking-with-price-transparency-data/hospital-comparison.png) ![Totals for the emergency visit bundle comparison between two hospitals](/images/blog/a-practical-look-at-reimbursement-benchmarking-with-price-transparency-data/hospital-comparison-totals.png) The conclusion flips entirely. Hospital A does receive more on the headline facility fee for the 99284 code, which is exactly what the original analysis highlighted. But once you account for the full visit, Hospital B comes out ahead by roughly $250 per encounter, about 12% higher overall. Here is the part that really matters. The 99284 facility fee, the single number the original analysis was built on, shows Hospital A higher by a good margin. But then look at what happens in the labs and the rest of the bundle. Hospital B collects significantly more across the labs and the troponin, and edges ahead on the professional fees as well. That is where the negotiating leverage actually lives, and it is easy to miss entirely if you are only looking at one code from one source. ## A Note About Percent-of-Charge Rates This kind of analysis also surfaces a challenge worth spending more time on. It's difficult to analyze hospital reimbursement using price transparency data alone when a hospital operates under a percent-of-charge contract. Here is how these contracts work. Rather than agreeing to pay a fixed dollar amount for a lab test, the payer agrees to pay a percentage of whatever the hospital bills. If a hospital charges $200 for a metabolic panel under a 65% of billed charges contract, the payer pays $130. If that hospital later updates its chargemaster and raises the charge to $250, the payer pays $163, and the hospital never had to reopen the contract to get there. Understanding which structure applies to which codes is a prerequisite for meaningful analysis. If you are looking at a payer MRF and seeing a percentage instead of a dollar figure, you are dealing with a percent-of-charge contract, and you will need additional data to make it actionable. ## Final Thoughts Claims data is becoming increasingly valuable for hospital benchmarking. Remittance data unlocks added visibility by going under the hood to help showcase billing patterns, validate reported rates, distill code cohorts, and help close the loop on percent-of-charge contracts. Federal enforcement energy should remain consistent, focused, and constructive. With the introduction of [Schema 2.0](/pricetransparencyproject/blog/transparency-in-coverage-tic-schema-2-0-is-live-updates/), this is a fantastic step forward and even more improvements are [coming in 2027 and beyond](/pricetransparencyproject/blog/cms-proposes-major-updates-to-transparency-in-coverage-rules/). Even a thorough analysis has limits. The methodology we walked through is more accurate than pulling estimated amounts from a hospital MRF for one billing code, but it still involves estimates. Every emergency visit is different. Every contract is different. We are modeling a typical clinical presentation, not a specific patient encounter. The goal is to get directionally right with reasonable confidence, not to manufacture false precision. This work takes real expertise. We have been doing it alongside managed care professionals for years and still approach every new analysis with humility. If someone tells you price transparency benchmarking is simple or that a tool handles it automatically, that is worth questioning. It takes experienced people to apply this data well. Even with its challenges, the good news is that when you approach this the right way, with the right bundle, the right data sources, and a real understanding of the contract structures involved, you get answers that are genuinely useful. You find out where reimbursement is strong, where there is room to grow, and where to focus energy going into the next negotiation. --- ## Part 1: How to Analyze Price Transparency Data for Reimbursement Benchmarking - URL: https://payerset.com/pricetransparencyproject/blog/how-to-analyze-hospital-price-transparency-data-for-reimbursement-benchmarking/ - Published: March 10, 2026 - Author: Matt Phillips - Section: The Price Transparency Project Price transparency data is one of the most powerful tools to emerge in healthcare in recent years. It also, like so many aspects of healthcare, is full of nuance. We have seen plenty of examples where analysts pull numbers from machine-readable files, find a striking difference between two organizations, and publish a conclusion that falls apart the moment someone with real contracting experience looks at the methodology. The challenge, in most of those cases, is not the data as much as it's the approach. Through hundreds of customer interactions, we've been able to see how experts are using this data everyday. In this post, we take some of these learnings and attempt to lay out a framework from all these interactions that you can use when benchmarking reimbursement between hospitals or healthcare organizations. ## Start with Strategy, Not Data Before you open a single file or run a single query, start with answering a fundamental question: what are you actually trying to accomplish? Are you a managed care leader preparing for contract renegotiation with a specific payer? Are you a consultant helping a health system understand where they are underpaid relative to peers? Are you an employer trying to steer members to higher-value providers? The answer shapes everything: which codes to analyze, which data sources to prioritize, how to normalize comparisons, and what conclusions you can reasonably draw. Too often, analysts dive into the data without a clear strategy. They pull a huge portion of the data, see interesting-looking numbers, find surprising variations, and draw conclusions that may not be relevant at all. ## Understand That Rates Are as Unique as Contracts This may be the most foundational truth around price transparency: every negotiated rate reflects a unique relationship between a specific payer, a specific plan, and a specific provider. Decades of legal back-and-forth, mergers and acquisitions, strategy shifts, policy changes and necessary responses all add up to data reflected in MRFs that attempt to codify & represent all of that complexity. Two hospitals in the same city, with the same payer mix, serving similar patient populations, can have wildly different reimbursement structures. One might have percent-of-charge contracts. The other might have fee schedules. One might have carved out high-cost drugs and implants. The other might have bundled case rates for certain service lines. This means you cannot simply pull two numbers from two machine-readable files and declare a winner. You have to understand the underlying contract structures and details around services to make any meaningful comparison. ## Use the Right Data Sources Accurate reimbursement analysis requires triangulating multiple data sources. No single source tells the complete story, and each one plays a distinct role in building a reliable picture. ![Payer MRF, Hospital MRF, and Claims data are all necessary for benchmarking](/images/blog/how-to-analyze-hospital-price-transparency-data-for-reimbursement-benchmarking/data-sources.png) **Payer Machine-Readable Files (Transparency in Coverage)** These files, published by commercial carriers as required by federal regulation, contain negotiated rates for in-network providers by plan type. They are the closest thing we have to ground truth for what a payer has contractually agreed to pay, and it is worth saying plainly: payers are required by law to publish accurate, complete data in these files. Enforcement of that requirement matters. When the files are done right, they are an incredibly powerful starting point. Working with these files in practice comes with real challenges. File sizes can run into multiple terabytes with hundreds of millions of rows. Access links expire. APIs rate-throttle. Data can be duplicated across plan types in ways that require careful handling before any comparison is meaningful. That is part of why triangulating with the other two sources is essential, not optional. **Hospital Machine-Readable Files (Hospital Price Transparency)** Hospitals publish their own pricing files and are required to affirm the accuracy and completeness of their MRFs as of July 1, 2024. These files include standard charges, payer-specific negotiated rates, and estimated reimbursement amounts. We treat hospital MRF data as a useful supplemental reference, particularly for cross-checking, but not as a primary benchmarking source. The estimated amounts can be unreliable, especially for complex contract structures. It is a piece of the puzzle, not the foundation of the analysis. **Claims Data** Contracted rates are one thing, but real-world claims and utilization unlocks more precise benchmarking and cohort analysis, helps you understand potential revenue impacts of higher reimbursements, and can be a useful tool in interrogating where contracts live within complex organizational structures. Claims data shows what actually happened: what was billed, what was paid, and how consistently. Remittance data (specifically the 835 files) reveals actual reimbursement amounts across countless observed transactions. This also becomes essential when you are working with percent-of-charge contracts. The payer MRF gives you the rate as a percentage, claims data tells you what the hospital typically charges, and together they let you calculate an estimated reimbursement, which you can then validate against observed remittances (if available). That triangulation can be powerful. The organizations doing this work are using all three sources together, cross-referencing and validating rather than relying on any one of them alone. ## Build Bundles, Not Single-Code Comparisons ![Services can be bundled in the MRF data](/images/blog/how-to-analyze-hospital-price-transparency-data-for-reimbursement-benchmarking/bundled-services.png) A hospital visit is rarely a single billing code. An emergency visit regularly includes the evaluation and management code, labs, imaging, cardiac diagnostics, IV services, and potentially dozens of other line items depending on how the patient presents. A knee surgery includes the procedure code, anesthesia, implants, facility fees, and post-operative care. An infusion visit includes the drug, administration codes, and nursing time. Comparing a single code between two organizations tells you very little about total reimbursement for that episode of care. Remember to always build clinically appropriate bundles that reflect how services are actually delivered and billed. Define the full picture before you touch any data. ## Account for Professional and Facility Components Many services generate both a professional component (the physician's work) and a facility component (the hospital's resources). These might appear on separate claims forms, can be negotiated separately, and can vary independently from one organization to another as well as from service to service. Any analysis that only captures one component is going to be off. And because different organizations structure their billing differently, understanding how each organization actually bills is a big part of the effort. ## Normalize for Different Reimbursement Structures ![Contracts can include Fee Schedule, Percent of Charge, Case Rates and bundles, Carve-outs negotiated types](/images/blog/how-to-analyze-hospital-price-transparency-data-for-reimbursement-benchmarking/contract-types.png) Different contract structures, at the billing code level, require different analytical approaches, and making a small error can skew your entire comparison. Fee schedules and specific negotiated rates are the simplest to work with. The payer MRF shows a dollar amount for each code, and you can compare directly across organizations. This shows up as "Fee Schedule" and "Negotiated" in the MRF data under the Negotiated Type field in the TiC Schema. Percent of billed charges are more complex. The MRF shows a percentage, but you need to know what the hospital actually charges to calculate expected reimbursement. This may require claims data and hospital MRFs to estimate typical charge amounts for that organization and code combination. Even then, it will be an estimate at best to truly understand the dollar impact. Case rates and bundles require understanding the scope of what is included in each payment. An ambulatory surgery center might receive one payment covering the facility fee, surgeon fee, anesthesia, and implants, while a hospital bills those components separately. Comparing them requires knowing what is inside each rate. Carve-outs for high-cost items like implants, specialty drugs, or transplant services are often reimbursed separately from standard rates. Missing these can dramatically skew an analysis, particularly for service lines where carved-out items represent a significant share of total revenue. These can be classified as CSTM codes in the data, Revenue Codes (RC), or under classifications that aren't used as commonly such as an AP-DRG. In practice, most sophisticated contracts are hybrid structures that combine several of these approaches. Knowing which structure applies to which codes is a prerequisite for any meaningful comparison. ## Validate with Claims Data Transparency data tells you what rates were negotiated. Claims data tells you what actually gets paid. These do not always match. Contractual adjustments, claim denials, bundling edits, and other factors can create real gaps between negotiated rates and actual reimbursement. When you have remittance data with sufficient volume (we look for at least 1,000 observations per code where possible), you can validate your transparency-based estimates against real-world outcomes. If your transparency-derived estimate says a hospital should receive $500 for a code, but claims data consistently shows $350, something in the analysis needs revisiting before drawing any conclusions. ## Service Type Matters The methodology above applies broadly, but the specific approach varies significantly depending on what you are analyzing. Emergency and acute care is highly variable by patient presentation and requires flexible bundles built around common clinical scenarios. Professional and facility components need to be analyzed and compared within their respective buckets. Inpatient reimbursement routinely involves Medicare Severity Diagnosis Related Groups, which bundle payment for an entire stay. Analyzing these requires understanding DRG weights, base rates, outlier provisions, and any carved-out services. Case mix and severity add another layer of complexity. Outpatient procedures are often more straightforward, particularly for ambulatory surgery centers with bundled case rates, though variation in what is included versus billed separately still requires attention. Infusion services are dominated by drug costs, which are often reimbursed on ASP or WAC-based structures with different margins than administration codes. Biosimilar substitution and 340B program participation can significantly affect comparisons. Physician services outside of a facility setting are generally simpler, since you are usually dealing with fee schedules without facility components. Modifier usage and place-of-service variations are still worth watching. ## Caveats Worth Acknowledging Even with the right methodology, price transparency analysis has real limits, and we think it is important to name them honestly. Data quality varies across payers and hospitals. Some publish clean, comprehensive files. Others have gaps, formatting inconsistencies, or errors that require extra interpretation. MRF data reflects a point in time. Contracts get renegotiated, rates change, and an analysis built on last quarter's data may not reflect what is true today. Not everything shows up in MRFs. Value-based incentives, quality bonuses, and other arrangements can affect total reimbursement without appearing in transparency files. Billing practices differ. Two hospitals might deliver identical clinical services and bill them differently based on their RCM systems, coding practices, and internal processes. That affects comparability even when you use the same code bundles. And honestly, this work is just complex. We have been doing it alongside experienced managed care professionals for years and still approach every new analysis with humility. If someone tells you this is easy or that a simple tool can handle it automatically, we would encourage some skepticism. ## A Framework for Getting It Right ![Complete framework for contract rate benchmarking](/images/blog/how-to-analyze-hospital-price-transparency-data-for-reimbursement-benchmarking/benchmarking-framework.png) To pull it all together, here is how we approach reimbursement benchmarking using price transparency data: **Start with strategy.** Know what question you are trying to answer and why it matters before you touch any data. **Use multiple data sources.** Triangulate payer MRFs, hospital MRFs, and claims data. No single source is sufficient on its own. **Build clinically appropriate bundles.** Never draw conclusions from single-code comparisons. Model how care is actually delivered and billed. **Capture all components.** Include both professional and facility fees wherever applicable. **Understand contract structures.** Know whether you are dealing with fee schedules, percent-of-charge, case rates, or hybrid arrangements, and adjust your methodology accordingly. **Validate with claims data.** Use remittance data to confirm that your transparency-derived estimates reflect real-world reimbursement. **Acknowledge limitations.** Be honest about what your analysis can and cannot conclude. Avoid overreach. ## The Bottom Line Price transparency data has genuine potential to shift how decisions get made in healthcare, for providers, payers, employers, and patients. But realizing that potential requires rigorous methodology and the kind of humility that comes from working closely with the data over time. We are still early in this journey as an industry. The data will get better. The tools will improve. Enforcement will continue to develop. And we will all be better served by a community that approaches this work carefully and shares what it learns along the way. --- ## Transparency in Coverage (TiC) Schema 2.0 Is Live - Updates - URL: https://payerset.com/pricetransparencyproject/blog/transparency-in-coverage-tic-schema-2-0-is-live-updates/ - Published: February 5, 2026 - Author: Matt Phillips - Section: The Price Transparency Project February 2nd, 2026 marked the first enforcement deadline for Transparency in Coverage Schema 2.0, a significant change to how payer data is published and accessed. We've been parsing the latest MRFs and wanted to share what we're seeing on the ground. We plan to update this post each quarter as payers continue adapting to the new requirements. Schema 2.0 is the first step. [We recently did a deep dive in to proposed rules for 2027 and beyond.](/pricetransparencyproject/blog/cms-proposes-major-updates-to-transparency-in-coverage-rules/) ## Refresher: What's New in Schema 2.0 There are a lot of updates, but here are a few of the highlights: **Network Name** The common carrier network name most familiar to members and the public. No more filtering through dozens of internal plan names. BlueCard networks are now called out explicitly, which helps separate local contracted rates from BlueCard passthrough rates for benchmarking and negotiation. ![Network name in payer MRF](/images/blog/transparency-in-coverage-tic-schema-2-0-is-live-updates/network-name.png) **Business Name** The common business name associated with the EIN (Tax ID). Previously, business names were only tied to NPIs via NPPES. Now we can group rates by business name and Tax ID, making it easier to determine if a rate applies to, as an example, Hospital A, Hospital B, or a physician's private practice. ![Business organization name in payer MRF](/images/blog/transparency-in-coverage-tic-schema-2-0-is-live-updates/business-name.png) **Plan Sponsor Name** For employer plans, shows the plan sponsor's business name. Helpful for distinguishing employer-sponsored vs. commercial plans. **Issuer Name** More specific than before. For example, "UnitedHealthcare Florida" rather than just UnitedHealthcare. **Setting** Indicates whether the rate applies to inpatient, outpatient, or both (in addition to the existing billing class for facility fee and pro fee). ## What We're Actually Seeing with Compliance We'll update this throughout the year and, as a reminder, [you can also view our public payer compliance scorecard.](https://docs.payerset.com/payers/) ### February 2026 Update It's rare for the Transparency in Coverage schema to get a dramatic update like this. Payers are retrofitting their processes and systems to comply. It's inevitable that mistakes will happen but we're also seeing some payers aren't posting the new format at all. **Payers not posting the new schema** As of February 2nd (the official enforcement day for TiC 2.0), many State Blues and Cigna have not updated to the new schema. This creates a fragmented landscape where some payers are posting 2.0-compliant files while others remain on the original schema, requiring anyone working with this data to reconcile both formats. For context, here's a screenshot showing the only Blues that are posting under the new 2.0 federal TiC rule: ![Overview of which payers are complying with Transparency in Coverage Schema 2.0](/images/blog/transparency-in-coverage-tic-schema-2-0-is-live-updates/compliance-overview.png) **Erroneous machine-readable files (MRFs)** UnitedHealthcare has published files with errors and typos. At Payerset, we don't blindly parse data according to the rules. We review how each payer is actually posting, then adjust our processes to handle the nuance and interpretation from payer to payer. This kind of manual remediation is necessary to ensure accuracy, but it takes additional time with such a monumental change. **Material changes to data access methods** Some payers have significantly changed how files are accessed. United, for example, has restructured their file access methods, requiring anyone ingesting this data to rebuild parts of their pipelines. **Last-minute CMS updates** At 9:52 AM on February 2nd, CMS was still updating their official schema documentation. When payers see last-minute updates, it can delay their internal processes too. The bottom line: many payers are not currently compliant with federal law. This is a transitional period, and the industry is figuring it out in real time. ## What This Means for Anyone Working with MRF Data If you're working with MRF data, expect some turbulence this quarter. The mix of 1.0 and 2.0 files, varying compliance levels, and payer-specific quirks means more data validation work. Keep in mind this schema is new and everyone is figuring out compliance. This is a transitional period, but it's a transition toward better, more detailed information. If you have questions about what you're seeing in the data or how to work with the new fields, reach out to us directly at [info@payerset.com](mailto:info@payerset.com). We're happy to help. [You can read our deeper guide to understand everything that's in Schema 2.0.](/post/transparency-in-coverage-schema-2-0/) --- ## CMS Proposes Major Updates to Transparency in Coverage (TiC) Rules - URL: https://payerset.com/pricetransparencyproject/blog/cms-proposes-major-updates-to-transparency-in-coverage-rules/ - Published: February 3, 2026 - Author: Matt Phillips - Section: The Price Transparency Project ## TL;DR - CMS is proposing some of the most significant updates to TiC requirements since its inception. - Plans would consolidate rate files by provider network instead of by individual plan, dramatically increasing usability. - Annual Utilization File would show which providers actually received reimbursement for a given service - In-network and out-of-network files move from monthly to quarterly updates - Enhanced out-of-network data: Claims threshold drops from 20 to 11, reporting period extends from 90 days to 6 months. - Drug Transparency pushed back: Initially was supposed to begin early 2026 but timeline is now TBD ## What You Need to Know The proposed rule represents CMS's response to years of feedback about the practical challenges of working with transparency data. While the 2020 final rules succeeded in releasing an enormous amount of previously hidden pricing data, implementation still had significant gaps: massive file sizes, duplicative data, lack of context about which rates actually matter, and misalignment with hospital price transparency formats. [We've written about these challenges plenty](/post/the-positive-future-of-price-transparency-in-the-u-s-in-2025/) and these proposals aim to fix some of those friction points systematically. For CFOs and managed care leaders, this means a more reliable foundation for benchmarking rates, validating contracted amounts, and preparing for negotiations. The data won't just be more accessible; it will be more trustworthy and easier to act on. ### Timeline The proposed rule was published December 23, 2025. The comment period closes February 23, 2026. If finalized, most provisions would apply for plan years beginning on or after January 1, 2027. You can view the official announcement [here](https://www.federalregister.gov/documents/2025/12/23/2025-23693/transparency-in-coverage). We've summarized the highlights below. ## Network-Based Rate File Structure: Identify the Correct Network and Rates Faster ### The Problem Under current rules, health plans and issuers must publish a separate in-network rate file for each plan or coverage option they offer. This creates massive redundancy when multiple plans share the same provider network and negotiated rates. Consider a realistic scenario: A regional Blue Cross Blue Shield plan might offer different commercial plan variations (different metal tiers, employer groups, and benefit designs) that all use the same underlying provider network with identical negotiated rates. Under current rules, that plan must publish 50 separate rate files, each containing the exact same provider list and rate information, just with different plan identifiers in the header. Now scale that across the BlueCross BlueCard network, where participating Blue plans across all 50 states can share network access. In addition to the complexity of managing this data, simply finding the "correct" plan in the data becomes unnecessarily complex. ### The Proposed Solution CMS proposes requiring plans and issuers to publish one in-network rate file per provider network rather than per plan. Each file would include: - Common provider network name for clear identification - Enrollment totals for each plan using that network (as of the file posting date) - All negotiated rates for that network's providers Plans offering multiple products that use the same network would reference a single network file instead of duplicating the data dozens or hundreds of times. This change could reduce file sizes, eliminate redundant data, and make it far easier to identify the relevant rate for a specific provider-payer combination. ![Before and after of Network Rate File update](/images/blog/cms-proposes-major-updates-to-transparency-in-coverage-rules/inline-1.jpg) ### Better Alignment with Hospital Reporting This structure also brings payer reporting into closer alignment with how hospitals report under their own price transparency rules. [Hospitals already organize their data by payer and network](/post/making-sense-of-hospital-price-transparency-data/), so having insurers report the same way creates better apples-to-apples comparisons across both datasets. ## Annual Utilization File: Focus Analysis on Providers Who Perform the Service ### The Problem Current in-network rate files contain negotiated rates for every provider with whom a plan has a contract, regardless of whether that provider ever actually submits a claim. This creates what the community have started calling "zombie rates" or "ghost rates": contractual arrangements that exist on paper but have zero real-world utilization. It's unclear if this is intentional obfuscation, data & system limitations on the backend, different interpretations of the rules, or a combination of all of these. But when you're benchmarking rates for a specific procedure or trying to understand the competitive landscape for a service line, these zombie rates add enormous noise to the analysis. You might see a contracted rate for a pediatric cardiologist performing total knee replacements, or negotiated amounts for providers who haven't billed the plan in years. ### The Proposed Solution CMS proposes a new Utilization File that plans and issuers would post annually. This file would identify all providers (by NPI, TIN, and Place of Service code) who received reimbursement for at least one claim during a 12-month period that ends 6 months before the file posting date. The Utilization File would list: - Each covered item or service (by billing code) for which claims were reimbursed - Each in-network provider who was reimbursed for that item or service - The connection between what services were actually billed and which providers delivered them ![Before and after of utilization file implementation](/images/blog/cms-proposes-major-updates-to-transparency-in-coverage-rules/inline-2.png) This creates a useful filter for rate benchmarking. For example, when benchmarking orthopedic surgery rates in a specific market, you can now focus exclusively on providers who actually performed those procedures for that plan's members. ### Real-World Application We pushed for full utilization & claims data from the payers but this is an important first step. There are no magic bullets here, though - we envision this being a first-pass filter and then further using real-world claims & remits data to understand marketshare, utilization, and validating rate benchmarking. ## Change-Log File: Track Rate Changes from Quarter to Quarter ### The Proposal Plans and issuers would be required to publish a Change-log File with each quarterly in-network rate file that identifies any changes made to the required information since the last posted file. This includes additions, deletions, or modifications to provider networks, negotiated rates, or plan enrollment data. The Change-log provides transparency into rate evolution over time. When you see a rate increase or decrease, you can track when it changed and potentially correlate it with contract renewal cycles, policy changes, or market shifts. This is particularly valuable for: - **Rate trend analysis:** Understanding whether your contracted rates are keeping pace with market movements - **Contract compliance monitoring:** Verifying that mid-year rate adjustments align with contract terms - **Competitive intelligence:** Spotting when competitors renegotiate rates or enter/exit networks We will be monitoring the implementation of this and will continue to provide feedback to CMS on what we see in the data. ## Taxonomy File: See Which Provider-Service Combinations the Plan Considers Valid ### The Problem Plans and issuers use internal taxonomies during claims adjudication to determine if a provider is appropriately credentialed to perform a specific service. A plan might automatically deny reimbursement for a procedure if the provider's specialty doesn't match the service being billed, regardless of whether a negotiated rate exists in the rate file. However, these internal taxonomies haven't been published. ### The Proposed Solution Plans and issuers would be required to publish a Taxonomy File showing their internal provider taxonomy that matches items and services (by billing code) with provider specialties (using Healthcare Provider Taxonomy codes from NUCC). This reveals which provider specialties the plan considers appropriate for which services. The Taxonomy File helps you understand the logic behind the rate file structure. When a rate doesn't appear in the data, you'll have a better idea if it's because: - No contract exists for that provider-service combination - The provider's specialty is deemed inappropriate for that service by the plan's rules - The rate was excluded for other reasons ## Excluded Provider Information: Remove Clinically Inappropriate Rate Combinations from Files ### The Proposal CMS proposes requiring plans and issuers to exclude provider-rate combinations for services that a provider is unlikely to perform based on the provider's specialty. The determination would be based on the plan's internal taxonomy used during claims adjudication. For example, a plan would exclude the negotiated rate for an ophthalmologist performing hip replacements, even if a theoretical rate exists in their contract master file. This directly addresses file bloat and improves data quality. Excluding implausible provider-service combinations: - **Reduces file size significantly:** Fewer irrelevant rate entries to store, transfer, and process - **Improves analysis accuracy:** Benchmarking focuses on clinically appropriate comparisons - **Eliminates confusion:** No more questioning why certain absurd rate combinations exist in the data This is complimentary to the Utilization file and a step in the right direction in reducing zombie rates and increasing usability of the price transparency data. ## Enhanced Out-of-Network Data: Access More Comprehensive OON Allowed Amounts ### Three Key Changes CMS proposes several modifications to make out-of-network allowed amount data more comprehensive and useful: **1. Lower Claims Threshold:** The minimum number of claims required for reporting drops from 20 to 11 different claims per item or service. This means more out-of-network utilization will be captured in the data, particularly for less common procedures or in smaller markets. **2. Longer Reporting Period:** The reporting period increases from 90 days to 6 months, and the lookback period extends from 180 days to 9 months. More data over a longer timeframe improves the reliability of out-of-network cost estimates. **3. Market-Level Aggregation:** Plans and issuers would organize allowed amount data by health insurance market type (individual, small group, large group, or self-funded) rather than by individual plan. This provides clearer market-wide context while maintaining appropriate aggregation for privacy protection. These changes make out-of-network data more comprehensive and actionable for: - **Balance billing risk assessment:** Better estimates of potential out-of-network costs for patients - **Network adequacy analysis:** Identifying gaps in network coverage by specialty and service - **Reference pricing strategies:** More robust data for establishing reference-based pricing programs - **No Surprises Act compliance:** Improved data for calculating qualifying payment amounts ### The Remaining Gap While these improvements are meaningful, the claims threshold issue persists. Even at 11 claims, many payers can still avoid posting out-of-network data for less common services. CMS continues to struggle with balancing privacy protection against the transparency goal of comprehensive out-of-network cost disclosure. ## Quarterly Reporting: Receive Updates Every Three Months Instead of Monthly ### The Change In-network rate files and out-of-network allowed amount files would move from monthly to quarterly reporting cadence. Prescription drug files would remain monthly. ### Why This Makes Sense Negotiated rates typically don't change monthly. Contract renewals and rate adjustments usually happen annually or semi-annually, meaning monthly updates often show no meaningful changes while creating substantial administrative burden for plans and bandwidth costs for file distribution. Quarterly reporting provides a reasonable middle ground: frequent enough to capture meaningful changes, but not so frequent that it generates busywork. The Change-log File (discussed above) ensures that users can track exactly what changed between quarters. - **For plans and issuers:** Reduced compliance burden, lower data storage and bandwidth costs, fewer opportunities for filing errors - **For data users:** More stable data for quarterly analysis cycles, less frequent data ingestion overhead, clearer signals when rates actually change ## Text File and Footer Link: Locate Machine-Readable Files Faster ### The Problem Finding a plan's machine-readable files currently requires navigating through multiple web pages, searching documentation, or using third-party tools that scrape and index file locations. There's no standardized way to locate where a plan posts its transparency files. ### The Proposed Solution Plans and issuers would be required to: - **Post a Text File** in the root folder of their website containing: - URLs for all required machine-readable files - Contact information for inquiries about the files - A point of contact for technical questions - **Include a footer link** on their website homepage titled "Price Transparency" or "Transparency in Coverage" that routes directly to the page hosting the machine-readable files These simple requirements dramatically improve file discoverability and accessibility. Data teams, researchers, and third-party tool developers can programmatically locate and download files without manual searching. This enables: - **Automated data pipelines:** Scripts can reliably find and retrieve updated files - **Consistent file locations:** Standardized paths reduce broken links and missing data - **Better compliance monitoring:** Regulators and watchdogs can easily verify file availability This aligns with hospital price transparency requirements, which already use similar standardization for file locations. ## Product Type Identification: Compare Rates Across HMO, PPO, and Other Plan Types ### The Proposal Plans and issuers would be required to include product type (HMO, PPO, EPO, POS, etc.) in both in-network rate files and out-of-network allowed amount files. Product type is a fundamental characteristic that affects network breadth, provider access rules, and often negotiated rate levels. Including this field enables more accurate comparisons: - **PPO vs. HMO rate analysis:** Understanding rate differences across product structures - **Network strategy development:** Identifying which product types offer the most competitive rates - **Member communication:** Helping members understand why rates differ across their plan options This builds on the improvements in Schema 2.0, where plan identification fields were enhanced to enable better apples-to-apples comparisons across carriers. ## What Didn't Make It (But Should Be on Your Radar) CMS explicitly chose not to address prescription drug transparency requirements in this proposed rule. The agency published a separate Request for Information in June 2025 seeking feedback on how to effectively implement the prescription drug machine-readable file requirement, which has been on hold since 2023. Expect separate rulemaking on prescription drug transparency in 2026. Given the complexity of pharmacy benefit manager (PBM) relationships, formulary tiers, rebates, and manufacturer pricing, the drug transparency requirements may end up being even more significant than these updates to medical service transparency. ## Price Transparency is continuing to gain momentum These proposed changes signal that price transparency policy is moving from "get the data out there" to "make the data actually usable." In particular, we're encouraged because a lot of these updates came directly from feedback from the price transparency community. CMS & policymakers are listening and the foundation for fair and equitable healthcare for everyone is solidifying. ## FAQ **When does this take effect?** Most provisions would apply for plan years (policy years in the individual market) beginning on or after January 1, 2027. However, this assumes the rule is finalized in 2026. The comment period closes February 23, 2026. **Will this reduce file sizes significantly?** Potentially. Depending on how payers implement the network requirement, the network-based structure alone could reduce file counts and total file sizes. We will be closely monitoring the effects of these updates. **What happens to existing Schema 2.0 requirements?** These proposed regulatory changes are separate from (but complementary to) the Schema 2.0 technical format updates that CMS released in 2025. If this rule is finalized, the technical schemas will be updated again to accommodate the new data elements and file structures. Both sets of requirements will apply. **How does the Utilization File interact with the Taxonomy File?** They serve different purposes. The Taxonomy File tells you which provider-service combinations the plan considers clinically appropriate. The Utilization File tells you which of those appropriate combinations actually happened in the real world. Together, they help you distinguish between rates that could theoretically be used versus rates that are actually driving claims volume. **Will plans still have to post rates for every provider in their network?** Yes, the Plan detail will still be available but the network file will add an additional layer or organization to better identify networks and subsequent plans. ## Put Price Transparency Data to Work Payerset delivers the most comprehensive price transparency data sourced directly from health plans and enriched with all-payer claims data. Compare negotiated rates by carrier, network, service line, and product type with confidence. - Validate contracted reimbursement with claims-backed utilization context - Filter out zombie rates and focus on real market dynamics - Benchmark against the providers actually delivering care in your market - Build stronger negotiation strategies with utilization-validated rate intelligence --- # The Price of Healthcare Podcast - Episodes (show notes and transcripts) --- ## Episode 2: Unpacking the mechanics and award sizes of the IDR process - URL: https://payerset.com/price-of-healthcare-podcast/02-idr-process-tia-goss-sawhney/ - Published: September 22, 2026 - Author: Guests: Tia Goss Sawhney, Owner and Managing Director, Teus Health - Section: The Price of Healthcare Podcast Tia Goss Sawhney is an actuary, a doctor of public health, and the owner and managing director of Teus Health. She has worked with the price transparency machine-readable files, inside the independent dispute resolution process itself, and with the federal IDR public use files, a combination that lets her interpret the arbitration system all the way down into the claims data. The No Surprises Act has largely done its job for patients. This conversation focuses on the other half of the law: the independent dispute resolution process that decides what an out-of-network provider gets paid. Tia explains how the qualifying payment amount is set and why it starts too low, how elective surgeries at in-network facilities end up in arbitration, and how the professional fees on a single surgery can climb from tens of thousands of dollars to hundreds of thousands. Listeners walk away knowing how to spot probable IDR claims in their own data, how those awards reach employees through premiums and wages, and where employers might push back. ## In this episode - Why Tia believes commercial pricing only changes when self-funded employers demand it, and what the Consolidated Appropriations Act opened up - Where the No Surprises Act is working for patients, and the one gap left for reference-based pricing plans - Why the qualifying payment amount starts too low: 2019 rates, CPI trending, and ghost rates - Providers winning more than 85% of determinations, and why no one but the arbitrator sees the justification - How elective surgeries at in-network facilities land in IDR, from assistant surgeons to neuromonitoring - The August amendments and the Fifth Circuit's QPA decision, and what neither one changes - Where challenges could come from: EmblemHealth's suit against Dr. Norman Rowe, and False Claims Acts for public employers - How to find probable IDR claims in your own claims data, and how the cost reaches employees ## Figures cited in this episode These numbers come from the federal IDR public use files, so here they are precisely, with the source. The 2.2 million disputes Tia cites for 2025 matches the payment determinations that certified IDR entities made that year: 1,082,247 in the first half and 1,145,039 in the second. Providers prevailed in about 88 percent of payment determinations in the first half of 2025 and about 85 percent in the second half, in line with Tia's "more than 85 percent." HaloMD was the top initiating party in both halves of the year. The IDR amendments Tia mentions took effect August 3, 2026. As she notes on tape, aggregate data reflecting them is not expected until spring 2027. The dispute volumes and win rates above are drawn from the [CMS Federal IDR supplemental background for July 1 to December 31, 2025](https://www.cms.gov/priorities/innovation/data-and-reports/2026/federal-idr-supplemental-background-2025-q3-2025-q4). ## Transcript **Andrew Gordon:** Welcome to The Price of Healthcare. I'm your host, Andrew Gordon. On this show, we sit down with the executives, influencers, and people working to build a functional healthcare market. Every episode, we're unpacking what's broken, what's working, and what it takes to buy healthcare with informed choice. In this episode, we're going to be discussing the No Surprises Act with a particular emphasis on the independent dispute resolution process embedded within the act. My guest today is Dr. Tia Goss Sawhney. Tia is the director, managing director, and owner of Teus Health, where she does analytic and public policy work. She's a fellow of the Society of Actuaries and a member of the American Academy of Actuaries. She holds a doctorate in public health, and she teaches healthcare claims data analysis as an adjunct clinical associate professor at NYU's School of Global Public Health. What compelled me to reach out to her is her expertise in healthcare payments and health insurance claims data, from the high-level policy perspective down to hands-on analysis of large datasets. She has worked directly with the price transparency machine-readable files within the independent dispute resolution process, and with the independent dispute resolution process public use files. This combination is rare and it is exactly what this topic needs. Tia, welcome. **Tia Goss Sawhney:** Thank you, Andrew. I'm so delighted to be here and many thanks to you and to Payerset for inviting me. **Andrew Gordon:** Happy to have you on board. So most of the media coverage treats the No Surprises Act as a consumer protection story. And on that count, it has largely been working. Far less attention goes to the half that decides what gets paid to the provider, or to the fact that the money behind it comes from self-funded employers who typically have no role in the negotiation. The law was built to do two things: keep patients out of the middle of a bill they never agreed to, and settle what the plan pays the out-of-network provider. That second piece runs through arbitration called the independent dispute resolution. Each side submits a number, an arbitrator picks one, and there's no splitting the difference. Now, regulators expected about 22,000 of these cases a year. We're covering the independent dispute resolution process and what's been happening inside it, as well as how it has evolved since it started. So Tia, let's set the stage a little bit. Tell me about your work and how you ended up working on out-of-network payment. **Tia Goss Sawhney:** My first work after studying finance at the undergraduate level at Wharton 40 years ago was a, was as a health insurance actuarial trainee, which means I'm a data person through and through. And I cannot look at data without thinking of costs. So that makes me a money person. Although I have deep experience across commercial, Medicaid, Medicare insurance, much of my work since 2019 has been on behalf of self-funded employers, so specifically on the self-funded portion of commercial insurance. Commercial insurance has systematic structural issues and pricing irrationalities, which I believe will only change when self-funded employers demand change. Unfortunately, until the Consolidated Appropriations Act of 2021, the same act that includes the No Surprises Act, self-funded employers most often were not permitted to access their own payment data. But they can now. And once employers and unconflicted people working on their behalf open the data, problems jump out. I tell my colleagues it's like fishing from a bucket. Exorbitant payments made as a result of the No Surprises Act truly jump. They are large, and they're — and not all of them, but some of them are so large that they just stand out. In addition, I was until recently an executive at a prepayment firm where I worked on behalf of self-funded employers trying to get ahead of the IDR awards and build sounder cases. We were rarely successful, the truth be told. **Andrew Gordon:** And so thinking about your multifaceted background, how do these various lenses land differently? I mean, comparing to other professionals, when you're in this space, you're examining the No Surprises Act, you're looking at some of these things underneath it. Talk to us a little bit about how that comes together. **Tia Goss Sawhney:** As I said, my work is always grounded in data. I'm always looking at the data. But over the decades of looking at the data, I've pulled in the law. I've pulled in clinical. I've been trained as a researcher, and I'm very committed to social justice and very repelled by fraud. **Andrew Gordon:** Switching gears a little bit here, the report card. The No Surprises Act became effective January 1st, 2022. It's almost five years old. How would you say we're doing? **Tia Goss Sawhney:** As you mentioned earlier, from a consumer protection point of view, I believe that the No Surprises Act is doing very well. Consumers are now no longer responsible for surprise bills, and that's wonderful. That was an injustice against patients. The one ongoing area is with respect to reference-based pricing plans. Under reference-based pricing plans, which are a very small portion of the insurance market, emergency services are exempt from surprise billing, but other services are not. But that's a feature of reference-based pricing plans. It's not the fault of No Surprises Act. With respect to paying a fair amount, I would say that the system is failing. And we're going to talk about more specific examples later on, but it's failing in two regards, at the low end and at the top end. So on the low end, the starting price for a negotiation is supposed to be something called the QPA, the Qualified Payment Amount, which is supposed to be a market price, an estimate of a market price, a fair price. We'll call it a fair price. And the law sets out a very specific methodology for calculating the QPA, and that is the median rate for that service as paid by that payer vis-à-vis negotiated rates in 2019. 2019, a very critical date, trended forward using the Consumer Price Index urban version to today, to the date the service was provided. Why is that a problem? That is a problem because in 2019, healthcare prices were not available. **Tia Goss Sawhney:** They were closely guarded secrets. And it's also a problem because healthcare costs have gone up faster than the CPI urban since 2019. And it's also a problem because calculating the median negotiated rate, some payers don't have enough of those rates for them to be truly meaningful for that particular service, or they have a lot of the rates, but they're essentially ghost rates. They're with providers who never actually provide the service because a provider who provides 100 of the services, a provider who provides one of that services, one of that type of service a year, and a provider who provides nothing is all weighted equally. So QPAs tend to be too low. So the starting price is too low. The flip side, though, is that providers and their vendors have been very effective at putting forth and winning arbitration awards that are much, much too high. And when I say too high, 10 times, 100 times any reasonable estimate of the market value, which is just stunning. And it's a stunning waste of our system's resources. This is particularly happening within elective surgeries. And I want to emphasize providers and their vendors. I've been digging through the data recently, and it's really stunning. The market is controlled by a handful of vendors. For example, in 2025, there were 2.2 million disputes, and nearly half of those disputes were represented by just five vendors. In fact, the top vendor, HaloMD, accounted for more than 400,000 disputes. **Tia Goss Sawhney:** HaloMD and presumably others get paid a percentage of the additional revenue that they bring to the out-of-network provider. Therefore, the higher the award they get, the more they get paid. And this is coming out of all of our pockets. It's coming out of employers' pockets. It's coming out of the pockets of anyone who pays, who self-funds for insurance or who pays an insurance premium. **Andrew Gordon:** Seems like there's certainly a lot to unpack and dive into there. So I wanted to just round out in terms of the, the good and bad aspects, the successes and the failures relative to the NSA. You know, I'm hearing that from a consumer protection standpoint, from being able to reduce the responsibility that patients have toward balance bills and everything else of that nature, we are certainly doing really well. But then in terms of the points where we need some more emphasis is just understanding the incentives behind and how these rates and negotiations are essentially being handled and the methodology behind that, we need to unpack a bit better. **Tia Goss Sawhney:** Yes, I agree. **Andrew Gordon:** So going into the QPAs a bit more, you defined them for us and really appreciate stepping through how variable they could be. How exactly are these QPAs failing? **Tia Goss Sawhney:** People don't have confidence in them. And once people don't have confidence, it becomes a free-for-all is how I would best summarize it. Instead, what's being relied on more heavily is the provider offer and the payer's offer. And with respect to the truly exorbitant awards, it is the provider's offer that is being accepted. But overall, it's important to emphasize that more than 85% of the time across all awards, big and small, it is the provider's offer that's being accepted. The system at the, at this moment is very statistically biased toward the providers. **Andrew Gordon:** Fascinating. So QPAs are essentially the starting point for these negotiations and IDR awards. They're generally low based on what's happening on the backend as a solution. What's coming out of it is a much higher basis. These exorbitant awards that you speak of, what's the basis for these? Why is there such a large delta there? **Tia Goss Sawhney:** I wish I could tell you, but here's, here's another catch to the, the IDR system. And that is the provider makes an offer, the payer makes an offer, and as you mentioned, as you said before, the arbitrator has to choose one. There's no splitting the difference. The arbitrator then writes a report that says which one they chose. The offer made by the provider and the offer made by the payer are not disclosed. They're not disclosed to each other, so therefore there's no rebuttal. They're not disclosed to the public. They aren't reviewed under appeal because there is no appeal process. So anyone can write any justification, and the only entity that sees it is the independent dispute resolution entity. Presumably CMS has a right to look at it too, but there's no formal process for triggering a formal review, a formal appeal or even a formal review. So I can't tell you what's being said that justifies these very large rewards. **Andrew Gordon:** I also noticed too, Tia, as you were laying it out for us, it's contrary to how a lot of negotiations happen where you have two parties that come to the table and they're exchanging offers back and forth. They're eventually settling on something. It seems like there's a lot of mechanics or aspects of this that are much more controlled or confidential in fashion, or just are not privy to those key parties. And as we talked about with employers funding a good chunk of it as well, and not even really playing a massive role or any role in the negotiation, it starts to get really challenging. Can you talk a little bit about these? There's examples of elective surgeries that are being arbitrated under the IDR, and just wanted to get some more clarity. Because when I think about the No Surprises Act, and we think about emergency care and balance billing, and we bucket all of that into our mind, and we think, well, these aren't necessarily surprise cases or services, how exactly does it end up that these elective surgeries are being arbitrated under the IDR process? **Tia Goss Sawhney:** I ask the same question. Under the IDR process, the professional charges for any procedure performed in an inpatient facility is subject to IDR, with one exception, and that is if the lead surgeon has the patient sign a form in advance that says whereby the patient acknowledges that they're taking full responsibility. So if I was considering a breast reduction surgery and I go willingly and knowingly go to an out-of-network physician, then the physician could hand me the form and say, “Sign here and you take full responsibility.” Or the physician could not hand me the form, or the physician could hand me the form and I say, and I could say, “I'm not signing this. I don't want to pay this bill.” Then if the surgery, if my elective breast reduction surgery is at an in-network facility, that physician who didn't give me the form or who gave me the form and I didn't sign it can then file for payment under IDR. I consider that to be a mistake, an unintended consequence, or something to be corrected in the current IDR rules. Because if the patient knowingly selects a provider who's out-of-network, then that is not a surprise. The second scenario is, staying with breast reductions for the moment, the physician decides that they want an assistant surgeon in the operating room. Now, the patient has not selected the assistant surgeon, so one could argue that is a surprise. But here's where it's not as much of a surprise. What if the assistant surgeon is from from the same practice as the lead surgeon? Or what if the assistant surgeon is the buddy of the lead surgeon, but from another practice? Is that a surprise, or is that stuffing the operating room to maximize billings? I have seen cases, I've worked cases where, and I can see it in the data, where the assistant surgeon and lead surgeon are from the same practice. **Tia Goss Sawhney:** The anesthesiologist — did the surgeon select the anesthesiologist, or is the in-network facility where the procedure is happening knowingly putting out-of-network anesthesiologists into their ORs? For an elective surgery, there should be no surprise about who's in the operating room. It's a summary of what I'm saying. Yet the surgeon, the assistant surgeon, and the anesthesiologist, and I mustn't forget the neuromonitoring company, which is not an issue for breast reduction as much as for spinal surgeries, which are often elective too, are all coming into the IDR process. **Andrew Gordon:** So in a lot of these cases, Tia, that you're saying the facility itself typically would be in-network, and then these folks who are supporting providing the operation at the individual level, most of them are out of network, just so that I'm understanding it correctly? **Tia Goss Sawhney:** Well, I mean, most surgeries, most days are all in network. But for IDR cases, where there's one provider out of network, there's often a whole cast of providers who are out of network. And they're interconnected with each other. They're from the same medical practice, or they otherwise have connections to each other. You will see the same anesthesiologist working with the same surgeons, the same neuromonitoring company. Sometimes a neuromonitoring company may be a sister group to the medical group. **Andrew Gordon:** I see. Okay. And I guess that makes sense because they would be supporting each other for these services or these operations, and they probably end up working together in a variety of different aspects. But I guess, could you help us understand and break down from a lead surgeon versus an assistant surgeon standpoint versus some of these other characters, as you mentioned, how that plays into either exorbitant awards or this IDR process and what people are getting paid. Help us kind of understand why these different roles are important to segment. **Tia Goss Sawhney:** Each of those out-of-network providers providing one or more services related to that surgery, if the surgery is in an in-network facility, can go through the IDR process. Therefore, a surgery that all the professionals combined may have been paid $20,000, $30,000, $40,000 can end up costing $500,000, $600,000, $700,000, $800,000. And I've actually been working this data for the last few months, and it's astounding. **Andrew Gordon:** Many multiples above, as you mentioned, what a typical reimbursement expectation would look like. You had mentioned before that there is little or no appeal processes or kind of accountability measures in place to prevent some of these exorbitant awards from happening. Talk to us a little bit about what's there, what exists, what doesn't exist. **Tia Goss Sawhney:** Disclaimer here, I am not a lawyer. So any lawyer listening, please forgive me. The way the NSA was written, there was, it was written without any private right of action. So the IDR entity awards have the force of a government decision. They do not have private right of action. And this has been challenged in the courts multiple times. So at the moment, the only recourse is to go to a CMS website and write about your complaint. I shouldn't use the word complaint because complaint, we think of complaints as something that gets filed in a lawsuit. It's not that. It's go to the CMS website and write about your gripe. You'll probably never hear from CMS and they don't have to do anything. They may do something over time if they get enough gripes about the same topic. **Andrew Gordon:** Fascinating. So for the thinking about some of these modifications, going beyond just accountability or other processes that may or may not be present there, what would you say with the NSA IDR process being recently amended? What do you think with these changes that have become recently effective? Are they helping or hurting the process? What are you seeing? **Tia Goss Sawhney:** We don't see anything yet. The amendments to the process were effective in August, and it will be next March or April before data will — before aggregate data will come out. What the amendments did, though, was make the IDR process more accessible to providers. Cheaper, faster. It did not, in fact, address the issues that we've been talking about. In fact, one can reasonably expect it will mean that the number of IDR disputes will continue to grow. **Andrew Gordon:** I did also just want to jump in and make a comment. Possibly also cycle over a question to you just relative to incentives and thinking about as these supportive clinicians and characters in these different services, as more of them either fall out of network or maintain out-of-network status, what incentive, given what we've talked about today with these exorbitant awards and the massive win rates that we're seeing on the provider side, what incentive would these clinicians and folks have to maintain or work to be in-network with various insurance carriers? **Tia Goss Sawhney:** Well, I firmly believe that most medical professionals want to be paid a reasonable amount for their work, that they want the payments to be fast, as fast and as frictionless as possible. To those professionals, thank you. There are, however, a subset of professionals, and more importantly, the medical groups that they work for who are into maximizing revenue. And if that is the game that the medical group is playing, then they should not be in a network. And if they can do their surgeries or procedures at an in-network facility, they then — they have lots of incentive to stay out of network and play the IDR game. **Andrew Gordon:** So there was recently, just going back to as well the amendments and some of the latest things happening in the media and news relative to this process, there was a major court decision regarding qualified payment amounts. What do you see in terms of the results of that and the decision going back to helping or hurting, pros and cons, relative to where we've been and where we're going? **Tia Goss Sawhney:** The qualified payment amount decision was sound, but it was brought, the case was brought by providers in Texas. And so as such, it was to fix the problems that providers perceive with QPAs. Topping the list was the use of ghost rates. Ghost rate is when there are negotiated rates exist between a payer and a provider, but the expectations is that it's never going to be used. So for example, an OB-GYN medical practice that in their contract with the provider has negotiated rates for heart surgery. The OB-GYN doctor's never going to do heart surgery. But when the rates were negotiated, what they did is they created a rate set for all possible physician services. And the OB-GYN medical practice said, “Well, do the OB-GYN services seem to have good rates for us?” And they said yes, and they signed off on it. So their contract actually includes cardiac surgeries, but that's a ghost rate, right? The other thing is that the decision said that the rates have to include incentive and bonus payments. So not all medical services are paid on a fee-for-service basis. Fee-for-service refers to when a specific service is rendered, there's a specific rate for that service, and it's paid. But there could also be payments associated with quality and bonuses so that the specific fee is paid for that service, but at the end of the year, if the doctor or the medical group has done a good job overall, they get an extra 20%. So to get rid of ghost rates and to include the bonus payments in the market rate calculation makes sense. **Tia Goss Sawhney:** What it doesn't — does not change, however, is that 2019 is the base. Most entities can't verify the 2019 rates. Since 2022, rates have been public. So I can go today and look and see what Aetna is paying in a market for cardiac surgery services. And that's available today. And it was available starting in 2022. There were problems early on with the files. The newer files are getting better, but we're still stuck on 2019 and we're under-trending. **Andrew Gordon:** So we're still stuck on 2019, and the idea is that we are going to have a lot more visibility and then accountability too with everybody being able to see the rates as of 2022 and the transparency and coverage files being released. That is really where we could start to see a little bit more of the rubber meet the road, if I'm hearing you correctly? **Tia Goss Sawhney:** Well, and I wouldn't use the 2022 files either. I would, you know, if I was creating the rule today, I would be using today's files. So. **Andrew Gordon:** For sure. Makes a lot of sense. I want to look into the future a little bit and just thinking about where change is going to come from, where the evolution of this is going to continue to go. We talked about with no appeal process and just challenging these individual exorbitant awards, how might people challenge these kind of moving forward? Talked a little bit about how folks historically have or have not been able to challenge them. What are we looking at when it comes to the system change here? **Tia Goss Sawhney:** First and foremost, let me say again, not a lawyer. We need system change. The people paying these bills, which is largely employers, and among employers, it's largely self-funded employers, need to understand what's happening, and they need to bring forth change. In my mind, I believe, I hope, pray that there are opportunities for them to do so. So there is no private right of action against an IDR award. But are there other possibilities? Perhaps. But certainly one can make political noise, and I really advocate for that. And of course, political noise is most effective when employers and other organizations band together. So employer groups and coalitions need to be on top of this. I believe that there may be other opportunities also. So if you can't take action against the award, can you take action against the provider or the vendor? Either one, because these exorbitant awards are not justifiable, but they put forth a justification. So how to break the veil of secrecy and get those justifications? And then if they're making false statements within the justifications, that is a problem. **Tia Goss Sawhney:** And at which point there is action that can be taken. So is there enough circumstantial evidence to cause, to break the veil of secrecy on the justifications and see what's being written and challenge what's been written? For example, there's a case right now that Emblem Health has against Dr. Norman Rowe, who does breast reductions. He and his multiple provider groups do breast reduction surgeries primarily in New York and New Jersey and Florida. And Emblem Health has filed a case against him on just these grounds. Another way of going at it is for self-funded employers, states can't regulate self-funded employers. So, but states can and do regulate providers. So are the providers following state law? So for example, New Jersey has a version of the federal Stark Law that it's much more powerful than the federal Stark Law. And according to my read, not a lawyer, providers cannot self-refer. So a New Jersey surgeon who puts an assistant surgeon from the same practice in the operating room, that may be illegal — not a lawyer. Also in New Jersey, New Jersey has an NSA-type law, No Surprises Act-type law, that predates the federal No Surprises Act. And that seemingly prevents surgeons, the lead surgeons who provide an elective service from seeking payment in excess of the payer's normal out-of-network payment. So if the patient selected the lead surgeon, their lead surgeon can't under New Jersey law, according to my reading. **Tia Goss Sawhney:** So could those payments be challenged under New Jersey law? **Andrew Gordon:** You see a lot of these, Tia, as opportunities for employers to challenge it? Just want to make sure that I'm receiving that right and that is there anything else that you would say that employers might be able to do as it comes to and realizing how much of these awards they're funding? **Tia Goss Sawhney:** Well, if you look at the commercial market, the commercial market is dominated by employers. Now, it's not — the employers often have insurance companies as their administrators. So when Emblem brings a suit against Norman Rowe, the actual cases that are described in the suit are actually cases where this surgery was provided to employees in dependence of New York City, New York City's benefit plan. So, which brings me to another point. Public-funded employers are a special class. So false claims made against public employers, whether they're state or federal, subject to — if it's a federal employer, subject to federal False Claims Acts. And many states have an equivalent at the state level. So when you — they have state-level False Claims Acts. So when — to the extent that these awards are being made against public employers, they have the power of the, of the federal or state and/or state False Claims Acts. They also have potentially the power of the state-level judiciary and legal system. They have the power of the state attorney general. **Andrew Gordon:** I was going to say, is there anything that I neglected to ask you that you'd like to share with the audience? I feel like we've had a really great conversation thinking about what's happening right now, understanding where do we stand, what's been the evolution to date, where it's kind of been breaking, what are some ways and changes that are coming down the pipe, as well as just some changes that could help to make things operate a little bit more smoother with more accountability and transparency. Anything else that you wanted to add for the audience today? **Tia Goss Sawhney:** I would encourage every employer, not just self-funded employers, to find out exactly what they have been paying with respect to NSA IDR claims. If you don't know, you need to know. And self-funded is coming directly from your bank account. But if you are any employer over 50 employees, in some states 100 employees, then you’re experience-rated and these exorbitant awards are going into your experience rating. So therefore, ignorance is expensive. Go find out what you're paying and then work toward change. Make political noise with politicians, with the press, via lawsuits, and work together, work with associations and coalitions, propose legislative change, demand transparency. Demand and appeal the process. **Andrew Gordon:** So I wanted to actually dive in a little bit on your comment about looking at the claims, figuring out and understanding where this is happening. Could you add a little bit of color as to, I assume there's not some massive sign that says this is an NSA IDR determination or what have you when going through the claims data. So could you help us understand how that might emerge or how that would become clear to an employer that is doing exactly that? They're diving into their claims data, they're looking through the information. What are they looking for as it relates to these specific things? **Tia Goss Sawhney:** So just excuse me when I get a little technical here. There are, there are multiple paths to find the IDR claims, or at least the probable IDR claims. Keep in mind, IDR gets initiated after an initial payment. So what you're looking for is a claim that was paid at a reasonable amount that two to six months later typically is paid at a much larger amount. And the way it works is the claim is paid, and then in the data you'll see that the claim — the payment was reversed, and then a much bigger payment was made. Now, when claims are reversed and the much bigger payment's made, there is hopefully a reason code, and hopefully one of the reason codes is IDR decision. That's the best-case scenario. Unfortunately, the data that's often distributed doesn't include reason codes. So if your data doesn't have reason codes, you're still looking for that pattern. Was there a claim paid that several months later was repaid at a much, much larger amount? And that is a clue to probable IDR. **Andrew Gordon:** With these claim adjustment reason codes and the possibility that those codes are there, but you said that sometimes they're not. I don't want to open too much of a can of worms, but I am curious, why might the data streams that folks are reviewing or having access to not be able to include these reason codes? And is it that sometimes they're just not included in it? Is it that these codes are oftentimes there, they're just behind the scenes and not commonly shared in the feed that goes to whether it's employers or the folks who are reviewing these claims on behalf of employers? How would you explain and share that? **Tia Goss Sawhney:** The codes are definitely there in the claims administrator system, which is often an insurance company's system. But yes, it's not distributed out because remember, historically, claims data wasn't shared with employers. And now that it's being shared, the exact fields that get shared are a matter of negotiation. And maybe no one — and so the reason codes have not been part of the request or part of what's been distributed. But they are available. They can be produced. **Andrew Gordon:** I see. And so just also to recap for the audience and to make a clarification. These exorbitant awards, when they're being paid, there is no added expense to the member, to the patient, when these determinations and these claim adjustment reason codes are put in to say, well, the clinician was paid $5,000, six months down the pipe, that's changed to $50,000. My out-of-pocket as a patient on that specific service is not going to waver. Is that correct? **Tia Goss Sawhney:** It will. I mean, it could actually benefit the patient because if it was originally paid as an out-of-network claim, remember, initially it could have been paid one of two ways. It could have been paid as an out-of-network claim adjudicated at the in-network level, but at which point it's not going to — it's probably not going to change, but initially it could have been adjudicated or alternatively, it could have been adjudicated as an out-of-network claim at an out-of-network level. So in that case, then the patient could actually benefit. And you might say, but wait, why would — given the NSA, why wouldn't the payer have adjudicated it upfront at the in-network level? The other thing that has been found and documented is that claims have gone into IDR, a substantial percentage, in fact, of the IDR claims that go into IDR and have awards are, in fact, claims that should never have gone in. So the payer may have adjudicated quite appropriately as an out-of-network claim, but it went into IDR, and the IDR entity decided that IDR applied, at which point it has to be readjudicated as an in-network claim. **Andrew Gordon:** So there wouldn't be a situation, or at least it wouldn't be common to have a situation then where, from a patient cost-sharing perspective, they're actually going to be expected to pay more, or they would be impacted in a negative manner? **Tia Goss Sawhney:** No, it would, it would not be. Overall, patients are being well protected, but payers are not being well protected. **Andrew Gordon:** The reason why I'm asking these questions to you is, as we're familiar with the, the cases against Wells Fargo and Johnson & Johnson, and just some of these other major companies, that was originally brought a lot of the times by employees for exorbitant amounts of money paid or not being able to get competitive rates for certain things. I mean, as we talk about fiduciary liability, and for the audience who may or may not be familiar with the Consolidated Appropriations Act originally in 2021 and has since been going through a lot of updates as well to strengthen it, it's very important for people, the employers who are funding and providing for and looking over and offering competitive benefits to their people to make sure that they're getting the best rates possible and to make sure that they're really targeting and finding value in those contracts and in the partnerships and the claims that they're paying. How does the IDR process impact that when we talk about fiduciary responsibility? And then you have these exorbitant awards that they're paying. Granted, a lot of it is not hurting the patient necessarily, as we said. But when you think about the high expense of healthcare and the damage to salaries or benefits because of this larger and larger expense growing on the employer's accounting book, how do you kind of justify or where does or does not fiduciary liability play a role in this conversation? **Tia Goss Sawhney:** Once again, I'm not a lawyer and the courts have been working on this. I would argue that it's a very important part of fiduciary responsibility. Let's look at it from a few perspectives. First of all, a lot of times employee contributions, employee premiums for their benefits are pegged at a percentage of the expected costs. If it's 20% of the expected total cost, then every dollar extra that's being paid is being paid — 20 cents of that is being paid by employees in their employee premiums. So even if the employee is being protected vis-à-vis their cost sharing, they're paying for it in their premiums. Second of all, total cost of care affects what employers can pay in wages. It also affects whether an employer can even offer a plan. So, I mean, do we want to be paying 3/4 of a million dollars for all the professionals who attended a surgery where they reasonably collectively should have been paid under $50,000? That's so $700,000 spread. If the employer's paying that, that's more employees that employer could hire. That's more raises that employer could give. And sudden spikes in healthcare benefit costs, which a lot of employers are experiencing right now, may determine whether they even continue to offer a plan or whether they change the cost sharing on the plan or whether they up the percentage of the plan costs that the employee has to pay for premiums. I mean, ultimately, you know, employees pay. **Andrew Gordon:** Bringing this home for us, talking about how we've seen cases grow year over year, we've seen these awards be dozens or hundreds of times higher than fair market rates for services, thinking about what's coming down the chain, anything else that you want to share as we round this out in terms of what people should be aware of, and what their action items should be, specifically for, sounds like, employers and policymakers and also a few other stakeholders? **Tia Goss Sawhney:** My very short summary is get involved. Look at the data, get involved, ask questions, challenge. There are many other topics I could talk about, including more details of IDR, so I hope you will invite me back for further discussions. **Andrew Gordon:** For sure. Absolutely. It's been a really good conversation. Now, for those in the audience who are interested in reaching out to you to continue the conversation privately, where would you direct them? **Tia Goss Sawhney:** Um, reach out to me by email. My email address is T-G, as in Tia Goss, Sawhney, S-A-W-H-N-E-Y, at teushealth.com. **Andrew Gordon:** Excellent. Tia, thanks so much for coming on today. It was a pleasure having you. **Tia Goss Sawhney:** Thank you, Andrew. My pleasure. **Andrew Gordon:** That's a wrap for this episode of The Price of Healthcare. We appreciate you tuning in, and we'll see you on the next one. --- ## Episode 1: From a sketch to a rule: the origins of price transparency - URL: https://payerset.com/price-of-healthcare-podcast/01-origins-of-price-transparency-randy-pate/ - Published: September 5, 2026 - Author: Guests: Randy Pate, former Deputy Administrator and Director, CCIIO - Section: The Price of Healthcare Podcast Randy Pate ran the office at CMS that wrote the price transparency rules. As Deputy Administrator and Director of the Center for Consumer Information and Insurance Oversight, he was in the room when the 2019 executive order landed, and he has watched every version of the rule since from the outside. We start before there was a rule at all. Randy explains why a functional healthcare market needs prices before it can have anything else, walks through how an executive order becomes a final rule, and is candid about how much of the first pass was a shot in the dark. He also talks about what changed his own mind: he came in from the payer side believing negotiated rates were a private contract, and the employer listening sessions moved him. Listeners walk away with the original theory of the case, an honest read on where file quality stands, and a practical answer to what a buyer can accomplish with this data today. ## In this episode - Why you can look up the price of a fighter jet but not an MRI, and why prices are the precondition for everything else - How the postwar tax treatment of employer coverage and the fee-for-service model built the incentives we are still living with - What happens between an executive order landing on a desk and a final rule going out the door - Why the employer listening sessions changed Randy's mind about the rule he was skeptical of - Starting with the 100 shoppable services, and why the early files were too big to be usable - CMS running the schema and guidance on GitHub, a first for the federal government - The distance between a negotiated rate on paper and the dollar amount paid on a claim - Why enforcement started light, where states are picking it up, and what Randy tells someone who wants to use this data Monday morning The rule Randy and Andrew trace back to its beginning is Executive Order 13877, "Improving Price and Quality Transparency in American Healthcare," signed in June 2019. ## Enforcement figures cited in this episode These numbers move, so here they are precisely as of publication. CMS has issued civil monetary penalties to 28 hospitals since enforcement began in June 2022. By year: two in 2022, twelve in 2023, three in 2024, ten in 2025, and one in 2026. The ten penalties issued in 2025 ranged from $32,301, imposed on Southeast Regional Medical Center in Kentwood, Louisiana, to $309,738, imposed on Arkansas Methodist Medical Center in Paragould, Arkansas. The $32,301 is the lowest CMS has issued since enforcement began. Across all penalties to date the range runs higher: the largest is roughly $880,000, issued to Northside Hospital Atlanta in 2022. On warning notices, more than a thousand is the accurate figure. CMS has confirmed over 1,249 warning letters to date, and a further 519 hospitals received noncompliance letters between April and early June 2026. Every penalty notice is published on the [CMS enforcement actions page](https://www.cms.gov/priorities/key-initiatives/hospital-price-transparency/enforcement-actions). ## Transcript **Andrew Gordon:** Welcome to The Price of Healthcare. I'm your host, Andrew Gordon. On this show, we sit down with the executives, influencers, and people working to build a functional healthcare market. Every episode, we unpack what's broken, what's working, and what it takes to buy healthcare with informed choice. In this first foundational episode, we're going to be talking about the origins of the price transparency regulation. Roughly seven years ago, the federal government began drafting a rule that would eventually require hospitals, and later insurance companies, to publish their negotiated rates and charges. It survived both political parties and continues to evolve. We're going to be covering how it got started, how it was built, and where it goes from here. My guest today is Randy Pate. Randy's the founder of Randolph Pate Advisors out of Arlington, Virginia, where he advises payers, providers, states, and health technology companies on federal and state health policy. Before that, he was Deputy Administrator at CMS and Director of the Center for Consumer Information and Insurance Oversight, which is the office that runs the health insurance exchanges and writes a great deal of the rule book for private coverage in this country. In that job, he led the turnaround of HealthCare.gov, and he had a hand in shaping several of the policies actively influencing today's market, including Transparency in Coverage, individual coverage health reimbursement arrangements, and Section 1332 state innovation waivers. **Andrew Gordon:** Randy's worked on this from many different seats: public health counsel for House Energy and Commerce, health counsel to Congressman Kevin Brady on Ways and Means, a health policy fellow at Heritage, and a senior advisor at HHS. On the private side, he helped launch MITRE's policy work with CMS and spent six years running public policy for Health Care Service Corporation. He's a lawyer by training, with degrees from Alabama and a master's in public health from Johns Hopkins. Randy, welcome. **Randy Pate:** Thanks, Andrew. I really appreciate it. Thanks for that very nice intro. **Andrew Gordon:** There's been a lot of content covering price transparency in the present tense, with files and compliance and vendors. I haven't seen a lot of people start with the question of why anybody thought price transparency would work in the first place, what the original theory was, and how we went from essentially a sketch to something with teeth. You were in the room from the very first day and you've watched it every step since. Randy, take us back to before there was a rule. What was the problem that you and your colleagues were trying to solve? **Randy Pate:** It's a great question. The fact that I'm calling it a great question is even an oddity when you think about every other sector of the economy: computers, cars, houses. I even went to a seminar one time where somebody said you can literally go online and find the price of a fighter jet, but you can't find the price of an MRI or the price of a hip replacement. It's very difficult and pretty much impossible to do that. The problem is that if we want health care to operate anything like a real market, we have to have the prices. And the prices are not sufficient to have a real market. They're not automatically going to solve everything about the health care system in our country, but it is a necessary precondition to pretty much anything else. If you don't have prices, you're not going to be able to have consumerism. If you don't have consumerism, you're not going to get those signals that we as consumers send about what we like, what we don't like, what kind of quality we're looking for, the tradeoffs that we all make between price and value when we shop for everything else. So if we don't have prices, we're never going to get to those other aspects of consumerism that make so many other products that we buy so great, and that we take for granted. **Andrew Gordon:** Great points, and I do think there are a lot of parallels. I like how you talked about other industries and the fact that we are used to knowing the prices up front. Going back to some of the earlier language, informed choice, being able to really know beforehand what it is that we are looking to receive and what the price attributed to that is. What's the value exchange going to look like? So you talked a lot about consumerism. Did that play a lot into the original theory of how this would work? Because we're also seeing, whether it's with employers or researchers and reporters, what was the combination effect that was aiming to happen from a lot of this initial thought and direction? **Randy Pate:** I'll just speak for myself and my own evolution on this topic. I come from somewhat of a payer background. I worked for Blue Cross Blue Shield, HCSC, and it's five states, Blue Cross plans. And I have that mindset. At the same time, I don't only come from that mindset. I also try to think about the provider perspective, the patient perspective, the device manufacturer, the drug makers, all of it, because it's all important to how the whole system functions or doesn't function. But when I go back even before price transparency, the regulations and the executive orders and all of that, I think about how, unfortunately, we've had some accidental steps in our health care system's development, all for very good intentions over the years, but they have caused some problems that we're now really seeing come to fruition. We spend almost 20 percent of our GDP on health care, which is much higher than any other developed country. **Randy Pate:** We have really good care. If you have cancer, if you have heart disease, if you have some of these tough conditions, we have very good care. But sometimes the access is spotty, or the quality, we don't know what we're getting a lot of times before we go in. These are problems that didn't just come about in 2019 when we were starting on this path to this regulation. It goes back to World War Two, post-World War Two, when the IRS came out and said any health care or health insurance that is provided by an employer is tax-advantaged. So it was basically not taxed by the federal government, whether on the employer side for the contributions they make to the employees' premiums or on the employee side. And out of that, it became this benefit that came along with employment. And I think that's a good thing. **Randy Pate:** It has a lot of good aspects to it. But when people think about health care and health insurance, it's almost like you get to buy a ticket to Disney World. Once you get that ticket — it's not true anymore, but it used to be that when you got your ticket to Disney World and went in and rode the rides, you got to ride all the rides for free. And so it's this thought process that we've been under for a long, long time, where health care is just something that, I've got my insurance card, I go in, and everything should be free. I'm not saying that I think people love to go to the hospital and ride an MRI machine like a roller coaster. I'm not saying that. But from an economic incentive perspective, it turns things in a bad direction. In other words, it's something that somebody else pays for. It's not something I have to think about. **Randy Pate:** And of course, then we're like, well, who wants to have costs be a barrier to their care? And that's true, except now we're seeing health care year after year outpace inflation in the general market. Whereas inflation most years is a couple of points, three percent, maybe four or five percent in a really bad year, health care can be regularly seven, eight, nine percent growth, and that just is not sustainable. So we have to figure out some way to deal with it. Now, along with that has been this whole fee-for-service model that our health care system is based on. And a fee-for-service model just means that you go to the doctor, you get care, whatever the doctor prescribes, and then they send a claim to the insurance company or to Medicare, and then they get paid a fee back. **Randy Pate:** Well, nothing wrong with that either. It's the most logical way to structure something. However, it does happen to often carry the incentive that the more care is delivered, regardless of whether that care is good or bad, the more the provider gets paid. And now we're seeing the system for the last 30 years has been trying to get away from that. With things like health maintenance organizations, ACOs, whether it's upside and downside risk for the providers, there are all these ways to dance around, in my opinion, consumerism, which is where the rubber hits the road. I'm using my money, I make my decisions, I'm making those tradeoffs, and there's nobody better suited than me to do that. **Randy Pate:** So, very long answer. But I think it's important as a foundation, because price transparency doesn't solve all of these other issues that we've been living under for a long time in our health care system. But you have to have it as a start. **Andrew Gordon:** Love that, and completely agree with and hear the affordability challenges that we're seeing, the incentives that need to be unpacked and understood, and then making sure that they're aligned for the folks that are receiving and delivering the care and being able to pay for it as well. So switching gears a little bit over to the policy and legislative side, the 2019 executive order set this in motion. Walk us through what happens between an order landing on a desk and a final rule going out the door. I feel like there are a lot of listeners who aren't really sure what this process looks like. **Randy Pate:** When you think about the federal government, it's really a lot like you would think about it from the outside. You've got the White House, the folks over there, they're at the top of the mountain in terms of federal government. And you've got all those agencies, and we're all doing our work. We have our programs and our policies, and we're carrying things out. And the first reaction when an executive order like that comes down, someone calls you or you get a text or an email, and the first reaction is panic. Like, oh no, what do I have to do? But in all seriousness, I came from a payer background, and sitting in my seat, I'd always thought, well, prices and a negotiated rate between hospitals and health care plans, or between doctors and health care plans, that's a matter of contract. It's private contract. And that's part of the value that health insurance companies bring, that they're able to negotiate lower prices because they bring a lot of membership, a lot of patients, to that provider. So my mindset was that these prices are a contractual arrangement. **Randy Pate:** And now we're going to have to start requiring the companies to disclose their secret sauce for how they put together their networks, how they make prices attractive, how they maybe give a little here and take a little more there to get to your product that people buy. And so I would say I had a strong bias against the government intervening and saying, OK, we're going to open up the doors on this. But then I would just say, as a team at CMS, we knew this executive order is coming down. We need to comply with this. And so we started doing research. We started holding listening sessions with different players. And that's one of the great things about being in the federal government, is you can really be a convener and hear all these different perspectives. We heard from patient groups, insurance companies. We heard from employer groups that are sponsoring care for big employers like Lockheed Martin and Walmart, these big players. And we heard from all across the sampling of these different groups. **Randy Pate:** The message that we started to hear was, it's not easy. There could be some pitfalls with doing this. It would be very burdensome on insurance companies to do this. But particularly the employers were really interested in getting this data, because they believed these were things that had been hidden behind a wall for them for so long. They were basically contracting out for these health care services with third party administrators and for the members, and then they couldn't receive that feedback on, well, what is the price we're paying for this episode of care, for this service? And as purchasers, they could really move the needle if they had that data, if they had that information. So I would say that was one of the things that really changed my mind about doing this regulation. And then from there, I would say it is a lot of teamwork. **Randy Pate:** We worked with federal partners. We had the Department of Labor. We had the Treasury. We had, of course, experts at CMS. And then we had our White House, and they're like a quarterback, coordinating the whole thing. So my team took the lead on the drafting of the regulation, the proposed rule. First we put out a proposed rule and then you get public comment on it. So I would say very deliberative process. We're doing listening sessions. We're meeting together as a federal partnership across all the different agencies, putting out a draft of something we think is a starting point, taking into account all of the public comments, all of what the public has to say in writing, and then issuing a final rule. **Randy Pate:** And I'll still say, in an area as complicated as price transparency, and something that had never been done before, even with all of that, we knew we were going to miss on a lot of things. And we knew that we were taking a stab in the dark on a lot of things. So, really complicated area. But we wanted to start down the pathway of getting these prices into the hands of the consumers and the employers. **Andrew Gordon:** Great, and amazing to hear on the focus groups, the public commentary, a lot of that collaborative effort to be able to put something together. It's incredibly valuable. And I also will say 100 percent on the complexity of things, it can be very difficult. Pricing in health care, the factors that can influence it, understanding the whole supply chain there, it is very difficult. And it's something that as you guys were drafting it, working together with other people, making sure that you were spending that time to put in that critical thinking, makes a lot of sense. So what would you say in that first pass? What are some things that you guys really knocked out of the park on, that you got right? **Randy Pate:** I don't know if we knocked it out of the park on anything other than taking a step and having it really happen for the first time. And I would say that required, I mean, it was very burdensome. It is very burdensome for insurance companies, for example, to go through all of the millions of claims that they have and put them in a format that can be published. And it was two things. It was, you publish the negotiated rates, and then it was also, you have to update your own consumer tool. If you're an insurance company, you have to have a consumer tool so that me as an enrollee can go in and put in the service I want and then see, OK, is this in network? Where am I on the deductibles? How much out of pocket am I likely to get? So we really updated how those were supposed to operate. **Randy Pate:** I would say one of the biggest rewards out of it was after I'd left the administration, when the regulations started to be effective. There was a final regulation and then they became effective starting about six months to a year later. And when I started saying, hey, the insurance companies are doing this, they're actually posting real data, we got something right. There was a lot of doubt, I would say, that we were going to get anything at some point, just because it had never been done before. But we started getting data. We started seeing companies post their rates. You could go online, whether they were readable or not. We'll get to a whole other story. But I would say those are the two biggest things, was just getting started, and then actually seeing the numbers start to come out. **Andrew Gordon:** There's a lot to be said for bringing new things to life and just the amount of work and rigor that it takes to go from zero to one. So incredible work there. And it is absolutely an iterative process as we're thinking about that and moving into how the legislation and the rules started to really get traction, get teeth. It seemed like in the first couple of years, compliance was pretty uneven. A lot of the files seemed to be unusable. Was that a surprise, or about what you'd expect from any new reporting requirement? **Randy Pate:** Well, it was about what I would expect for the complexity of what was being undertaken. So, just for example, there have been a lot of problems with the data, especially the first round. Some of these files were terabytes, or bigger than terabytes, really big. So, me on my laptop, I don't know if I have that kind of storage space or computing power to be able to download something like that. And remember, it was before AI tools came out, before they really hit it big. And so there wasn't any ability to, like ChatGPT, take all of this data and just make it really clean. I think we're getting there, but I still don't think we're there yet. But we knew there were going to be hiccups. And so we actually started off and said, look, insurance companies, you don't have to put out all of your negotiated rates yet. We're just going to do the 100 most shoppable services. And we went to a list that existed in Medicare, the services that were most susceptible to consumers being able to shop and compare. And the easy thing that always comes to my mind is MRI imaging. There are imaging centers and they are located in a lot of different places. **Randy Pate:** And you can shop and compare lab work, things like that, where they really are considered more shoppable. And then after that, the second phase was, OK, now you have to do everything. So, again, the data still has a long way to go. And I will say the other thing is, we knew that people weren't going to be able to pull all this down on their laptops, as it was, or on their smartphones. But we believed, and we are still hoping, that third party developers, companies out in Silicon Valley and smart kids with their computers, will be able to come up with tools that would allow you to have your smartphone in the doctor's office and be able to say, hey, I know you're telling me I need this, and you want me to go to this provider, but that's going to cost five thousand dollars, and this one over here costs a thousand. What do you think? These types of conversations that we just don't have today. Some people say, well, you shouldn't bring price into the conversation about health care, because it's your health. But again, that's just not how we do anything else. Even exercise classes or vitamins or supplements or gym memberships, going to the spa, people make these value judgments all the time. And just interjecting a little bit of that into the thought process, I think we'll have an outsized impact in the long run. **Andrew Gordon:** There's a lot to be said for that with medical debt as well, and just not knowing necessarily the prices beforehand, combined with potentially that mentality you talked about before of, I have insurance, so it should largely be covered. There's a lot to unpack there. And it does take some time to get through to this. When I think about the machine readable files, the goal of the policy and the legislation is to put all of this information out there so that, as you mentioned, Randy, these founders, these entrepreneurs, these technology proficient innovators can really use the information and help to translate it into those real world workflows, including in those tools that you mentioned with insurance companies, or just other third party tools that people can leverage in order to help them make greater decisions and have more information ahead of going to receive certain services. I want to talk about the gap that exists between a rate on paper and then what ends up getting paid on a claim. There is a gap there, and I'm curious to know how policy is trying to close that distance between those two worlds and how close we're getting. **Randy Pate:** Yeah, it's a great question. So just going back, one other thing on the machine readable files. I think another area where the team really hit it out of the park was the use of GitHub. So when we talk about a machine readable file, you have to have a schema, or basically a design for how each data element should look and where it should be placed. And the federal government, for the first time ever in my knowledge, used GitHub as a place for guidance and instructions to be issued on this, and then for the health insurers mostly, the tech people, to come on and ask questions. So I cannot take credit for it at all. My team came up with it. I'd never used GitHub before. **Randy Pate:** I have since started to use it. But that's another exciting thing I just wanted to throw out there. I think, honestly, Andrew, people are so jaded about our government a lot of times. And I would just say, there's a lot of reason to be jaded. There absolutely is. But at the same time, there's also a lot of good people who are doing great stuff. And that is just an example of something I would have never thought of, and the government has never really done before, but now is something that has been in place for six, seven years that people are using, and it's still evolving. **Randy Pate:** But to get to your actual question, I will say we're still not there yet at all on the translation between what a negotiated rate is before a service happens versus what the final payment is. There's legislation out there, for example. And I know the federal government on the executive branch side is pushing towards, OK, if you have a starting point, let's say you're doing something like a value based care arrangement or an alternative payment model, where instead of a fee for service, you're saying, OK, we're going to measure outcomes, or we're going to put some sort of incentive payment on the back end for controlling costs. The basic idea is that you need to be able to disclose in the transparency file, in the machine readable file, the math for how you get there. Whatever you're doing, your percentages, if it's a percentage of Medicare, you put that in there. You need to disclose the formula, and then you actually need to come up with a dollar amount right at the end of it. That's something that is not there yet. But the idea is that the consumer or the employer or whoever can look at not only the methodology if they want to, but they can also see how it works in reality for this service, for this patient. The dollar amount. **Andrew Gordon:** Right. The methodology, the standardized schema, the fact that the schema is hosted in GitHub and has allowed for people to interact with it and to see everything that's going on, brings so much validation to all of this work that's making its way, and has been making its way, into industry for quite some time. The rules put a named executive on the hook in the hospital machine readable file to attest that they are true, accurate and complete. How much would you say personal accountability changes behavior compared to a fine? **Randy Pate:** There haven't been a lot of fines issued yet. There have been a number on the hospital side, but not really on the health insurance side. I would just say, having worked at a health insurer, having to have that name, that officer, sign their name to it, it doesn't guarantee accuracy. It just creates a little more attention within the organization. You're going to tend to have real lines of accountability when you do have to have an officer sign like that. So I think it's a good thing. You could always have inaccuracies. They could be for good faith reasons. Occasionally you could have intentional gaming of it. I don't think that's going on for the most part. I just think that's another little reminder for these organizations, some of whom are huge. They have big staffs, big divisions and everything. Just to create some of those lines of accountability and make sure that somebody is getting briefed up, and when they put their name on it, they feel confident that they're not going to have egg on their face. **Andrew Gordon:** For sure. Speaking of the penalties, CMS has issued roughly 27 penalties since enforcement. Ten of them were last year, I believe, ranging from thirty thousand dollars to just over three hundred thousand. Over a thousand hospitals have received warning notices. What was the original goal for enforcement and how do you see that evolving over time? **Randy Pate:** Yeah, so with any type of new regulation like this, you have to balance a couple of things. One is you have to balance the need for people to have this information, and for the employers to have it like we talked about, which is so critical, because if you have a lack of compliance, you're never going to be able to do things like have apples to apples comparisons between how much provider A versus provider B charges for the same service, what's included in that, all these important questions. You never get the benefits of the rule unless you have enforcement and you have compliance. But at the same time, as I mentioned, it's extremely difficult for a lot of the carriers that have legacy IT systems. For example, you have a lot of acquisitions. A large insurance company goes and acquires a smaller one that has maybe some antiquated systems, or the systems won't talk to each other. And those types of things can create a lot of costs as you're trying to comply with something new like this. And so we wanted to take a very light hand to begin with, but over time, the expectation clearly is that we want to get to full compliance and we want to make sure that the intent of the rule is carried out. And so I think now you're seeing even more focus on compliance. Congress is even looking at increasing penalties and that sort of thing. A number of states are moving in that same direction. **Randy Pate:** The states have actually played a huge role in not only enacting their own versions of price transparency, but in starting to police and really make sure that the carriers in their states are complying. It's all part of the push to get towards true price transparency. **Andrew Gordon:** When I think about that too, Randy, and the enforcement, the accountability, the responsibility, we're many years in on both fronts. The two separate rules, the hospital price transparency and then the insurer with the Transparency in Coverage rules. What's your read on the quality of the information that's coming out of these files? If you want to speak to each of them separately, or just in general, would love to get an understanding of where we stand. **Randy Pate:** So honestly, I think there's still a long way to go. I think we've also come a long way. I'm not a data scientist and I'm not out there downloading JSON files and things like that, but just from my understanding, reading some of the media articles and what some of the commentators are saying, it seems like there's been a big leap forward starting earlier this year. So CMS issued some new guidance around what the files should contain, what the data should look like, last fall. And they said by early this year, we're going to start enforcing that. And I just did a little spot check of some of the biggest carriers, pulled up some of the files. And whereas in the past I was completely lost, this time I would say I was a little bit less lost. It did feel like this looks cleaner. This looks more, I can keyword search and things, and it is actually bringing up something that makes sense. **Randy Pate:** I think there's a proposed rule that CMS has out now that goes even further in cleaning up the data, reducing the file size, getting rid of some of the redundancy in some of the files. So that'll be another big step when that comes to fruition. But I think it has gotten much better over the course of this last year in particular. **Andrew Gordon:** So I want to shift gears a little bit to the different stakeholders and groups that are engaging. You had mentioned earlier, Randy, that employers were certainly at the forefront, were top of mind when drafting this, and were also engaged in those discussions and the public commentary that's coming in. Tell me a little bit about how they have shown up. Are we noticing that it is a small circle of sophisticated plan sponsors? Is it more widespread engagement? What are we thinking in that department? **Randy Pate:** I think there's a lot of dedication and fervor to get this done and to do it in a way that has impact, that really moves the needle. I think it's one of these very tough problems, and you're talking about all these different organizations around the country that you're trying to bring along to this new way of thinking, and this new environment really that we're trying to create with price transparency. But I mentioned the employer groups before. I think they're continuing to push from their perspective. I've been struck by just the number of technologists and the data science people that are working at some of these companies. They are on top of this. They know every aspect of the MRFs. They have very strong opinions on how do you make this more usable? How do you make it clear what's in network versus what's out of network? How do you make it clear when there's an alternative payment arrangement, how that should be displayed? **Randy Pate:** Another big thing is prescription drugs. That's something I didn't mention. The prescription drug file really has not been implemented yet. So that means we're not seeing prices for prescription drugs posted yet. And so I think there's a push to get that done, possibly by the end of the year, through legislation. So the stakeholder community I think has been really engaged, and it's only getting more engaged, and I would say at a more detailed level, as these files continue to evolve. And so that's been really interesting to see. And I would say when you look at the polling on this, it's a bipartisan issue, it's a nonpartisan issue, really. And 90 percent of Republicans and Democrats together agree that we need this. So it's one of these things where I don't know if there's any other issue across the whole spectrum, whether it's domestic policy or foreign policy, where there's that level of support. So let's hope that our leaders, the Congress and the administration, listen and really follow through on it. **Andrew Gordon:** I want to parlay off that comment with the bipartisan support, and excellent points to that. It is rare sometimes to see this. What would you say can explain that unwavering support across the board that's been received for this kind of stuff? **Randy Pate:** I mean, look, I think a lot of it's frustration, just to be honest. I think there's just a lot of baffling things. I'll just say, thankfully I have not used a lot of health care. I'm a health care person, but I hate to go to the doctor. But I had to go for a checkup a few months ago. And I got a bill afterwards and I thought, well, that should be zero out of pocket, because the part of the ACA that says preventive care, there's no cost sharing. But I got a bill. So I click on it and it says you can see your invoice and see what you're actually charged for. And this is after the fact, not before. I click on it and it's one hundred dollars. That's the bill. OK, what's that? I click on it to find out what it's for. **Randy Pate:** And it just says pay us a hundred dollars. Basically no information, nothing about why, what. And so I think people are frustrated with that. There's no other system like that. But even some of the most frustrating consumer-facing systems out there, you think about some of the telecommunications things, trying to get your cell phone service, figure out how much your bill is. There's more transparency in that, or cable, or the airline industry, all of these, so much more transparency in that than there is in health care. And so I just think people are, then multiply that little problem, that little tiny problem I had, for some people multiplied by thousands and thousands of dollars. And not only that, but they're in a situation where they had no idea going in it was going to cost anything like that. So I honestly think frustration is one of the biggest causes of it. But I also think that people do realize that one way or another, it's up to all of us individually. We can't continue to punt and hand off personal decisions. We have information now. **Randy Pate:** We should have information at the tip of our fingers all the time and we should be able to make better decisions. So we just need information to do it. **Andrew Gordon:** I'd love to shift gears a little bit and do some forward looking, some forecasting. If transparency works the way that it was drawn up, the way that we've been iterating on it, and with some of the things coming down the pipeline here, what does the market look like in five years? **Randy Pate:** I hope the market looks like a real consumer market where people are able to know in advance how much something costs. They have the ability to see it. They have the ability to compare quality information. What are the outcomes? They have the ability to go to the place that they think, with the help of lots of electronic and in-person expertise and otherwise, is going to be the best decision for themselves and their families. And I hope that that also results in competition, lowering prices, and providers of all types and insurance companies thinking differently about how are we going to get to value? How are we going to start not only just cutting costs, but improving quality at the same time? **Randy Pate:** I think it can be done. I think there's a lot of progress that can be made. I don't think any of it's easy necessarily, but in five years, I don't think we're going to be there 100 percent, but I hope we can all look back and say, hey, it's different now. **Andrew Gordon:** It's a process and it's a long game, especially in an area that's as complicated as this one, but we certainly have to pay respect to all the growth that we've seen and all the growth that we expect down the pipe. And it makes a lot of sense that we want to move toward that world where people are able to make those decisions in a very upfront, clear, controlled kind of way, because we all have budgets, we all have a certain amount of money that we're looking to or expecting to spend. And so we need to make sure that we're catering to that as best as we can. Obviously, there's a lot of emergency care and there are certain things that are nuanced in nature, which are very tough to predict ahead of time. But there are other things, to your point, with using examples like radiology or lab work or other things that fit that narrative really well. What would you tell a listener who wants to put this data to work on Monday and they're not exactly sure where to start? **Randy Pate:** That's a good question. I would not recommend going and downloading just the straight JSON files, which is sort of like an Excel file, but much more difficult to download. I would not recommend doing that. So there are states, for example, where you can go and they have their own tools to look up things. So, for example, if you're in the state of Indiana, you can go to a website, and I don't have the link, I can get it to you, but the website allows you to type in the provider that you're thinking of and then the procedure, and then see what the prices are. It even has a map where you can compare providers. I played around with it. There are a lot of private companies that have similar versions of that out. And so, honestly, depending on the service that you need, you can actually get out there and play with it. **Randy Pate:** But then I would also say, when you have that price, you should probably also call whoever it is you're thinking about. At least maybe when you get down to two, call them and make sure that that's accurate. But honestly, a lot of it's out there now and it is usable. I think we have to get the word out and we have to get people used to these tools. And I think they'll continue to get better. But right now, most people don't even know they exist. **Andrew Gordon:** For sure. Randy, there was a lot that we covered, from the origination of things through to what we're seeing today and then now where it's going. Anything else that you want to share with the audience? Maybe something I neglected to ask you, or just something that comes to mind relative to what we're seeing in this space? **Randy Pate:** No, I just try to think about this in terms of, this is information that in any other market we just take for granted. We don't even think about the fact that all of these technologies that we rely on, whether we have computers in our cars, we have computers in our hands, we have all of this advanced technology that we're using on a day to day basis. And we know how much it costs. And we're able to make decisions about it. People are smart. They're not just mindless sheep. They will make a decision, usually a very good decision, based on value. And they can figure that out. We just have to get information to them in a way that is usable. And I know we will see positive results. I'm positive. Absolutely sure of that. **Andrew Gordon:** Wonderful. So for those who are interested in reaching out to you after this episode, where would you direct them? **Randy Pate:** Sure, it's a long email address. It's just Randy at RandolphPateAdvisors.com. And that's R-A-N-D-O-L-P-H. Or you can visit my website, www.RandolphPateAdvisors.com, and contact me that way. **Andrew Gordon:** Sounds wonderful. Randy, it's been a pleasure. Thanks so much for coming on. **Randy Pate:** Thanks, Andrew. Really, really appreciate it. Enjoyed it. **Andrew Gordon:** All right, folks, that's a wrap on this episode of The Price of Healthcare. We look forward to seeing you on the next one. --- ## Introduction: Welcome to The Price of Healthcare Podcast - URL: https://payerset.com/price-of-healthcare-podcast/00-welcome/ - Published: September 4, 2026 - Author: Guests: Jerry DiMaso, Co-founder & CEO, Payerset; Jacob Little, Co-founder & CCO, Payerset - Section: The Price of Healthcare Podcast The show starts where the company did. Matt Phillips sits down with Payerset co-founders Jerry DiMaso and Jacob Little to talk about why they launched The Price Transparency Project and what listeners can expect from the conversations ahead. They reflect on how price transparency has changed since the Transparency in Coverage data first landed in 2022, from early confusion and technical obstacles to a source of insight the whole market now draws on, and on the continued need for education, advocacy, and open dialogue between groups that too often operate apart. ## Transcript **Matt Phillips:** Hello, and welcome to the Price of Healthcare podcast. This is an initiative of the Price Transparency Project that we've recently launched as an avenue for us to create advocacy, policy tips, best practices, really for anyone working with healthcare pricing data. And so today I'm with Jacob Little and Jerry DiMaso, co-founders of Payerset. **Jacob Little:** Thank you. **Matt Phillips:** Want to give a little intro of yourselves? **Jacob Little:** Absolutely. My name is Jacob. I started this with Jerry when all of this began with the tick data in July of 2022. It's been an amazing journey since then, getting this information into people's hands, helping so many different organizations with it. And we're just really excited to see where price transparency is today in 2026, as this is being recorded, compared to when it started. So it's been a wonderful journey. **Jerry DiMaso:** I'm Jerry DiMaso, Jacob's co-founder. Very excited to get this started with the Price Transparency Project, trying to get this out there for everybody. **Matt Phillips:** All right. So starting a price transparency company, Payerset, it's kind of always been a mix of policy and advocacy along with company building, building a technology company. Why did it make sense to break out Price Transparency Project to its own thing? **Jacob Little:** There's still so much education that needs to happen. I was at a conference, this really sweet person was talking about price transparency. It was a conference for hospital financial leaders. And this really sweet person approached me after I had done a talk and said, hey, is what you're doing legal? Is this information supposed to be out there? And I was like, well, I guess we have a lot of work to do. So there's still, I think, a lot of people in the space that either think that don't know about it at all, a nd are really surprised that the contracted rates are out there and can be accessed and used. They don't even realize it's being used against them sometimes, which is even worse. And then if they do know, there's just been a lot of, I think, negativity and frustration because it was much harder than everybody thought it was going to be. But guess what? Surprise, surprise. Healthcare pricing is complicated, right? It's a complex system that has built up over many, many years. And luckily, we're making all of that simple. But we needed to start with education and we needed a vehicle to do that in a really focused way that wasn't about the tools we're building or the solutions we're delivering, just about making sure that there was a community that could help each other, that knew where the policy was, that knew how this could be used. **Jerry DiMaso:** And something that was separate from a company, separate from technology, just more about helping people understand where the price transparency data is, where it's going. So we'll talk a little bit about policy. We'll talk a little bit about where we were with price transparency, where it first came out and the journey it's gone through, the schema 1.0, then to schema 2.0, now schema 3.0 is going to be coming out soon, which we're really, really excited about. **Matt Phillips:** A little teaser. We do have one of the originators of the transparency and coverage legislation. That's going to be a guest. But speaking of policy, you guys were both just recently in D.C. meeting with various leaders talking about schema 3.0. I mean, maybe give us a little bit of taste. Like, I know you can't talk that much about in the room, but what's coming? Highlights. **Jerry DiMaso:** There's actually a lot. There's actually a lot coming. Schema 2.0 was a huge step forward in terms of just having one continued investment and reinvestment in the price transparency data in the first place. So there was a schema 1.0 came out a couple of years in between, had a lot of learnings, a lot of different technical snags and the carriers, learning how to publish, learning how to turn their contracts into data, which, you know, they're written long documents that are very complicated. So kind of turning those into a data set. So there was a bit of a learning curve there with the posting. Schema 2.0 came out, added a couple of new fields that we really needed to make the data even more useful. It also allowed the payers kind of an opportunity to refresh and refresh their processes. And so we saw a lot of cleanup in the data just in the last few months, which is really exciting. Schema 3.0 is going to be adding a lot more capability from an analytics standpoint to the data. So we're looking at potentially getting some utilization data. We're looking at even just more semantic meaning behind some of the provider groupings and trying to get more information about carve-outs and outliers and things like that, because contracts are pretty complicated. So ultimately trying to get to, can we codify a contract into a data set and make that available and useful for everybody? So it's very exciting to be there. The final rule is actually undergoing review now. So we will have some information on that soon in the coming weeks and months. That's a very exciting time. So it's a very exciting time for price transparency. **Matt Phillips:** I know you're excited about the recent hospital price transparency updates too. **Jacob Little:** Yeah, it's actually a really important point because when you say the word price transparency, depending who you're talking to in the industry, as I said earlier, they either don't know what it is or depending on who they are, they're associating it with maybe the thing that you're not talking about. So if you talk to somebody in a hospital about price transparency, they're going to be thinking about their regulation. Oh yeah, those are those files that we have to put together and that's so hard. And oh, there was another update and it has to be on our website. It has to be linked in the footer, all of those things. The transparency and coverage rule that affects commercial insurers is a completely different rule, different enforcement, different schema, completely different. That's coming out of the insurance company's actual systems and being populated. So that when we talk about 3.0, we're talking about that from the commercial insurers out of their system. So there's kind of two branches of price transparency. And I think there is a vision that over time they will be able to kind of at least compliment, talk to each other, say the same thing. We're not there yet, but they can be used in a really powerful way to triangulate and kind of understand. And there's a lot of interesting contract language that is in the hospital data today that is not in the in the data from the insurer. So I think that's really, really exciting. And there's just so much movement right now. **Matt Phillips:** Yeah, a lot going on. All right. So just talking about price transparency project. So we'll wrap up here soon. But what can people expect? And really, I guess maybe the first part of that is who are we even trying to talk to? Who are the different stakeholders that we're really building this for? **Jacob Little:** It's really just anybody in the healthcare ecosystem that wants to understand prices. That goes for patients, patients really above all. We're trying to enable the care delivery organizations. Some people call them providers. We're enabling employers. There's so many employers that are self-funding insurance. And so there's just a lot of education. There's a lot of policy happening kind of separate from this price transparency rule that's affecting kind of what they can see. Are they even allowed to see claims for the things that they're paying for? It's a whole other topic. We're going to be talking about all of that. And then patients from an education perspective, understanding their EOB, advanced EOB, understanding their actual bill. What does it all mean? Why is the gross charge, why is the charge different than what the insurance company is reimbursing to the care delivery organization? So there's just so much. And what we're really trying to do is bring all of those perspectives together to get on the same page. Because if we can't get on the same page, if everybody's just on the opposite sides of the aisle kind of pointing at each other and, oh, I think you're the problem, you're the one making health care in this country expensive. We're not going to get anywhere. And we all know, right, the situation now is untenable. This is not sustainable. So that's really who we're trying to help. **Matt Phillips:** Yeah. You know, before we wrap up, do you have anything else you want to share with the community? **Jerry DiMaso:** If we can get real pricing out there for everybody and if people can predict what their pricing is going to be for any given health care service or anything that they need, ultimately that's going to help kind of at least flatten out the market a little bit and start to turn it into an actual market where you can shop around for health care and you can understand kind of what the pricing is going to be before you get a procedure. Right now, that's kind of difficult, but there's a lot of legislation coming out. This is a bipartisan effort in Washington, which is a really, really important thing. It's definitely a top focus. A lot of the employers are struggling. Premiums are going up. Care costs are going up for care delivery organizations. This whole concept of transparency is eventually going to allow us to lead to deregulation in a lot of places. The more transparent people are, the more transparency we have. We can deregulate and reduce the administrative burden on care delivery organizations, on carriers. And that's going to ultimately drive the cost down. **Matt Phillips:** I love the call on bipartisan. I love the call out on different perspectives, and that's really what this is about is bringing together different voices that sometimes can be in echo chambers. **Jacob Little:** That's right. Oh, there are very serious echo chambers. We go to all the conferences representing the self-funded employers, representing the hospitals. Everybody has a slightly different perspective. There was a conversation with somebody that led policy and a hospital leader. And the policy expert said, hey, well, I think all all hospitals should get paid 140 percent of Medicare no matter what. And then the hospital leader said, well, my commercial mix is only 40 percent. And so if that happened, our independent hospital would go out of business. And so do you think it's going to make health care cheaper or more expensive if one giant system just buys up all of the independent system? **Matt Phillips:** Which is happening in that market, because we know what market that is. **Jacob Little:** Yes. Then the policy person was like, that's a really good point. Let's keep talking. And they shared information. And that's what we want to do at scale. **Matt Phillips:** Yeah, I think that's a beautiful, beautiful way to sum it up of what we're trying to do here. So thank you both for taking the time to do this. And thank you all for listening. Episode one is actually out now. So go take a listen. --- # Insights - Articles --- ## Introducing The Price of Healthcare Podcast - URL: https://payerset.com/post/introducing-the-price-of-healthcare-podcast/ - Published: September 7, 2026 - Author: Payerset Team - Section: News The Price Transparency Project has a new home for the conversations we've been having off the record for years. We're excited to announce **The Price of Healthcare Podcast**.

Conversations with the brightest minds in healthcare finance.

## Who you'll hear from We want to bring together different perspectives from people who are working to create a functional healthcare market:

Providers

Health system CFOs, managed care and revenue cycle leaders, and people at the forefront of healthcare finance innovation.

Employers

Self-funded employers, benefits advisors, and the plan fiduciaries who are fighting to rein in ever-growing costs.

Advocates and policy makers

Researchers, journalists, and the analysts shining light on a broken system to influence change.

Each episode will go deep with leaders across the spectrum of healthcare finance. You'll hear what it's like to be at the table in a real negotiation, the stories behind policy, and evidence that change can happen when employers are equipped to ask the right questions. ## Why now Five years ago this show could not have existed. Hospitals have had to publish their negotiated rates since 2021, and every commercial payer has had to publish theirs, monthly, since 2022. Those payer files now cover roughly [1.7 million care-delivery NPIs](/pricetransparencyproject/by-the-numbers/), and hospital compliance has climbed from 27% in 2021 to nearly universal today. The data finally got good enough to act on, and a whole profession is learning how. There's still such a need for awareness that the right data is out there and usable, and that people are already seeing meaningful change. More than anything, we hope to highlight that no one side of the house is going to fix healthcare pricing. It begins with listening to every stakeholder. Only then can we learn from each other, compromise, and build the healthcare system America deserves. Our co-founders, Jerry DiMaso and Jacob Little, sat down to talk through exactly that: why we started The Price Transparency Project, why a podcast is the right way to carry it forward, and what they hope comes out of these conversations. Start here.
## Where to listen Episode one is live. You can find it on [the show page](/price-of-healthcare-podcast/) alongside every episode that follows, each with its full transcript and show notes the day it publishes. You can also listen wherever you already get your podcasts. We're on Spotify, Apple Podcasts, and YouTube. Subscribing to the Project newsletter is the surest way to catch each new episode as it drops. If there's someone you think we should talk to, or a topic you want us to take on, email us at [info@payerset.com](mailto:info@payerset.com). The best episodes are going to come from the people listening.
Meet The Price of Healthcare Podcast →
--- ## Introducing Employer Rate Intelligence - URL: https://payerset.com/post/payerset-launches-free-employer-plan-benchmarking-tool/ - Published: September 2, 2026 - Author: Payerset Team - Section: News A self-funded plan in Memphis pays 0.83x Medicare for a panel of common services. A plan in Seattle pays 1.75x Medicare for the same kinds of care. Both plans price within one percent of their local market, and both could fairly be told their network is competitive. Neither employer had a practical way to see this until now. Not because the data was secret, but because nobody had made it readable.
Access your free benchmark →
## The data that was always there Under the federal Transparency in Coverage rule, every health plan's negotiated in-network rates are published in machine-readable files. That includes the rates a third-party administrator negotiates on behalf of a self-funded employer, for every in-network provider, by billing code. Enforcement began July 1, 2022, and the files refresh monthly. The responsibility for this disclosure sits with the plan. A self-funded employer can delegate the posting to its administrator, and nearly all of them do, but the compliance obligation stays with the plan sponsor. Penalties for noncompliance can reach $100 per day, per violation, per affected individual. So the rates exist, they are legally required to be public, and the plan sponsor is accountable for them being posted. Yet ask a room of benefits leaders whether they have seen their own plan's published rates, and most of them will tell you they did not know the files existed. ## Why nobody looked The honest answer is scale. The payer transparency dataset is the largest published healthcare dataset in existence, on the order of trillions of rows per quarter. Every carrier organizes its files differently. Aetna alone publishes thousands of separate files, with the actual negotiated rates scattered across them. Opening one file can exhaust a laptop's memory before a single question gets answered. Most organizations that process this data cherry-pick the files they think matter. Payerset has taken the opposite approach since 2022: we collect every file each payer posts, every month, and keep full snapshots in perpetuity. Individual plans, group plans, fully insured, self-insured, ACA. All of it. That decision looked expensive at the time. It is the reason the analysis below is possible at all. ## What we built We took roughly 130,000 self-funded plan sponsors, identified their plans with the large administrators, and turned the published rates into a report anyone can read. Each Employer Rate Intelligence report shows a plan's overall position against the market: what the plan's negotiated rates look like next to what other carriers pay the same providers, in the same city, for the same services. It shows the plan against Medicare. It breaks both comparisons down by service line, from maternity to imaging to specialty drugs, and plots every benchmarked billing code against the market. The reports are free. The underlying report data is downloadable, also free. There is no registration wall and no sales call. Search for an employer at [payerset.com/employer-rate-intelligence](https://payerset.com/employer-rate-intelligence/) and the report is simply there. We are not showing anyone anything that is not already on the open internet. We visualized what the law already made public, because a disclosure nobody can read is not really a disclosure. ## How this was measured Every report is computed from public sources: the Transparency in Coverage files for negotiated rates, Department of Labor Form 5500 filings for employer identity and headquarters, NPPES for provider identity, and CMS fee schedules for Medicare benchmarks. The reports cover a fixed panel of roughly 500 high-impact billing codes drawn from national commercial utilization. Rates must pass eligibility checks before aggregation: fee-for-service arrangements, standard modifiers, valid provider NPIs. Each provider and code combination is compared against a rate-count-weighted benchmark across the major payers we process, matched to the same provider and the same service to reduce distortion from provider mix. Everything rolls up as medians, so no single outlier rate drives a headline number. The public reports reflect the employer's headquarters market rather than every employee location, and payer-published rates can include stale entries. The full methodology, including its limitations, is published alongside the reports. We would rather be checked than trusted. ## Reading the shape of the data The plan-level numbers cluster tightly around the market average. Minus one percent. Minus two. Plus zero. Employer after employer lands within a rounding error of "at market." The service lines underneath tell a different story. In one large plan's report, emergency and urgent care runs 48.9 percent above what other carriers pay the same providers, while imaging runs below market and specialty drugs sit near 150 percent of Medicare. Another plan shows maternity deeply discounted and chronic care near 208 percent of Medicare. Big swings in both directions, netting out to almost exactly zero. Maybe that is simply how large portfolios of rates behave. Maybe it reflects how networks get assembled, with visible discounts in the categories employers ask about and quiet markups where they do not look. The pattern is consistent enough to deserve an explanation, and we are not going to pretend we have the complete one. This is part of why the reports are free. The people best equipped to interrogate this data, the benefits consultants, the plan auditors, the actuaries, the researchers, have never had it in usable form. Now they do. ## What this means for plan sponsors Health benefits are compensation. Under ERISA, the plan sponsor is a fiduciary of that money, held to the same standard the industry long ago accepted for retirement plans. A new wave of lawsuits against large employers, whatever the outcome of any individual case, is testing a single question: did the sponsor monitor what its plan paid? For years, a sponsor could honestly answer that the data was unreachable. Claims data locked behind restrictive contracts and months of back and forth. Rates known only to the administrator. That answer is expiring, because the rates are public and now they are legible. A reasonable starting checklist costs nothing: - Look up your plan's report and see where it lands against the market and Medicare. - Check which service lines run above market, and by how much. - Verify that your administrator is actually posting complete, current files for your plan, since the compliance exposure is yours. - Bring the report to your broker and ask them to walk you through it. The employers writing the checks have been the last to see the prices. For the first step in fixing healthcare's asymmetry, the price of admission is now zero. ## Where this is headed Transparency cannot only serve the largest health systems and carriers. It has to reach employers large and small, providers large and small, and ultimately patients. A market needs real prices, and for the first time the real prices are visible. The reports refresh quarterly with each data cycle. If you want to see your plan against your own claims data, or see yourself against a cohort of similar organizations, we can go deeper. But start with what is free. Your plan's rates are on the internet. They have been for years. Go look: [payerset.com/employer-rate-intelligence](https://payerset.com/employer-rate-intelligence/) --- ## The 2026 Price Transparency Field Guide Is Here - URL: https://payerset.com/post/the-2026-price-transparency-field-guide-is-here/ - Published: June 21, 2026 - Author: Payerset Team - Section: News We're very excited to introduce you to the first flagship resource from The Price Transparency Project. It's called **The 2026 Price Transparency Field Guide**, and we debuted it at HFMA earlier this month. It's been creating a lot of buzz. If you work on the finance or managed care side of a health system, you've watched price transparency move from a compliance checkbox into a strategic asset. The industry changes rapidly, and the Field Guide helps leaders in healthcare finance adapt to those changes and prepare for what's coming next. ## Why we built it **Our goal was to create the best resource a healthcare finance professional could pick up on this subject.** We wanted something short and usable: the new CMS standards and the strategies we watch leading managed care teams run, grounded in the latest data and compressed into a guide you can finish over a coffee. By the time you close it, you'll know what your peers are doing with these files, and what payers already know. Payer files now cover roughly 1.7 million care-delivery NPIs. And as of 2026, nearly every hospital in the country has posted a machine-readable file with rates a named executive has attested are true, up from 27% full compliance in 2021. The data finally got good enough to act on, and the guide is about acting on it before your competitors and payers do. ## What's inside A few of the things you'll find inside the guide: - **The day the single-code comparison stopped working.** We walk through a real chest-pain ED visit where one hospital looked like it out-earned its competitor on the 99284 facility fee. Build the full clinical bundle around that visit, and the conclusion flips: the same hospital was paid about $249 less per visit once every line item was counted. We show why single-code benchmarking misleads, and how to bundle instead. - **The maternity rates that weren't there.** One of the largest systems in the NY metro was prepping for a negotiation and found a top-five competitor with zero maternity and OB/GYN rates on file. The rates existed. They were sitting in an AP-DRG structure nobody without the contract had ever seen, running 3 to 4 times the market benchmark. We explain where the highest-dollar carve-outs hide and how to surface them before a negotiation, not after. - **A negotiation playbook you can run before the payer does.** Payers now arrive at renewals holding their own transparency analysis. We lay out the five-step process leading managed care teams use to build the counter-narrative first, with two 2026 case studies: a hospital that turned a payer's 15% overpayment claim into a roughly 2% reality and avoided the cut, and a system that won a rate increase on a growth service line sitting 35% below market. - **What's actually changing in the rules.** Schema 2.0 went live February 2. Attestation enforcement, where a named senior executive at every hospital signs that the rates are true, accurate, and complete, began April 1. And the proposed Schema 3.0 could collapse fifty redundant rate files into one per network, while adding utilization, taxonomy, and change-log files that don't exist anywhere today. We break down what each change means for the people who pull these files, and we look ahead to the 2028 wave of standardized drug pricing data that's already reshaping fiduciary expectations. ## Leaders are already using it The response since we started circulating print copies at the HFMA Annual Conference has been better than we hoped. CFOs, managed care leaders, and benefits advisors have already given some incredible feedback. The strategies and case studies inside come from the same work we do alongside leading health systems and consulting firms preparing for real negotiations. We didn't want this to live behind a paywall, so we've made it available for free. Whoever sits across the table from you at the next renewal is already reading this data. This guide helps ensure you're reading (and using) it better.
Download your copy of The 2026 Price Transparency Field Guide →
--- ## Introducing The Price Transparency Project - URL: https://payerset.com/post/introducing-the-price-transparency-project/ - Published: June 2, 2026 - Author: Payerset Team - Section: News Our favorite part of what we do at Payerset is learning from our customers and the broader ecosystem. Every day, the leading minds in healthcare are working to make the vision of a functioning healthcare market a reality. We have the honor of talking, sharing, and learning from so many of these leaders, but we've never had a good way to share that with the community. **In that vein, we're proud to announce The Price Transparency Project**: a place where we can share practical guides and best practices, highlight the leaders working on the ground every day, and advocate for the change we all want to see. Our goal is to make this a resource for the entire community. There's a lot coming over the next couple of months: a podcast to showcase the community, research to advance price transparency, policy advocacy and updates, practical guides for leaders and analysts, and much more. ## First up: the 2026 Price Transparency Field Guide Our first drop is the 2026 Price Transparency Field Guide. Inside, you'll find direct lessons and key themes for getting the most out of price transparency data in 2026.
Sign up at the Price Transparency Project →
We're honored to build with you all and we'll see you out there. --- ## Putting Price Transparency Data to Work: Highlights From Our Relentless Health Value Episode - URL: https://payerset.com/post/putting-price-transparency-data-to-work-highlights-from-our-relentless-health-value-episode/ - Published: April 9, 2026 - Author: Matt Phillips - Section: News Several conversations about healthcare price transparency circulate at the policy level: what the rules require, who has complied, and what enforcement looks like. Equally important is what can happen with the data once it is in your hands. We were excited to have our CEO, Jerry DiMaso, join Stacey Richter on Relentless Health Value Episode 506 to work through exactly that. Catch the full conversation on the [Relentless Health Value podcast](https://relentlesshealthvalue.com/episode/ep506-how-other-employers-shareholders-and-clinics-are-using-price-transparency-data-and-its-an-arms-race-with-jerry-dimaso). What follows distills the most actionable parts of that conversation for plan sponsors and providers. ## Where the data comes from In 2019, hospitals were required to publish their gross charges, discounted cash prices, and negotiated rates with carriers. In 2022, carriers had to follow, publishing their own negotiated rates through machine-readable files. The result is a dataset that did not exist a few years ago: what payers have actually agreed to pay, across carriers, plans, and provider organizations, available to anyone who knows how to access and interpret it. For self-insured employers and union plans, this is a meaningful shift. You can search your own plan by EIN to see what your carrier has negotiated on your behalf, compare that against other employers in your industry, and for the first time, do that without asking your TPA to grade its own homework. ## What plan sponsors can do with it ### 1) Benchmark against peers When you search by EIN, you can pull your own plan's negotiated rates and compare them directly against other companies operating in your space. The disparities can be significant. If a competitor is receiving meaningfully better rates from the same carrier, that is a data point worth knowing before your next contract discussion. ### 2) Identify high-cost codes Not all billing codes are equal in terms of volume or spend. Infusions, musculoskeletal procedures, and a handful of other service categories often account for a disproportionate share of plan costs. Transparency data lets you pinpoint the specific codes where you are paying above market, so your TPA can go back to providers and negotiate with something more specific than a request for a better overall discount. ### 3) See through the aggregated discount conversation A TPA showing you a 90% discount across the board may be accurate on codes that rarely get used and significantly less accurate on the codes that drive most of your spend. You can now see both the charged amount and the allowed amount at the code level, which is enough to validate whether the headline number reflects what is actually happening in your plan. From there, the actions available to plan sponsors include directing your TPA into specific renegotiations, carving out service lines for direct contracts or centers of excellence, and modeling what a different plan structure would look like for your population. All of these become more tractable when you have the rate data to ground the analysis. ## What providers can do with it For clinical organizations, the shift is about leveling a playing field that has historically favored payers. Carriers negotiate with thousands of providers and have a comprehensive picture of rates across the market, while independent practices have typically had access only to their own contracts. With everyone being able to access the price transparency data directly from insurance companies, the information asymmetry is closing. ### 1) Benchmark rates and defend your value in negotiations A small practice can now see what every carrier active in their geography is paying for every procedure code they perform. They can identify where they are under-reimbursed relative to neighboring providers, go to a carrier with specific data rather than a general request, and pair that rate data with their own outcomes and quality information to make a defensible case. Jerry shared an example of a psychiatric provider with strong patient outcomes, specifically around reintegration into the community, that was being under-reimbursed for some of the services where their performance was strongest. Having the data gave them a specific, grounded conversation with their carrier rather than a general ask for a rate increase. ### 2) Identify new revenue channels Smaller providers were sometimes unaware of other carriers active in their geography. Transparency data opens that picture up. A practice can discover contracts or carriers they were not previously working with, evaluate whether the rates make sense for their service mix, and make an informed decision about whether to pursue those relationships. ### 3) Make the case for staying independent There is a preservation angle here that does not come up enough. When independent practices lose ground on rates and eventually sell to larger health systems, all the prices go up. Keeping independent practices financially viable is good for the whole system, and transparency data gives smaller providers a better chance of making that case before they reach the point of having to sell. ## The realistic picture on where this goes Stacey raised two concerns worth addressing directly. The first is whether transparency causes prices to rise as providers discover they are being paid below market. The second is whether it creates an arms race. The more honest framing, and the one Jerry landed on, is that the most realistic outcome is a regression toward the mean. When rates are visible, extreme outliers on both ends face pressure. That is closer to how a functioning market behaves than what healthcare has had for most of the last few decades. The bigger lever may be fiduciary accountability. Plan sponsors can no longer claim they were unaware of publicly available rate data. That changes the calculus for how employers engage with their carriers and TPAs, and the responsibility runs in both directions. Carriers that know their plan sponsor clients have visibility into their rates face a different kind of accountability than they did when that information was opaque. Jerry also noted that his work with the current administration and CMS reflects a continued and renewed push for more transparency, and that data quality and compliance have both been improving. The organizations getting real value from this right now are the ones who have invested in the methodology to use it well, not just access it. Let's keep building and moving price transparency forward together. --- ## Key Updates in Price Transparency: Transparency in Coverage (TiC) Schema 2.0 - URL: https://payerset.com/post/transparency-in-coverage-schema-2-0/ - Published: October 3, 2025 - Author: Jacob Little - Section: Industry Insights ## Transparency in Coverage Schema 2.0: What Healthcare Leaders Need to Know **TL;DR** - CMS released the long-awaited Transparency in Coverage (TiC) 2.0 schema on Oct. 1, 2025. Enforcement begins Q1 2026. - Updates and clarifications from December 2025 CMS meeting provide further enhancements. - Major updates include consolidated provider group data, new plan sponsor/issuer fields, and clearer service setting codes. - Improvements reduce file size, enhance accuracy, and enable more apples-to-apples comparisons across carriers. - Bottom line: schema 2.0 is a meaningful step forward but leaves a lot of room for stronger improvements. ## December 2025 CMS Update On December 11, 2025 CMS hosted a session for solution providers and the broader ecosystem to directly address questions as well as provide a few updates since the initial announcement. Here are highlights from this update: ### Network Name - Network name will live within objects in the MRF and will reduce the dependency on file-naming conventions. - The name should contain the common provider network name recognizable by the public. - Format changed from a string to an array allowing a provider group to be associated with multiple network names without duplicating the provider group structure. This will reduce unnecessary data size increases. - CMS also emphasized a common real-world pattern: a "network" usually isn't a single provider group. Instead, multiple provider groups can share the same network name, and Schema 2.0 supports documenting that relationship by repeating the same network name across multiple provider groups. ### Clarification on use of "Additional Information" field Additional information is an open text field meant to serve as a "backstop" when: - Standardized fields don't fully express the negotiated rate logic, OR - Contractual provisions materially affect a rate but do not have dedicated schema attributes. CMS grouped common uses into categories such as: - Conditional or tiered reimbursement rules - Alternative payment methodologies - Contractual nuances CMS also noted they monitor how additional_information is used and may standardize common patterns in future schema iterations if consistent usage emerges. ### Miscellaneous **Clarity on new Severity of Illness field vs. Billing Code Modifiers** - Severity of illness is typically associated with DRG-based coding/payment contexts, and may affect negotiated rates for DRGs. - Modifiers are typically associated with CPT-based billing contexts, where modifiers may affect the negotiated rate. **Opportunity to move more metadata in the TOC vs. repeating within MRFs** - The TOC structure supports defining multiple reporting plans and pointing them to the same in-network file locations. - This is framed as a core mechanism to avoid producing multiple large in-network files that are effectively duplicates. - In Q&A, CMS addressed whether it's acceptable to have multiple in-network files with the same plan information without using a TOC. The response emphasized that if multiple files would share the same plan context/rates, the TOC structure is the intended mechanism to represent that relationship and avoid duplication. Overall, there is room for improvement in standardization here but it is encouraging there is an ongoing dialogue on intention and best practices. ## What You Need to Know - Schema 2.0 is the first major update to TiC since September 2023. - The update consolidates provider groups, introduces plan context fields, and improves service setting reporting. - By reducing duplication and adding clarity, data is now more consistent, human-readable, and actionable. - However, out-of-network allowed amounts remain hampered by the 20-claim threshold. - Payerset will continue to track CMS updates and provide customers with schema-aligned insights. ## Transparency in Coverage 2.0 and Why It Matters When CMS announced Schema 2.0, expectations were high. Industry leaders had requested details on outliers and carveouts, better out-of-network rules, and overall improved detail to more accurately reflect payer-provider contracts. While not all of these changes were included, this release still represents progress. At a high level, TiC 2.0 brings higher-quality data, reduced file sizes, and clearer plan-level context. For CFOs and managed care leaders, this means a more reliable foundation for benchmarking rates and comparing contract terms across insurance carriers. ## Key Schema Improvements ### Provider Group Data Consolidation - **Internal references only:** Provider groups must now be defined once and referenced across the file. This should greatly reduce duplication and file size. - **Removed separate reference file:** All provider group information now resides within the in-network file, preventing dead links and missing provider data. - **Impact:** Fewer errors from dead links (e.g., Cigna, Geisinger) and easier parsing. ### New Plan Identification Fields - **Plan sponsor name:** Identifies the employer or group sponsoring the plan. - **Issuer name:** Separates carrier from plan name for clarity (e.g., "Issuer: BCBS Tennessee" vs. "Plan: Premium Plus PPO"). - **Clarified plan name field:** Now represents only the plan itself. - **Product type:** Standardized classification (HMO, PPO, EPO, etc.). While this field is not in the schema, it is proposed and documented in the notes. We hope it is included in a fast follow-up update. - **Impact:** Enables apples-to-apples comparison of plans across carriers. Previously manual workarounds (like Payerset's own categorizations) can now be automated. ### Service Setting and Place-of-Service Enhancements - **"Setting"** is a new field that now distinguishes between inpatient and outpatient. Previously, inpatient and outpatient information had to be derived from multiple fields. - **No empty allowed-amounts lists:** Enforces meaningful data if an out-of-network file exists. - **Impact:** Simplifies alignment between TiC data and claims data (e.g., Type of Bill, POS codes). ### DRG Severity (SOI) Attribute - A new attribute for Severity of Illness (SOI) within DRGs. - **Impact:** Allows more precise inpatient benchmarking by distinguishing between base and high-severity DRG payments. ## Where Schema 2.0 Fell Short - **Out-of-network threshold:** The 20-claim minimum rule remains. This means many payers can legally avoid posting OON data. While CMS removed "aggregation to a single provider," the broader problem may persist. - **Missed opportunities:** No inclusion of outlier or carveout objects, which would have captured the real nuance of contracts. - **Impact:** Transparency improves, but contract reality still lags behind. ## How to Act on This The good news is that for Payerset customers, no action is required. We will incorporate the new fields and guide you on how to apply them to your analysis. The new data will simply "flow through," and the previous schema will be snapshotted so you can access historical data and see how these schema updates have materially changed the data and the insights derived from it. ## FAQ **When does schema 2.0 enforcement start?** Feb. 2, 2026. Files published after that date must conform to the new schema. **Will schema 2.0 reduce file sizes?** Yes. Provider group references alone dramatically reduce redundancy. **Why is the out-of-network threshold still an issue?** The 20-claim rule often results in payers posting nothing. This reduces transparency rather than protecting privacy. **How does this help CFOs and contracting teams?** With standardized plan identifiers and service settings, comparisons are more reliable. Negotiation leverage improves when contracts are benchmarked accurately and consistently. **What's next?** CMS has hinted at future schema changes, including drug pricing elements in 2026. From our perspective, this TiC 2.0 update was a half measure, with much left to be desired. We hope this update is not a foreshadowing of what the Drug Price Transparency data will hold. --- ## Managed Care Contract Negotiations & Price Transparency in 2025: Lessons from the Front Line - URL: https://payerset.com/post/managed-care-contract-negotiations-price-transparency-in-2025-lessons-from-the-front-line/ - Published: September 28, 2025 - Author: Joseph Tollison - Section: Industry Insights **TL;DR** Margins are tightening, denial behavior is evolving, and employer dynamics are shifting. Organizations that win are building a proactive defense with stronger advocacy, clear accountability, smart automation, and day-to-day adaptability. The sections below open with longer-form context followed by actionable bullets that match those lessons from the front line. I recently attended the [Florida HFMA Annual meeting](https://www.hfma.org/chapters/region-5/florida/) and in addition to coming back with some sand in my suitcase, I also came back with some key insights, insights directly from the voices of hospital managed care leaders. While challenges were shared, there was an overall feeling in the room of support and of tackling these challenges together. Here's what I learned. ## Snapshot: Current State for Managed Care Leaders Hospitals and care delivery organizations are managing a payer mix that leans more heavily on Medicare and Medicaid while commercial enrollment fragments across narrow networks, ICHRAs, and self-funded plans with custom rules. Retail entrants and PE-backed ambulatory platforms continue to peel away profitable volumes, especially in surgery and advanced imaging. At the same time, insurance carriers are reshaping payment behavior through edits that short pay first and force providers to appeal, even when prior authorization exists. Teams are turning to price transparency machine-readable files (MRFs) and market analytics to anchor rates and strategy. The data is increasingly usable and, when validated against internal audits, can be accurate enough to influence managed care contract negotiations. However, variability in plan definitions and file construction still creates noise. - **Relentless payer mix pressure.** Expansion of government programs and narrower commercial options keep average reimbursement under strain. - **Disruptors siphon revenue.** Retail and PE-backed sites of care move profitable work out of hospital settings. - **Denials evolve into partial pays.** Edits reduce payment up front and push the burden of proof to care delivery orgs. - **Data becomes leverage.** Transparency data is useful but requires careful validation and standardization. ## The Very Real (and Specific) Big Problems The front line is experiencing two types of friction. First, payment tactics that are not outright denials but function like them. An example is Medicare Advantage inpatient claims initially paid at observation levels, which forces the hospital to fight back to a DRG payment. Another example is professional and facility E/M downcoding that reduces level 5 visits to lower levels and requires appeals to restore payment. Second, the constant flow of policy and provider manual changes increases administrative lift. In one state, a Provider Stability Act created stronger notification and timing standards for commercial plans, and leaders suggested similar guardrails would help elsewhere. Prior authorization remains a persistent barrier, particularly when moving patients from acute to post-acute settings, where delays for rehab and SNF transfers tie up beds and frustrate families. - **Non-denial tactics.** MA inpatient paid as observation until the DRG is earned back. E/M downcoding that must be overturned one claim at a time. - **Policy change overload.** Website-only notices and short windows drive operational whiplash. - **Prior authorization bottlenecks.** Rehab and SNF transfers stall while teams chase medical necessity reviews. - **Employer and ERISA complexity.** Self-funded plans support tight edits. State guardrails often exclude ERISA unless contracts force direct notice and mutual acceptance. ## What Is Working Right Now Organizations that are getting traction have formalized ownership, codified their positions, and tightened their operating cadence with carriers and internal partners. A centralized managed care compliance function tracks policy changes, monitors denial spikes by reason and line of business, and brings evidence into monthly Joint Operating Committee (JOC) meetings. Internal policy libraries give revenue integrity, utilization management (UM), and coding teams a consistent stance on contested topics like level of care and room and board. Contract language is being upgraded to include material change notice, quantitative limits on prepayment reviews, and clear escalation timelines. Post-acute partners are pulled into regular roundtables to improve first-pass authorization quality and move patients faster. - **Central command center.** One accountable owner for policies, denials, and payer trend analytics. - **Policy playbooks.** Board-approved internal policies for hot spots like LOC, E/M levels, and room and board. - **Stronger contracts.** Material change notice, mutual acceptance for impactful policy shifts, and limits on prepayment reviews. - **Peer collaboration.** Quarterly councils with SNF and rehab partners to improve first-pass auths and transfers. ## Practical and Impactful Plays Managed Care Leaders Can Implement This Quarter Short-term wins come from clarifying ownership, instrumenting analytics, and standardizing responses. Assign a leader who has authority across revenue cycle, UM, and contracting. Build a policy library for your top dispute areas and set three-year reviews with named owners. Triage every carrier policy into benign, conflicting, or material, and decide whether to educate, escalate, or negotiate. Track appeal overturn rates for specific edits. If a carrier's automated downcoding is overturned 70 to 80 percent of the time, present that evidence to disable the edit for your tax ID. Pilot tools that extract medical necessity from clinical notes to improve first-pass approvals for post-acute transfers. - **Appoint a compliance lead.** Give them cross-functional authority and a clear mandate. - **Stand up a policy library.** Top 10 issues first, with owners and review dates. - **Classify policy changes.** Educate, escalate, or negotiate based on materiality and contract fit. - **Instrument appeals.** Use overturn rates to challenge automated edits at the carrier. - **Improve first-pass auths.** Use tooling to surface necessity elements from notes for rehab and SNF. ## Price Transparency Data: Accurate and Useful Teams are using payer MRF-derived rate intelligence for competitive scans across neighboring counties and to set realistic ask targets for specific services. When internal managed care teams can validate the contracted rates against claims and remits, the alignment can be strong enough to guide strategy and is often accurate to the contracted penny, depending on the carrier and geography. The main caution is variability. Plan constructs and file formats can blur narrow versus broad networks and mix rates that do not actually apply to a given membership segment. For this reason, ensure that your price transparency provider is offering plan-level detail by parsing all of the MRFs (not just the files associated with the most common plan names), and ensure that your price transparency partner is validating price transparency data with real-world all-payer claims data so you can build a strategy with confidence. The data is powerful for positioning, but leaders should align on plan definitions, validate with claims, and supplement with internal cost and case-mix context. - **What works.** Detailed peer service-line and billing code benchmarks. - **What needs care.** Plan-level comparisons and validation with claims. - **How to use it.** Anchor negotiations with validated ranges and pair them with internal cost and case mix to build the right strategy and negotiation approach. In addition, don't make your negotiation strategy solely about the services you deliver today, but also about where you are planning to grow through build-outs or acquisitions. ## Commercial and Employer Dynamics Self-funded employers are paying the bill and frequently support tighter edits and stronger utilization controls. The best results come when providers bring employers into the conversation with real patient access data, delay metrics, and examples of unnecessary friction. Some large administrators operate custom plan rules for marquee employers that differ from standard policies. Contracts can reduce surprises by requiring direct notice to Managed Care, a defined review period, and mutual signature for material changes that impact payment. This is especially important when ERISA limits state-level protections. - **Expect tighter controls.** Employers and TPAs often support aggressive cost containment. - **Bring employers real-world evidence.** Access metrics and member experience data move the discussion beyond MLR. - **Contract for notice and consent.** Direct notifications, review windows, and mutual signatures for material changes. ## The Direction of Travel: Five-Year Outlook The operating model is shifting from reactive, per-click payment toward risk-bearing arrangements with real downside. Consolidation will continue on both the care delivery and carrier side. Teams that remain fee-for-service oriented without building risk capabilities will struggle. Organizations that invest in advocacy, accountability, automation, and adaptability can maintain access while protecting financial stability. There is ongoing debate about how far consolidation and integration will go, and whether public policy will introduce more universal structures. Regardless of the policy path, the common traits of resilient systems are already visible: they organize their data, operationalize their policies, and close the loop from contract language to front-line workflows. - **Consolidation accelerates.** Fewer, larger platforms on both sides of the table. - **Risk becomes standard.** Quasi-risk to full risk replaces pure per-click thinking. - **Four A's become table stakes.** Advocacy, accountability, automation, and adaptability define winners. ## A Simple Checklist to Start Tomorrow Often getting started on the right foot is the part of the challenge. And what I heard from the room of professionals living and breathing this daily was the following checklist to tackle one by one. 1. Appoint a Managed Care Compliance lead with authority across revenue cycle, UM, and contracting. 2. Build a policy library for your top 10 dispute areas and schedule three-year reviews. 3. Instrument denial analytics by carrier, reason, and service line with alerting for spikes. 4. Prepare template clauses for material change notice, prepayment review limits, and JOC escalation. 5. Pilot documentation AI and denial prediction on targeted service lines. 6. Convene a quarterly post-acute council to improve first-pass auths and transfer throughput. 7. Use transparency data accurate and detailed benchmarks tied to referral patterns and case mix to set realistic asks. ## Call to Action Reach out to Payerset for the most comprehensive price transparency data sourced directly from health plans and enriched with all-payer claims data. Build a trusted, accurate rate foundation for negotiations and strategy with plan-level detail and validation using claims that give contracting and revenue integrity teams confidence. Contact Payerset to see how combining price transparency and claims data delivers trusted price intelligence that can improve your next negotiation. --- ## A CFO Blueprint: What to Look for in Healthcare Price Transparency Solutions - URL: https://payerset.com/post/cfo-blueprint-healthcare-price-transparency-solutions/ - Published: September 27, 2025 - Author: Joseph Tollison - Section: Industry Insights Price transparency solutions for healthcare aren't simply just another compliance checkbox. For hospital CFOs, managed care leaders, and finance directors, it's the difference between negotiating blind and negotiating with clarity. The right solution helps you cut through the noise, spot hidden opportunities and move with confidence in a market where every dollar counts. But here's the challenge: not all healthcare price transparency solutions are created equal. Many make big promises but fall short when you dig into the details. So how do you know which solution will actually deliver meaningful insights you can trust? And while yes, Payerset is indeed a price transparency solution option, we did our best to take a step back and take what we have learned and heard over the years from finance leaders such as yourself to put this guide together. Our why and reason to exist continues to be driven democratizing healthcare pricing through real transparency and our hope is that this guide helps contribute and support that mission that serves as our north star. Almost 75% of CFOs in the [HFMA survey](https://www.hfma.org/finance-and-business-strategy/the-healthcare-cfo-of-the-future-turning-risk-into-opportunity/) identified strengthening payer-provider relationships as a leading focus for the next three years, either taking it on directly or entrusting their teams to drive meaningful progress. Price transparency fits into that focus and strategic need. So here's our take on the top five characteristics and the supporting questions to ask and get answers to when you're considering what's next for price transparency in your organization. ## 1. Look Beyond Price Transparency Compliance: Does It Create Real Business Value? A lot of vendors stop at "checking the box" for compliance. They parse machine-readable files (MRFs) and hand you a massive dataset, but they don't make it usable. That's not enough. You need a partner who transforms raw, chaotic files into clean, structured intelligence. Ask yourself and more importantly the price transparency solution provider you're speaking with: - Can this solution show me actual contracted rates in seconds, not hours or days? - Is this data complete? Many solutions do not acquire all of the payers' posted files because it is cost-prohibitive, resulting in missing or inaccurate reimbursement rates. - Does it reduce complexity by cleansing and formatting the data so that it is ready for analysis in Excel or a BI tool, allowing me to integrate it with my internal data? - Is it verified with real-world claims data so I can build meaningful cohort comparisons and trust the rates posted by the payers? In reading HFMA's *[The Healthcare CFO of the Future: Turning risk into opportunity](https://www.hfma.org/finance-and-business-strategy/the-healthcare-cfo-of-the-future-turning-risk-into-opportunity/)*, one of the quotes shared in the report really echoes the need to go beyond a compliance checkbox. "With our system being located between two metro areas, we want to make sure we're not only in compliance with price transparency requirements, but also that we're maintaining a competitive advantage for those services," [Kolin Huth](https://www.linkedin.com/in/kolin-huth-1285441a2/), CFO at Jackson County Regional Health Center in Maquoketa, Iowa. ## 2. Trust the Data: Is It Accurate and Auditable? Price transparency data is messy by nature. Phantom rates, zombie rates, and mismatched provider groups can easily distort the truth. If your solution isn't auditing and normalizing data, you're left with unreliable numbers. And unreliable numbers can cost millions. Look for a healthcare price transparency solution that: - Continuously audits payer files for compliance and accuracy - Flags and filters zombie rates so they do not skew results - Provides clear sourcing so you always know where the numbers come from - Retains all data over time for historical benchmarking - Does not cherry-pick payer plans or products and includes the full range of plans, both large and small This type of [complete and comprehensive data](/post/why-complete-healthcare-price-transparency-is-essential-and-what-it-takes-to-get-it-right/) builds trust. And transparency without trust isn't transparency at all. You can scope out [our payer scorecard data](https://docs.payerset.com/payers/aetna-price-transparency) which provides another layer of visibility to build trust. And feel free to [browse our data dictionary](https://docs.payerset.com/using-the-payerset-platform/data-dictionary) to see all the fields that are continuously captured in our SaaS solution. ## 3. Prioritize Speed and Usability of Price Transparency Data In the real world, you don't have hours or oftentimes even the on-staff expertise to hunt through a 10-terabyte file or wait weeks for a consultant to deliver a spreadsheet. You need answers fast, ideally in minutes, with just a few clicks. Your healthcare price transparency solution should: - Deliver instant rate lookups across payers, providers, and codes - Offer intuitive dashboards anyone on your team can use (no need for advanced data science or engineering backgrounds) - Fit seamlessly into existing workflows instead of adding new headaches Here's a good test when you're on the next demo: Think about, could your managed care team pull insights from the tool during a live negotiation? If the answer is no, it could be a signal to keep looking. ## 4. Flexibility and Built for Your Future Needs as Hospital CFO Healthcare contracts aren't static. Neither are your needs. A price transparency partner should help you tackle today's challenges and set you up for tomorrow's opportunities whether it's preparing for a contract negotiation, identifying leaked revenue or evaluating where to expand the business. When evaluating a price transparency solution look for: - Access to historical benchmarking to see how rates shift over time - Custom queries that let you slice data the way you need - Scalable infrastructure that grows with your organization's questions - A vision for the future and upcoming product roadmap enhancements that will benefit you You want a solution that adapts to your strategy, not one that boxes you in. ## 5. A True Partner, Not Just a Vendor At the end of the day, technology is only half the story. You need a partner who shares your commitment to fairness, clarity and better outcomes. Someone who doesn't hide behind jargon or black boxes, but instead gives you the confidence to take bold, informed action. So next time you hop on a price transparency solution demo take note of: - Do they explain their methods in plain language? - Are they open about their limitations as well as their strengths? - Do they treat transparency as both a product feature and a core value? - Are they able to share referencable customers? - Can they share a sample data set to provide more confidence in their offering? ## The Bottom Line: Selecting a Price Transparency Solution That's Right for Your Organization Choosing a price transparency solution is more than a procurement exercise. It's a strategic decision that can reshape how your hospital system negotiates, benchmarks, and plans for the future. The best solutions don't just simply give you more data, they give you clarity, confidence, and control. They turn a regulatory burden into a competitive advantage. At Payerset, we believe price transparency should empower, not overwhelm. That's why we transform trillions of rows of payer-provider rate data into insights your team can not just only trust but use effectively. Because when you can see clearly, you can act boldly. --- ## Why Complete Healthcare Price Transparency is Essential - And What It Takes to Get It Right - URL: https://payerset.com/post/why-complete-healthcare-price-transparency-is-essential-and-what-it-takes-to-get-it-right/ - Published: May 14, 2025 - Author: Jerry DiMaso - Section: Parsing Payer MRFs Comprehensive healthcare price transparency data has become an essential input for providers, consultants, and healthcare systems alike, helping to support fair negotiations, data driven strategic planning, and stronger financial forecasts. We outline why having the most complete healthcare price transparency data is critically important and provide a framework for avoiding the common pitfalls in using transparency data. ## Every Plan, Every Service, Every Provider ### Quick Recap We've talked before about how transparency data isn't always as transparent as it sounds but here's a refresher of why it can be challenging to create the complete view of the data: - **File Inflation** - Some payers publish massive files filled with inflated provider lists that include non-contracted entities, adding volume but not value, and making the files harder to process. Aetna and Anthem Elevance are textbook examples of this. - **Temporary access windows** - Files are sometimes hosted behind APIs with download limits or expiration windows, making it difficult to access everything in time. This is an approach UnitedHealthcare takes among others. - **Non-descriptive plan names** - Plans labeled with vague or unrecognizable names can be overlooked unless a system is in place to retrieve and examine every file, regardless of how it's labeled. - **Inconsistent file mapping and buried rates** - Different health plans point to different file sets. Some overlap, others contain unique data. Without capturing and parsing everything, critical pieces can be missed. ### Why Complete Healthcare Price Transparency Data Is Non-Negotiable So yes, while accessing healthcare price transparency data can be challenging, what's often overlooked is the absolute importance of getting the most detailed and comprehensive view possible. Whether you're advising a provider on a contract renewal, benchmarking rates across markets, or trying to understand how a payer's network structure has changed, having all the granular data is foundational. Missing even one set of files, or failing to associate it properly with the right health plan, can mean overlooking entire reimbursement structures or excluding payer-provider arrangements that are critical to the bigger picture. Here's why completeness matters: - **Contractual visibility and alignment** - Knowing every rate that is associated with each health plan and provider group allows your team to clearly understand contract terms, uncover hidden rate structures, and anticipate negotiation leverage points. Knowing what's in the data (and what's missing) affects your leverage at the negotiation table. - **Risk reduction** - Incomplete data can lead to assumptions that don't hold up under scrutiny, creating risk for your organization or clients. - **Operational efficiency** - Cleaner, more complete data reduces the need for manual follow-ups, rework, or reliance on anecdotal evidence. - **Historical context** - Being able to trace how rates and relationships have changed over time can reveal patterns, disruptions, or opportunities for improvement. Put simply, the more complete your data, the better your decisions. And in today's climate, precision is a competitive advantage. ## What a Complete Approach Looks Like The good news is that this is possible by following a framework with a few key principles: - **All files, every time** - Every transparency file from every payer must be captured, regardless of whether the health plan name looks meaningful at first glance. Every file represents a potential set of unique contract terms. - **Full parsing and matching** - Files need to be deeply parsed, flattened, and matched back to health plans in a structured, consistent way. This is especially true for JSON files with nested structures that mask key data. Every plan type, including employers, should be accessed and parsed and mapped appropriately for use in analysis. - **Data validation and cleanup** - Irregularities like broken links, mislabeled plan IDs, or non-compliant formats need to be flagged and resolved wherever possible to avoid misinterpretation. - **Historical access** - The ability to see past versions of data, not just current snapshots, provides essential context for historical trends and network changes. This enables retrospective analysis that supports smarter forecasting. - **Self-service usability** - All of this must be made accessible to analysts, strategists, and managed care professionals without requiring heavy engineering support. That means intuitive interfaces, searchability, and the ability to filter by attributes such as provider, plan, or rate attribute. All of these capabilities add up to more than technical best practices. They represent the core infrastructure required to make price transparency truly actionable. ## Payerset is the Platform Built for These Needs We've built our platform from the ground up to meet these needs. Every piece of our technology stack is designed to support full data access, ease of use, and real-time decision-making. - We collect all files from every payer and TPA that's compliant with the federal Transparency in Coverage rule. - We associate rates back to their correct health plans, even when plan names are vague or inconsistent. - We ensure representation across more than 300 carriers and third-party administrators, including both national brands and regionals. - Our longitudinal archive gives users the ability to trace changes over time, which is especially important when providers are added or dropped, or when contract terms change with little notice. With **Rate Explorer**, business users can query and analyze pricing structures via an intuitive self-service portal. No coding or data prep required. For data and analytics teams, our **Data Lake** product provides structured, historical files ready for integration into BI platforms or internal tools. We also offer robust data quality management, ensuring your team isn't spending hours cleaning or reconciling files manually. ## Who This Is For Our platform is built for professionals who need precision, speed, and flexibility: managed care experts, provider strategy leaders, healthcare finance analysts and consultants, revenue cycle consultants, and advisory firms all use our platform to do work that depends on nuance and completeness. These users don't just need a general idea of rate levels or averages. They need specifics: at the CPT code level, across multiple plans and geographies, historically and in real time. When your work influences contract terms, network participation, strategic growth, or reimbursement modeling, you can't afford to miss a data point. And the tools you use must be as thorough and reliable as the work you deliver. --- ## The Positive Future of Price Transparency in the U.S. in 2025 - URL: https://payerset.com/post/the-positive-future-of-price-transparency-in-the-u-s-in-2025/ - Published: February 26, 2025 - Author: Jacob Little - Section: Industry Insights *This post was originally published on February 26, 2025, and updated on August 27, 2025.* On February 25, 2025, President Trump signed his [second executive order regarding price transparency](https://www.whitehouse.gov/presidential-actions/2025/02/making-america-healthy-again-by-empowering-patients-with-clear-accurate-and-actionable-healthcare-pricing-information/). The executive order is titled "Making America Healthy Again by Empowering Patients with Clear, Accurate, and Actionable Healthcare Pricing Information." Below we cover the background his new executive order builds on, challenges we've overcome as an industry and ones that still remain, as well as outline the path forward to ensure the positive impact these new regulations can help create for the healthcare landscape. We'll update this post throughout the year as healthcare price transparency continues to evolve. ## Foundation laid for price transparency This new order builds upon Executive Order 13877, issued on June 24, 2019, titled ["Improving Price and Quality Transparency in American Healthcare to Put Patients First."](https://trumpwhitehouse.archives.gov/presidential-actions/executive-order-improving-price-quality-transparency-american-healthcare-put-patients-first/) This regulation was a paradigm shift, requiring hospitals and health plans to provide meaningful price information to the public. Specifically, it mandated: - **Hospitals** to maintain a consumer-friendly display of pricing information for shoppable services and [provide a machine-readable file (MRF) listing negotiated rates for all services](/post/making-sense-of-hospital-price-transparency-data/). - **Health plans** to publish their negotiated rates with providers, their out-of-network payments, and the actual prices paid for prescription drugs. - **Health plans** to maintain a consumer-facing tool that allows individuals to access price information. This was a bold and necessary step toward healthcare and hospital price transparency. ## Barriers to implementation and enforcement Despite the intent of these regulations, implementation faced several challenges. The data published by payers was often: - **Infrequently updated**, resulting in missing or incomplete information. - **Low quality**, with issues such as duplicate records, inconsistent naming, and non-standard billing classifications. - **Difficult to access**, perhaps the biggest obstacle. Machine-readable files (MRFs) were often intentionally complex, making extraction, normalization, and usability a significant challenge. As an industry, we have made significant progress in bringing the promised vision to reality yet still there's so much to be done. As a price transparency company, we are frequently asked: "What will the Trump administration do this time around to make this better?" While we were confident that this administration would continue supporting price transparency, we were uncertain about specific priorities. However, on February 25, 2025, we were excited and relieved to see that the administration is fully committed to advancing transparency. ## The 2025 Executive Order: A renewed focus on price transparency As stated in [Section 3 of the executive order](https://www.whitehouse.gov/presidential-actions/2025/02/making-america-healthy-again-by-empowering-patients-with-clear-accurate-and-actionable-healthcare-pricing-information/), titled "Fulfilling the Promise of Radical Transparency," the Secretary of the Treasury, Secretary of Labor, and Secretary of Health and Human Services are now required to take all necessary actions to: - Enforce existing healthcare price transparency regulations. - Within 90 days, mandate the disclosure of actual prices of services rather than estimates. - Issue updated guidance to ensure that pricing data is standardized and easily comparable across hospitals and health plans. - Update enforcement policies to ensure [complete, accurate, and meaningful data reporting.](/post/why-complete-healthcare-price-transparency-is-essential-and-what-it-takes-to-get-it-right/) Sections B and C of the order are particularly critical, as they address major data challenges that have plagued price transparency since 2022. ## What are the price transparency challenges that must be addressed? We live and breathe this data every day and while price transparency laws have led to progress, several persistent issues must still be resolved. ### 1. Conflicting rates in machine-readable files (MRFs) Many MRFs list multiple rates for the same provider and service within the same plan but lack the necessary details to clarify which rate applies. This becomes especially problematic in rental networks, such as those used by Blue Cross Blue Shield, where the same provider appears under different contract structures. One example of this is a provider is listed multiple times under the same plan with different rates, leading to confusion and reduced trust in the data. There are some particularly poor payers when it comes to publishing conflicting rates but on a positive note, United Healthcare made major improvements in 2023 by reducing conflicting rates, but the issue is not fully resolved. ### 2. "Zombie Rates" (Ghost Rates) Some MRFs contain clinically implausible rates, meaning a provider is listed for services they have never billed for and likely never will. While transparency laws must ensure all contractually covered rates are disclosed, better data refinement strategies are needed to avoid unnecessary data bloat. An example of this could be pediatricians listed with rates for hip replacement surgeries or hospitals listing rates for treatments they have never provided. ### 3. Barriers to accessing data Many organizations lack the technical infrastructure to process the massive datasets contained in MRFs. Some insurance carriers submit multiple files for the same network with nearly identical data, creating redundancy and inflating file sizes. **File Size Issues Across Payers:** - **Elevance (Anthem)** have some files that exceed 1 terabyte when uncompressed and contain over 10 billion records per file when fully processed. - **Aetna** files often range from several hundred gigabytes across many of their employer health plans. - **United Healthcare** files, when uncompressed, are typically around 100 gigabytes. - Some payers submit multiple MRFs for the same network, adding to unnecessary data duplication. The sheer size and complexity of these files make it impossible for most organizations to access and analyze the data effectively without specialized technology. ### 4. Poor data retention policies Many payers do not retain historical MRFs, making it impossible to verify past rates for billing disputes. Even if historical data is retained, changes in schema & structure are rarely documented. These limited time windows can have very real consequences - reduced auditability, lack of accountability of payers & less negotiation leverage for care organizations. At Payerset, we store all historical MRFs indefinitely, but this should be standard practice performed by the carriers posting these files. Arguably, this could even be centralized by CMS for single source access and better auditability. ### 5. The problem of "Percent of Charges" contracts Many contracts express prices as a percentage of charges, rather than providing a fixed dollar amount. This makes it impossible to determine the real cost until after a procedure is billed, reducing price transparency. A common scenario is a contract that states Procedure X is reimbursed at 75% of charges. However, without knowing the provider's billed charge, there is no way to estimate the cost. While hospital price transparency data helps bridge this gap, it does not cover all healthcare settings, making true price comparison more challenging. ### 6. Expiring file links and API rate limits Many payers provide MRFs through public APIs, but these APIs have rate limitations that prevent full data downloads before links expire. Some payers even intentionally limit the amount of time current files are accessible when they are published with short download expiration windows. We overcome this by deploying a distributed computing approach that downloads files in parallel before they expire. However, this should not be necessary. ## A step in the right direction: CMS Schema 2.0 for Transparency in Coverage (TiC) A lot of exciting updates have happened over the past several months with one of those changes being a new FAQ related to "Schema 2.0" released by CMS. Schema 2.0 sets out to solve some of the challenges with the initial implementation of the TiC Act. A few of the highlights we're excited about are much clearer direction on provider groupings to help reduce file sizes in many cases and increase usability, increased standardization with place of service and service codes, required Table of Contents, and more. [We dive deep in to these upcoming changes in a Q&A with our co-founder and CTO here.](/post/transparency-in-coverage-schema-2-0/) ## Moving forward: A renewed commitment to healthcare price transparency We have worked diligently for years to clean, transform, and simplify this data to help customers realize the intended value of these regulations. However, these challenges should not exist and they are not in the spirit of the law. The executive order earlier this year indicates a turning point. We now have the opportunity to accelerate progress, raise the standard for data quality, and ensure that price transparency delivers on its promise. We are on a mission to: - Democratize healthcare pricing. - Make price transparency real, accessible & truly transparent as it should be. - Work side by side with partners, customers & industry stakeholders to create a transparent, fair and equitable healthcare market. Here's to 2025 and beyond! --- ## Making Sense of Hospital Price Transparency Data: 2025 Updates & Solutions - URL: https://payerset.com/post/making-sense-of-hospital-price-transparency-data/ - Published: February 23, 2025 - Author: Joseph Tollison - Section: Industry Insights *This blog was originally published on February 23, 2025 and updated on September 10, 2025* Hospital price transparency data has come a long way since its messy early days. But even with 2025 regulations, inconsistencies still make analysis challenging. In this post, we break down the current state of hospital machine-readable files (MRFs), the latest updates, and how Payerset simplifies the process. [Click here for direct links to each Hospital MRF by State](https://docs.payerset.com/hospital-transparency/mrf-links-by-state) ## The State of Hospital MRF Data Unlike the Transparency in Coverage (TiC) rule, which applies to insurance carriers, hospital price transparency regulations are a separate initiative with different requirements, schemas, and implementation timelines. When hospital price transparency requirements were first introduced, the lack of standardization made meaningful analysis nearly impossible. Hospitals published data in different structures, with no consistency in file formats, terminology, or coding methodologies. Some of the most notable challenges included: - **Inconsistent File Formats** – No unified schema for reporting, making data difficult to compare - **Limited Field Utility** – Missing or vague pricing fields made apples-to-apples comparisons difficult - **Lack of Cross-Referencing** – Theoretically, hospital-posted prices should match payer-posted prices, but discrepancies were common - **Disorganized File Hosting** – No centralized or predictable locations for file access Was this lack of consistency intentional obfuscation or just poor implementation? The reality is likely a mix of both, compounded by resource-constrained hospital IT teams. ## 2024-2025 Hospital Price Transparency Data Rule Updates ### July 2024: Standard Charges Format Implementation To improve data consistency, the July 1, 2024, regulations introduced a standardized format, requiring hospitals to publish: - **JSON Schema** – A structured, machine-readable format for improved parsing. - **Wide-Form CSV Format** – A more accessible but still structured alternative. ### January 2025: Enhanced Accessibility and Data Accuracy Starting in January 2025, additional measures were implemented to improve usability and compliance: - **Increased Accessibility** – Hospitals must prominently display links to their MRFs in website footers. - **Affirmation of Data Accuracy** – Hospitals must attest that their posted data is complete and correct. - **New Data Elements:** - Estimated Allowed Amounts – Projected pricing for services. - Drug Unit Measurement Standardization – Making National Drug Code (NDC) comparisons easier. The Centers for Medicare & Medicaid Services (CMS) [provides a detailed breakdown](https://www.cms.gov/newsroom/fact-sheets/hospital-price-transparency-fact-sheet) of the Hospital Price Transparency Rule, including the latest regulatory updates effective July 1, 2024. Similarly, the American Hospital Association (AHA) [discusses how hospitals are implementing these new requirements](https://www.aha.org/news/headline/2024-07-01-new-hospital-price-transparency-requirements-take-effect). These updates were significant steps forward, but they didn't entirely solve the challenges of normalizing hospital price data for analysis. ## May 2025 Changes to Hospital Price Transparency Guidance [On May 22, 2025, CMS issued](https://www.cms.gov/files/document/updated-hpt-guidance-encoding-allowed-amounts.pdf) updates regarding Hospital Price Transparency Guidance. The key change is that new guidance for encoding allowed amounts. In short, CMS is closing the "loophole" of placeholders and requiring real dollar values so that hospital transparency files are more consistent and useful. Here's a summary of the changes that occurred in May. **Dollar Amounts Required**: Hospitals must encode payer-specific negotiated charges as actual dollar amounts in machine-readable files (MRFs), whenever they can be calculated (e.g., negotiated base rate, case rate, per diem, or percentage of a known fee schedule). **No More "999999999"**: Hospitals should stop encoding nine 9s as a placeholder for "estimated allowed amounts." CMS found this was overused and made the data less useful. **Definition of "Estimated Allowed Amount"**: Must represent the average dollar amount historically received from a third-party payer for an item/service. **How to Calculate** (must use prior 12 months of electronic remittance advice (ERA/835) data): - If the negotiated algorithm/percentage applied for only part of the year, report the average dollar amount for that period only. - If the item/service was provided at least one time in the prior 12 months, report the average of those paid amounts, and note "one or more instances in the prior 12 months." - If the item/service was not provided in prior 12 months, encode an expected dollar value, and note "zero instances in prior 12 months." **Documentation in Notes Field**: Hospitals must add clarifying notes in the MRF to indicate whether there were zero, one, or more instances in the prior 12 months when reporting estimated allowed amounts. ## Ongoing Challenges in Hospital Pricing Data Despite improved formatting and regulatory oversight, several challenges persist that got in the way of hospital pricing data standardization. These are the three hurdles to overcome. ### 1. Payer Name and Plan Name Inconsistencies Different hospitals refer to the same payer in multiple ways like: - UnitedHealthcare might appear as "UHC," "United," or "UnitedHealthcare." - Cigna could also be listed as "LifeSource" for transplant networks. - Blue Cross Blue Shield (BCBS) variations make it difficult to determine the exact plan. ### 2. Billing Code Variability - Some hospitals use a single billing code for a procedure (e.g., one CPT code for a colonoscopy). - Others list multiple billing codes, each with slightly different pricing structures. - There's no uniform approach, making it hard to determine whether differences stem from contract negotiation, billing methodology, or simple misclassification. ### 3. Slow Adoption of New Compliance Measures - Hospitals are only required to update MRFs once per year, meaning outdated formats linger. - Many hospitals are still catching up on compliance, delaying the effectiveness of new regulations. Despite regulatory improvements, compliance remains a major issue. [According to a report from the Office of Inspector General (OIG)](https://oig.hhs.gov/reports/all/2024/not-all-selected-hospitals-complied-with-the-hospital-price-transparency-rule/), a significant percentage of hospitals have yet to fully comply with the transparency rule. Additionally, [a Patient Rights Advocate report found that compliance among hospitals has actually declined,](https://www.healthcaredive.com/news/hospital-price-transparency-continues-drop-patient-rights-advocate/733703/) highlighting ongoing inconsistencies in hospital-reported pricing. ## How Payerset Solves These Challenges We take a human-first approach to organizing, simplifying, and making hospital price transparency data more actionable and accessible. **1. Payer Name & Plan Name Normalization**: We standardize payer names and plan names so that they are consistent across all hospital files. This allows for easy comparison across hospitals and alignment with payer-posted data. **2. Billing Code Categorization**: We map hospital billing codes to categorized, easy-to-understand procedure groups. This helps remove noise from the data and ensures proper comparability across providers. **3. Compliance Tracking & Continuous Monitoring**: We track hospitals' compliance with regulations and update our datasets accordingly. As hospitals gradually align with the new standards, we incorporate their latest data for accuracy. **4. Seamless Integration with Payer Data**: By linking hospital-posted data with Transparency in Coverage payer data, we provide a holistic view of healthcare pricing. This allows better benchmarking and removal of outliers to enhance pricing insights. Hospital price transparency is improving, but significant challenges remain. Payerset makes it easy to work with hospital and payer data, eliminating inconsistencies and enabling smarter analysis. --- ## How Payerset Simplifies Healthcare Plan Complexity in Reporting - URL: https://payerset.com/post/how-payerset-simplifies-healthcare-plan-complexity-in-reporting/ - Published: February 21, 2025 - Author: Jacob Little - Section: Industry Insights ## The Complexity of Reporting Plans & Why It Matters When it comes to healthcare price transparency, one of the biggest challenges users face is navigating reporting plans: the structured data sets that insurance carriers use to define pricing. These plans represent different insurance products, such as PPOs, HMOs, and EPOs, but they go far beyond the broad categories that most people recognize. Each insurance carrier structures their pricing data differently, and reporting plans are fragmented into multiple categories, including examples like: - **Standard commercial plans** – The widely recognized plans available through insurers. - **Exchange plans** – Those available on the Affordable Care Act marketplace. - **Employer-sponsored plans** – Customized plans that large companies negotiate, often with unique pricing structures. ## Challenges Accessing Insights Today Many price transparency platforms require users to select these reporting plan(s) before they can access a subset of pricing data. While this might seem like a logical way to organize information, it actually creates unnecessary complexity and friction for users. Why? - Reporting plan names are often obscure, highly technical, and inconsistent. - Selecting the wrong plan can exclude critical data and lead to inaccurate comparisons. - Depth of the analysis is inherently limited with this reduced scope. Forcing users to choose upfront process is time-consuming, fragmented, and often leads to incomplete or misleading comparisons. Not to mention, maybe you want to see the variability across common categories of plans for each payer but have no way of doing that without immense manual intervention. ## Payerset's Approach: Complete Flexibility & Data Accuracy Payerset takes a different approach. Instead of forcing users into predefined selections, we maximize flexibility by automatically collecting, categorizing, and mapping all available reporting plan data. Our process ensures that: - We collect and process every file from every carrier. Nothing gets left out. - We automatically categorize and map plans to recognizable names and categories to eliminate confusion. - Users can compare rates across multiple payers without needing to pre-select a plan. This means that when users search for a procedure like knee surgery, they instantly see all relevant pricing data across all applicable reporting plans, organized coherently for easy analysis, without having to make complex selections first. ## How does this look in the real-world? Imagine you're a hospital administrator evaluating reimbursement rates for a procedure. With traditional platforms, you might have to dig through multiple files, selecting different plans manually, just to piece together a full comparison. With Payerset, the process is seamless: 1. Search for the procedure(s), provider(s), and Payer(s) 2. Instantly view rates across all relevant plans, automatically categorized and mapped for trusted analysis. No need to limit scope upfront. 3. Add additional ad-hoc descriptive details such as billing code modifiers, place of service, TIN value, and much more within the same view to enrich your analysis. ## Holistic View of Reporting Plan This approach ensures you never miss critical pricing insights while making analysis faster, easier, and more accurate. ## The Bottom Line: Holistic Analysis Leads to Better Outcomes Payerset's mission is to make healthcare price transparency simple, accurate, and actionable. By eliminating the burden of pre-selecting reporting plans, we provide users with a more intuitive, comprehensive, and insightful experience. With more accuracy, less frustration, and better decision-making, Payerset is the ultimate tool for anyone looking to analyze healthcare costs effectively. Experience the easiest way to compare healthcare pricing: try Payerset today. --- ## Payerset and PurpleLab Partner to Deliver Trusted Price & Coverage Intelligence, Transforming Healthcare Decision-Making - URL: https://payerset.com/post/payerset-and-purplelab-partner-to-deliver-trusted-price-coverage-intelligence-transforming-health/ - Published: February 13, 2025 - Author: Joseph Tollison - Section: News Payerset, the industry leader in enterprise price transparency data, and PurpleLab, a leading health tech company specializing in real-world data and medical claims insights, announced today a strategic partnership to launch a trusted price intelligence solution suite, setting a new standard in healthcare intelligence. This collaboration empowers healthcare organizations with unparalleled accuracy and actionable insights, enabling smarter, data-driven decisions that drive better outcomes. PurpleLab, dedicated to advancing healthcare pricing transparency, also integrated Lime Tree Health's comprehensive hospital price transparency data into its platform earlier this year. By merging these powerful datasets from Lime Tree Health and Payerset with one of the US's largest medical and pharmaceutical claims databases, PurpleLab now delivers an unmatched, 360-degree view of the healthcare payer and provider landscape. The trusted price intelligence solution will provide a holistic view of healthcare prices across providers, payers, and geographies. Health organizations will be able to determine the true cost of any service, from any provider, in any location, backed by validated data. This partnership will deliver critical insights into payer coverage policies, helping stakeholders understand their impact on patient access and affordability. Additionally, it offers actionable intelligence by uncovering historical pricing trends, allowing to predict future shifts, and enabling proactive cost management. By providing easily accessible price transparency, the solution suite will be invaluable for: - **Health Systems:** Improve revenue cycle management by informing contract and negotiation strategies, refining financial forecasting, budgeting, and resource allocation. - **Payers:** Refine payment models, develop competitive benefits packages, and negotiate fair reimbursement rates. - **Pharmaceutical Companies:** Inform market access strategies, support value-based pricing models, and demonstrate the economic value of their products. - **Clinical Care Organizations:** Make informed treatment decisions, guide patients toward cost-effective care options, and improve care coordination. "This partnership marks a significant milestone in our mission to deliver actionable healthcare intelligence," said Mark Brosso, CEO of PurpleLab. "By integrating Lime Tree Health's pioneering hospital pricing data into our platform alongside Payerset's industry-leading price transparency capabilities, we're setting the stage to make pricing intelligence accessible and actionable for everyone in healthcare." Since 2018, PurpleLab has rapidly become the trusted partner for comprehensive healthcare data and analytics. Their [HealthNexus](https://purplelab.com/platform/) platform aggregates over 50 billion medical and pharmaceutical claims from a diverse network of over 20 sources. This massive dataset, encompassing 330+ million patient lives and 2.3 million healthcare providers, delivers unparalleled insights into patient journeys, treatment patterns, and clinical outcomes, enabling data-driven decisions that improve healthcare delivery. "We see this partnership as an important milestone in reshaping healthcare pricing," said Jacob Little, CCO at Payerset. "Our goal is to deliver the transparency that creates fairness across the entire healthcare ecosystem, and teaming up with PurpleLab will help us achieve that vision." Payerset offers insights that transform how health systems, software vendors, consulting firms, and other stakeholders understand and manage healthcare pricing. Their proprietary technology continually processes and stores every machine-readable file (MRF) posted by insurance companies, amassing over 10 trillion records of contracted rates per quarter. This comprehensive and constantly updated dataset offers a historical and current view of pricing trends, enabling in-depth analysis of cost variations and contract performance. --- ## Unlocking the Power of Historical Price Transparency Data - URL: https://payerset.com/post/unlocking-the-power-of-historical-price-transparency-data/ - Published: January 23, 2025 - Author: Jerry DiMaso - Section: Industry Insights ## Overview of Use Cases for Historical Price Transparency Accessing and understanding historical price transparency data has always been a challenge. The sheer volume and complexity make it difficult to track trends, identify patterns, and detect anomalies over time. This often leads to decision-making without the full picture. Customers wrestle with this by manually piecing together old statements, email threads, and scattered public data, an inefficient and time-consuming process. Worse, these methods often were forced to rely on incomplete or inaccurate information. To solve this, we're introducing the Date Snapshot feature. This new tool simplifies historical rate analysis, giving users access to past pricing data to navigate healthcare costs with greater confidence. Users can select specific timeframes when creating fee schedules or rate comparisons. ## How Can Historical Price Transparency Data Improve Outcomes? **Leverage Historical Rate Data**: Access to past negotiated rates helps users bring concrete data to the table, strengthening their position in pricing discussions with payers and providers. This eliminates reliance on estimates or assumptions. **Identify Areas for Rate Reductions**: Analyzing rate changes over time can reveal unnecessary increases or significant price fluctuations, providing leverage to negotiate more favorable terms. **Benchmark Against Industry Standards**: Comparing current negotiated rates with historical market trends helps organizations determine competitiveness and adjust contracts accordingly. **Spot Unfavorable Contract Terms**: Users can identify past instances where negotiated rates were unusually high or misaligned with industry norms, ensuring future contracts are more balanced and fair. ## Get Started Payerset customers already have access to this feature within the Fee Schedule and Rate Comparison tools. And we're just getting started. More enhancements are on the way! --- ## Reflecting on 2024 and What's Next for Payerset - URL: https://payerset.com/post/2024-reflection-look-ahead/ - Published: January 14, 2025 - Author: Jerry DiMaso - Section: Industry Insights When we started Payerset, our goal was ambitious: making the immensely complex and often inaccessible data surrounding price transparency available to everyone. We're talking trillions of rows of data from every hospital system, payer, and NPI across the country. It's a monumental challenge, but it's also one of the most important ones to solve for the future of healthcare. Over the past year, we've made incredible strides. We spent many long nights improving the underlying engine to process the massive (and often intentionally over-complicated MRF data) published by payers, launched a new version of the Payerset platform into the world, took part in the HFMA (Healthcare Financial Management Association), National Price Transparency, and the HLTH conferences, and even launched our [Payerset podcast](/insights/categories/payercast/)! Beyond these accomplishments, however, we have learned so much and met so many fantastic people like [Cynthia Fisher](https://www.patientrightsadvocate.org/about-staff), [Dr. Marion Couch](https://www.linkedin.com/in/marion-couch-872ab3a6/), [Mark Brosso](https://www.linkedin.com/in/mark-brosso-73861b5/), [Alex Goolsby](https://www.linkedin.com/in/wgoolsby/), [Ron Urwongse](https://www.linkedin.com/in/rurwongse/), [Aneesh Chopra](https://www.linkedin.com/in/apchopra/), and countless others. Each step deeper into the world of healthcare price transparency has reinforced why we're doing this and how much potential there is to make a difference. The deeper we dig, the more energized we become. ## Bringing Healthcare Pricing Intelligence to Everyone As we move into 2025, we're continuing to build on making price transparency data accessible to everyone. We're incorporating more data than ever before to deepen our insights and expand our capabilities. However, we don't want to stop at simply serving up the data. We've spent a couple of decades in data & analytics and know in our core that moving from simply being able to access data to intelligently making decisions and driving outcomes is where impact is maximized. Payerset has been at the forefront of making transparency data accessible. Our vision, however, goes far beyond simply accessibility. To truly maximize our impact on the healthcare landscape, our aim is to empower everyone throughout the value chain with complete Pricing Intelligence. We want data to not only be readily accessible, but easily understandable and actionable. Next-generation pricing intelligence involves incorporating new data domains (Claims, anyone?), exploring ways to prescribe actions to take in order to improve outcomes, specialized tools for particular use cases, historical data to create a holistic picture, and much more. ## What's Right Around the Corner? Looking ahead, there's so much we're excited about. One of the first, and most visible ways, we're evolving is with a complete refresh of our platform. We've redesigned the user interface to make it even more intuitive and powerful for our users. But this update isn't just about aesthetics; it's about laying the groundwork for new types of analysis and use cases that will empower our customers to uncover insights they couldn't access before. You'll also see some more detailed announcements over the following weeks. We've released to our community the ability to view how rates have changed over time to enable a slew of new use cases, incorporating Provider data with an interactive new explorer, enhanced our Rate Comparison explorer, along with much more. We'll also be teasing some upcoming innovations as well. ## Thank You To our customers, partners, team, and community: thank you for being part of this journey so far. We've accomplished so much together in a short amount of time, and we're only just getting started. Here's to another year of learning, building, and making healthcare pricing a little more transparent for everyone. --- ## Exploring Price Transparency, Accountability, and Innovation in Healthcare with Andrew Gordon - URL: https://payerset.com/post/exploring-price-transparency-accountability-and-innovation-in-healthcare-with-andrew-gordon/ - Published: December 5, 2024 - Author: Joseph Tollison - Section: Payercast Healthcare price transparency has become a pivotal topic in the industry, and our recent Payercast episode featured Andrew Gordon, a social worker turned health economics researcher, who is helping shape the conversation around this critical issue. Here's a recap of the highlights, key insights, and lessons learned from our dynamic discussion. > "Transparency unlocks accountability. With better information, we can hold stakeholders accountable for fair pricing and quality care." - Andrew Gordon ## A Journey Fueled by Curiosity Andrew's path into healthcare research began with personal curiosity. Frustrated by an unclear $700 bill for an MRI, Andrew dove deep into the world of healthcare finance, seeking to understand billing practices, negotiated rates, and the systemic issues that complicate transparency. His commitment led him to engage with schedulers, coders, and billers to unravel the complexities of healthcare pricing. This hands-on approach highlighted both the human side of the system and its technological gaps. ## What is Price Transparency? Andrew defines price transparency as the patient's ability to know their exact out-of-pocket costs for healthcare services before they receive them. This patient-centric perspective acknowledges the critical need for clarity in a system where bills are often unintelligible and unexpected charges can be financially devastating. While elective procedures lend themselves more easily to transparency, emergency scenarios present unique challenges. ## Barriers to Transparency During our discussion, Andrew shared insights on why transparency remains a significant challenge: - **Technological Lag:** Many healthcare systems are burdened by outdated technology and siloed data, making it difficult to deliver accurate estimates. - **Complex Contracts:** Negotiated rates between payers and providers vary widely due to factors like service volume, site of care, and contractual carve-outs. - **Operational Overload:** Hospitals face competing priorities, from staffing shortages to EMR implementations, which often push transparency efforts down the list. - **Public Misconceptions:** Transparency can lead to patient confusion or mistrust, as seen in cases where itemized bills create more questions than answers. ## A Hopeful Shift: Accountability and Alignment Transparency, as Andrew notes, unlocks accountability. With more information available, stakeholders including patients and employers can advocate for fairer rates and better care. Employers, in particular, are emerging as powerful players in this space, leveraging data to push for direct-to-provider arrangements that cut costs and improve outcomes for employees. ## The Future of Healthcare Pricing Our conversation touched on the potential for transformative change in the industry: - **Disruption through Technology:** Innovations like AI and advanced analytics could streamline pricing processes and enhance transparency. - **Direct-to-Employer Models:** Employers are increasingly bypassing traditional insurance arrangements and partnering directly with providers to reduce costs. - **Independent Care Models:** Physicians and small organizations are exploring subscription-based care and other models to sidestep insurance complexities. Andrew's optimism is grounded in the progress being made but tempered by the recognition that systemic change takes time. The key is collaboration across stakeholders and a commitment to aligning incentives in ways that prioritize the patient. ## Personal Development Insights In addition to his professional expertise, Andrew shared a valuable personal development tip: create environments of psychological safety. Whether in healthcare or any other field, fostering open dialogue and encouraging diverse perspectives can lead to better solutions and stronger relationships. ## Final Thoughts Andrew Gordon's dedication to understanding and improving the healthcare system is both inspiring and instructive. His ability to connect the dots between research, policy, and practice highlights the importance of curiosity, humility, and collaboration in driving meaningful change. We are excited about the momentum in healthcare price transparency and grateful to have leaders like Andrew pushing the conversation forward. Stay tuned for more episodes of Payercast as we continue to explore the future of transparency, accountability, and innovation in healthcare. --- ## Reflections from the Georgia HIMSS Conference: Driving Digital Transformation in Healthcare - URL: https://payerset.com/post/reflections-from-the-georgia-himss-conference-driving-digital-transformation-in-healthcare/ - Published: October 3, 2024 - Author: Joseph Tollison - Section: Industry Insights The annual Georgia HIMSS conference brought together leaders and innovators from across the healthcare landscape, and this year's event did not disappoint. With strategic learning tracks covering cybersecurity, artificial intelligence (AI), and digital transformation, the conference offered practical insights into how healthcare organizations (HCOs) in Georgia can adapt and thrive in an increasingly digital world. ## Insights from the Digital Transformation Track I had the opportunity to attend the digital transformation (IT) track, which was packed with engaging sessions and interactive panels. We heard from experts representing major Georgia-based healthcare organizations like Grady Health System, Shepherd Center, and the Georgia Hospital Association. One theme stood out: success in digital transformation is not just about implementing technology; it's about empowering people. ### Key Takeaways **Change Management is Critical:** One of the most impactful discussions centered on the importance of change management, a concept often overshadowed by project management. Valerie emphasized the importance of focusing on the end state and outcomes for people, not just checking boxes on training or processes. It's about ensuring that teams are equipped to succeed, a point echoed by many speakers. **Business Cases and Leadership Buy-In:** In one of the panels, speakers like Steven McWilliams and Murry Ford discussed how to make strong business cases for technology investments within healthcare organizations. They highlighted that the key to success is inspiring teams and addressing barriers to adoption, whether it's bridging generational gaps in the workforce or making tough decisions during crises like Hurricane Helene. ## Learning from Real-World Challenges The impact of Hurricane Helene loomed large over many conversations. Several hospitals across the Southeast, including those in Georgia, had to revert to using paper records during the storm. This situation served as a stark reminder of what truly matters in healthcare technology: the people and processes behind it. While technology can streamline operations and improve outcomes, the crisis revealed that when it comes down to it, what really counts is how quickly and effectively teams can adapt, even without the "bells and whistles" of high-tech systems. **The People Factor:** Murry Ford, now overseeing revenue at Grady, brought a unique perspective as someone who transitioned from an IT role to a business leadership position. His insight into the prioritization of initiatives showed that focusing on outcomes and cross-functional alignment is critical to navigating the complex healthcare environment. ## Balancing Regulatory Compliance and Innovation Another topic discussed at length was the tension between regulatory compliance and the speed of digital transformation. Industry experts, including Sepi Browning and Jeff Morrison, shared their experiences with improving patient care while navigating the challenges of regulatory requirements. Although these regulations often slow the pace of change, they also serve as a forcing function, aligning teams around a shared goal. As Todd Schlesinger pointed out, once mandates are in place, the ability to execute is clear, it's just a matter of prioritization and leadership. ## Conclusion The Georgia HIMSS conference was a great reminder of the incredible culture and people who are the connective tissue of healthcare in this state. From interactive discussions on digital transformation to insights on crisis management and compliance, the event highlighted that healthcare's future depends not just on technology but on the people who make it work. As we continue to innovate, we must remember that true transformation happens when we empower our teams, prioritize the patient experience, and execute with purpose. I'm already looking forward to next year's Georgia HIMSS event. Until then, let's keep building a stronger, more connected healthcare community in Georgia. --- ## Payercast S01 E03 - Price Transparency Use Cases, HFMA 2024, Late Adopters or Sitting Ducks? - URL: https://payerset.com/post/payercast-s01-e03-price-transparency-use-cases-hfma-2024-late-adopters-or-sitting-ducks/ - Published: August 26, 2024 - Author: Jacob Little - Section: Payercast **Podcast Title:** Key Price Transparency Use Cases, HFMA 2024, Late Adopters or Sitting Ducks? **Season 1, Episode 3** ## Overview In this episode of Payercast, the Payerset team explores how health insurance carriers are proactively reducing reimbursements to hospitals by leveraging price transparency MRF files from other carriers. We dive into the core and most successful use cases for price transparency data and share PT success stories from the 2024 HFMA conference. Tune in to learn more about the evolving landscape of healthcare reimbursement and price transparency. ## Featured Topics ### Use Cases for Price Transparency Data in Healthcare The conversation delved into various use cases for health plan price transparency data, particularly focusing on the contractual rates between providers and carriers. Price transparency is increasingly becoming a valuable tool for healthcare organizations and payers alike, as the industry adapts to using this data more strategically. Below are some key takeaways. ### Bi-Directional Rate Benchmarking and Negotiation **Key Insight:** One of the most common uses of price transparency data is benchmarking reimbursement rates. Healthcare organizations use this data to understand how their rates compare to similar providers in their area. This allows for more informed negotiations with payers. For instance, a hospital can compare its reimbursement rates by billing code to neighboring facilities with similar demographics, clinicians, and market power, leading to more competitive negotiations. However, the insurance carriers are also using the data, sometimes in reverse. Hospitals have received letters from large health insurance companies pointing out that the hospital is being reimbursed at a higher rate than competitors and suggesting reductions based on the transparency data. This puts healthcare organizations on the defensive, making it critical for them to be proactive in their use of this information. **Actionable Insight:** Healthcare organizations must adopt a proactive approach to rate negotiation using this data, or risk being caught off-guard when payers leverage it against them. Understanding how payers are using this data can help prevent significant revenue loss. ### Market Expansion with Price Transparency Data **Key Insight:** The second significant use case discussed was market expansion. Larger health systems are using transparency data to strategically expand their services beyond their current geographic regions. For example, a hospital in Florida might look to expand into Tennessee, or a multi-specialty practice in one state may seek to acquire a practice in another. By analyzing publicly available rates, organizations can assess market dynamics and reimbursement rates in regions where they don't yet have a relationship with insurers. This data provides a foundation for understanding what rates are common and how they can position themselves for market entry. **Actionable Insight:** Market expansion decisions can be more informed and strategic when leveraging this data. Organizations can avoid blindly entering a new market by first gaining visibility into the prevailing rates and reimbursement structures. ### Underpayment Analysis and Claim Filling Gaps **Key Insight:** Another emerging use case involves using the data as a backstop for revenue cycle management. Underpayment analysis allows health systems to catch gaps in revenue more quickly by automating the detection of discrepancies between expected payments and actual payments received. **Actionable Insight:** By incorporating price transparency data into their revenue cycle processes, healthcare organizations can improve the speed and accuracy of underpayment detection, enhancing financial performance and reducing the revenue loss associated with claim underpayments. ## Case Study: UofL Health Leads the Way in Price Transparency Utilization At the HFMA annual conference, UofL Health in Kentucky was highlighted as an example of a health system successfully leveraging price transparency data. They were able to extract and analyze data from a large payer, Anthem Elevance, and used it in their negotiations. As a result, they secured significant reimbursement increases across 20 DRGs (Diagnosis-Related Groups), which is forecasted to improve their EBITDA by 3-4% over the next year. **Key Takeaway:** Proactively adopting price transparency data can yield significant financial benefits, as demonstrated by UofL Health. Other healthcare systems can follow suit by collaborating with cross-functional teams and technology departments to analyze data and use it in negotiations. ## Conclusion The podcast emphasized the importance of price transparency in transforming healthcare organizations' negotiation strategies, market expansion efforts, and revenue cycle management. Proactive organizations are already using this data to increase revenues and strengthen their negotiation positions. However, those who ignore it risk becoming "sitting ducks" when payers come knocking. Now is the time for healthcare systems to embrace price transparency and use it to their advantage. With the rising use of price transparency data across the industry, both proactive adoption and strategic application are essential. Those who prepare now will be better equipped to handle the new dynamics in healthcare pricing and reimbursement. --- ## Contract Negotiation Powered by Price Transparency Data: A Success Story from UofL Health - URL: https://payerset.com/post/contract-negotiation-powered-by-price-transparency-uoflsuccess/ - Published: June 29, 2024 - Author: Jacob Little - Section: Industry Insights Our hats off to the UofL team, Abraham Gage and Michael Venable, for being change agents and jumping into payer price transparency data early. They wrote the code, got the servers, and focused on getting this data and turning it into millions in annual savings. This is the vision of price transparency. Rebalancing the asymmetrical nature of healthcare pricing in this country by simply saying, "Hey, you are not giving me the fair rate in these specific areas based on your contract data that you published." One very important note: while the UofL team impressively parsed the payer price transparency data on their own, parsing and cleaning the data is a continually evolving challenge with the data and payer restrictions changing monthly. If you don't have the time or focus to get this information, you don't have to do it on your own. We provide a super easy-to-use portal where you can simply search any care delivery organization, health insurance carrier, and category of services (or specific billing code) and get all of the rate data you need returned in seconds. ## Key Outcomes from UofL Health's Initiative Using payer sourced price transparency data, UofL achieved a 33% increase in reimbursement for spine fusion procedures with MCC. ### Significant Increases in Reimbursement Rates The use of price transparency data allowed UofL Health to secure strategic increases in reimbursement rates for various services. For example, they achieved a 33% increase in reimbursement for spine fusion procedures with MCC (Major Complications or Comorbidities). The overall percentage increase in rates from September 2023 to May 2024 was substantial for several services, indicating a successful negotiation process driven by the insights gained from the transparency data. ### Enhanced Negotiating Position Access to competitors' pricing data across multiple geographies provided UofL Health with a robust foundation to negotiate better rates. This transparency empowered the health system to avoid accepting lower rates and instead push for rates that reflect the market value of their services. "The system is doing what the system should be doing, ensuring that the codes that are going to be generated yield a material return," highlighted the strategic advantage gained through detailed market intelligence. ### Strategic Decision-Making The transparency data informed UofL Health's market entry decisions and initial contract settings. This was particularly evident in their decision to establish a standalone imaging center to retain patients within their system and prevent them from being redirected to lower-cost providers by insurers. The data also helped UofL Health to avoid catastrophic disasters in M&A and joint ventures, ensuring better-informed decisions. ### Validation and Accuracy Ensuring the accuracy and reliability of the data was a critical step in the process. The team cross-verified the extracted data with internal claims and revenue cycle data, as well as corroborated findings with trusted partners. This meticulous validation process helped avoid pitfalls and ensured that the negotiation strategies were based on accurate and comprehensive data. "Extracting value from TiC data takes effort and patience," emphasized the need for a dedicated approach to harness the full potential of transparency data. ### Future Expectations The team anticipates ongoing evolution in payer behavior and additional guidance from CMS. They expect that payers will continue to balance compliance with transparency requirements and protection of shareholder value. The presentation underscores the importance of incorporating transparency data into the broader analytics portfolio to continuously identify and respond to market opportunities and threats. ## Why Payer Transparency Matters UofL Health's success story underscores the transformative potential of payer transparency data in leveling the playing field in healthcare pricing. By accessing and utilizing this data, healthcare providers can negotiate fairer rates, make informed strategic decisions, and ultimately improve their financial health. At Payerset, we recognize that not every organization has the resources or expertise to navigate the complexities of payer transparency data. That's why we offer a user-friendly portal that simplifies this process. With our platform, you can quickly and easily access the rate data you need, empowering your contract negotiation. Regardless of whether you opt for our solution, a competitor's, or decide to tackle it on your own, TAKE ACTION! Given the ease of accessing this data, it is quickly becoming negligent to ignore. --- ## Payercast S01 E02 - Recapping The 2024 National Healthcare Price Transparency Conference - URL: https://payerset.com/post/payercast-s01-e02-recapping-the-2024-national-healthcare-price-transparency-conference/ - Published: May 24, 2024 - Author: Joseph Tollison - Section: Payercast **Podcast Title:** Recapping The 2024 National Healthcare Price Transparency Conference **Season 1, Episode 2** ## Overview The Payerset team was a proud sponsor of the National Healthcare Price Transparency Conference (NHPTC) this year. We learned so much and met so many incredible people that are making a real difference in U.S. healthcare. The conference was praised for its impactful discussions on healthcare financials, engaging expert panels, and the overall event organization. The key themes revolved around the necessity for data transparency, accountability in healthcare pricing, and strategies for employers to manage healthcare costs effectively. ## Featured Topics ### Event Experience - The conference had a welcoming atmosphere with around 700 total guests, including 200 in-person attendees. - The event was well-organized with high-quality virtual content available for free. - Attendees appreciated the opportunity to access all presentation decks and virtual content seamlessly. ### Panel Discussions Two panels were highlighted: one focused on market strategies and the other on policy and employer responsibility in managing healthcare costs. Experts from various sectors, including employers, providers, and consultants, shared their insights on improving healthcare financials. ## Detailed Overview ### 1. Market Strategies for Data Utilization **Key Takeaway:** Employers have a fiduciary responsibility to understand and manage healthcare costs, as these expenses significantly impact their bottom line and employees' wages. **Actionable Insights:** - Employers must obtain and analyze data to combat issues like double billing and fraud. - Direct contracting with care delivery organizations is becoming more feasible and can lead to substantial savings. - Examples: Purdue University saved $25 million over five years by effectively managing healthcare costs. ### Policies to Increase Transparency - **Price Transparency:** Highlighted the importance of making pricing information accessible to promote competition and accountability. - **Data Transparency:** Emphasized the need for comprehensive data analysis to understand and improve cost structures. - **Quality Transparency:** Stressed the importance of correlating quality metrics with pricing to ensure value in healthcare services. - **Ownership Transparency:** Discussed the complex corporate structures of healthcare organizations and the need for clarity in ownership and financial operations. - **PE Influence:** Noted that private equity firms' involvement in healthcare often indicates a broken market that is fixable for profit. ### Employer Responsibility and Accountability - **Fiduciary Duty:** Employers are responsible for ensuring that their healthcare spending is efficient and effective. - **Negotiation and Cost Management:** Highlighted the importance of negotiating better rates and understanding high-volume procedures to manage costs. - **Case Study:** A healthcare organization managed to significantly reduce costs by switching providers, showing the impact of informed decision-making. ## Key Speakers and Takeaways ### Chris Whaley (Brown University) - **Insight:** Proved that healthcare organizations can break even or profit with efficient operations. - **Analysis:** Showed how rising hospital prices drive overall spending growth, using data from the Bureau of Labor Statistics. ### Marilyn Bartlett (CPA) - **Ownership Transparency:** Provided insights into the complex corporate structures of healthcare organizations. - **Call to Action:** Encouraged understanding the true cost of care delivery and improving operational efficiencies. ### Sean Grimminger - **PE Firms in Healthcare:** Explained that private equity firms enter broken markets for profit, indicating areas for potential improvement. ## Conference Highlights ### Sage Transparency 2.0 A new tool released at the conference, Sage Transparency 2.0, offers comprehensive data on healthcare pricing and quality metrics. The live demo, led by Gloria Sachdev, showcased the tool's capabilities in an interactive format. ### Legislative Support Noted the bipartisan support for healthcare price transparency, with legislation spearheaded by figures like Senator Braun and Bernie Sanders. Emphasized the importance of continued legislative efforts to improve healthcare transparency and accountability. ## Conclusion The National Price Transparency Conference provided valuable insights into healthcare financials, emphasizing the importance of data transparency, employer accountability, and strategic management of healthcare costs. With expert panels, practical examples, and new tools like Sage Transparency 2.0, the conference underscored the necessity for informed decision-making in the healthcare sector. The overarching message was clear: transparency drives competition and efficiency, ultimately benefiting both employers and employees in managing healthcare costs. --- ## National Healthcare Price Transparency Conference Recap - URL: https://payerset.com/post/national-healthcare-price-transparency-conference-recap/ - Published: May 15, 2024 - Author: Joseph Tollison - Section: Industry Insights The National Healthcare Price Transparency Conference, held on May 13, 2024, was a significant event bringing together industry leaders, healthcare professionals, and policymakers to discuss the critical issues of healthcare pricing and transparency. Hosted by prominent figures like Gloria Sachdev, Cynthia Fisher, and Mark Cuban, the conference delved into various facets of healthcare costs, price transparency, and the impact of these elements on employers, employees, and the broader healthcare system. If you didn't attend, please make sure you do next year. It will be well worth it if you care about price transparency in healthcare. For those who were not able to attend, my aim is to capture the essential points from each session, highlighting key insights and actionable takeaways. ## Cynthia Fisher Keynote **Topic: Empowering Patients and Employers through Price Transparency** Cynthia Fisher, founder of PatientRightsAdvocate.org, emphasized the need for accessible, upfront healthcare pricing to create a functional and competitive market. She shared impactful stories, like that of Cindy Reddy from Colorado, who faced financial ruin due to a surprise medical bill, and how transparency helped remedy the situation. Fisher highlighted the success of states like Colorado and Florida, where transparency laws have led to significant savings for employers and improved healthcare access for employees. She stressed the importance of compliance, noting that only 34.5% of hospitals are fully compliant with transparency regulations. Fisher advocated for stronger enforcement and state-level actions to ensure broader compliance and consumer protection. **Key Takeaways:** - Price transparency empowers patients to avoid overcharges and financial hardship. - Employers can leverage transparent pricing to negotiate better deals and reduce healthcare costs. - Stronger state laws and enforcement are crucial for achieving comprehensive price transparency. ## Mark Cuban Keynote **Topic: Revolutionizing Drug Pricing with Transparency** Mark Cuban, through his initiative Cost Plus Drugs, aims to disrupt the opaque pharmaceutical pricing system. Cuban discussed the inefficiencies and lack of transparency in drug pricing, sharing his company's approach of displaying costs, markups, and final prices openly. He criticized the traditional pharmacy benefit managers (PBMs) and advocated for employers to demand transparency in contracts. Cuban highlighted the benefits of direct contracting and the importance of employers owning their data to make informed decisions. **Key Takeaways:** - Transparency in drug pricing can lead to significant savings and fairer prices. - Employers should demand transparent contracts from PBMs and insurance companies. - Direct contracting and owning healthcare data are essential strategies for cost management. ## Chris Whaley - RAND 5.0 Study **Topic: The Impact of Price Transparency on Healthcare Costs** Chris Whaley presented the findings from the RAND 5.0 study, which examined hospital prices and the variability across states. The study revealed that employers pay significantly more than Medicare for the same services, with substantial variation not explained by quality or cost differences. Whaley emphasized the fiduciary responsibility of employers to ensure efficient use of healthcare dollars and highlighted lawsuits against companies failing to meet these obligations. **Key Takeaways:** - Employers pay, on average, 254% of what Medicare pays for hospital services. - There is significant price variation across states and hospitals, not linked to quality. - Employers have a fiduciary obligation to manage healthcare costs effectively. ![National Healthcare Price Transparency Conference](/images/blog/national-healthcare-price-transparency-conference-recap/inline-1.webp) ## Session Highlights - **Price Transparency Success Stories:** Examples from states like Colorado and Indiana where transparency laws have led to substantial savings and improved healthcare access. Real-life cases of patients avoiding overcharges through access to transparent pricing. - **Technological Innovations:** Development of tools by tech developers in states with robust transparency laws to facilitate healthcare shopping for consumers. Potential for future apps allowing patients to compare prices and quality, similar to airline ticketing systems. - **Employer Strategies:** Case studies of companies like Harris Rosen's hotels and school districts in Florida saving millions through direct contracting and transparent pricing. Recommendations for employers to audit healthcare spending and renegotiate contracts based on transparent pricing data. - **Policy and Enforcement:** Discussion on the slow enforcement of federal transparency laws and the need for state-level actions to protect consumers. Bipartisan support for price transparency laws and the potential for future legislative changes to enhance compliance and enforcement. ## Conclusion The National Healthcare Price Transparency Conference underscored the critical role of price transparency in transforming the healthcare market. By empowering patients, enabling employers to manage costs effectively, and fostering competition, transparent pricing can lead to significant improvements in healthcare affordability and access. As Payerset continues to democratize price transparency data, these insights and actionable steps from the conference will be invaluable in driving our mission forward. --- ## Payercast S01 E01 - Reviewing Price Transparency Rules and Exploring a Machine Readable File (MRF) - URL: https://payerset.com/post/payercast-s01-e01-reviewing-price-transparency-rules-and-exploring-a-machine-readable-file-mrf/ - Published: May 4, 2024 - Author: Joseph Tollison - Section: Payercast **Podcast Title:** Reviewing Price Transparency Rules and Exploring a Machine Readable File (MRF) **Season 1, Episode 1** ## Overview In Payerset's debut Payercast episode, we provide an in-depth exploration of healthcare price transparency, discussing the mandates for data disclosure, the structure of the data, and the practical applications for using this data effectively. ## Featured Topics ### The Price Transparency Mandate The discussion begins by outlining the federal mandates that require both hospitals and payers to make their reimbursement rates public. This initiative, spearheaded by CMS along with the Department of Health and Human Services (HHS) and the Department of Treasury, aims to increase transparency in healthcare pricing to enable better decision-making by consumers and other stakeholders. The mandate covers a wide array of healthcare services and requires that detailed data on negotiated rates be published in an accessible manner. The intent is to make healthcare costs more predictable and to empower consumers to make more informed choices. ### What Does a Machine-Readable File Look Like? The podcast goes into detail about the structure and content of the machine-readable files (MRFs) that contain the data released under the price transparency rules. #### Table of Contents The Table of Contents (TOC) file is discussed as a crucial element of the MRFs. It acts as an index that guides users to various data files related to specific healthcare plans. The TOC lists all the files a payer has published, which contain the negotiated rates and allowed amounts. This file helps users navigate the complex structure of healthcare data, linking directly to the in-depth data files that contain the specific rate information. #### In-Network File The podcast then explores what an in-network file looks like, detailing how it contains information about reimbursement rates for services provided within a network. These files are extensive and include details such as provider identifiers, service codes, and the corresponding negotiated rates. The structure of these files is designed to facilitate the extraction of specific data points but requires specialized tools and understanding due to the complexity and volume of the data. ### How Can These Files Be Used? The practical applications of the data contained within these files are extensively discussed. The hosts explain how analysts and healthcare organizations can use the data to: - **Analyze Pricing Variations:** By comparing rates across different providers and regions, stakeholders can identify pricing disparities and opportunities for cost reduction. - **Strategic Planning:** Organizations can use detailed rate information for better contract negotiations and to optimize their service offerings based on competitive pricing. - **Compliance and Reporting:** Ensuring that pricing strategies comply with regulatory requirements and using the data for mandatory reporting purposes. - **Market Analysis:** Companies can perform detailed market analyses to understand the competitive landscape, helping them make informed decisions about where to allocate resources. The podcast emphasizes the transformative potential of price transparency in healthcare, predicting that increased access to pricing data will lead to more competitive pricing structures and potentially lower healthcare costs overall. The detailed walkthrough of data files and discussion on their practical uses provide a comprehensive guide for stakeholders looking to leverage this new wave of data transparency in the healthcare industry. --- ## Price Transparency Q1 2024 Update: Strides Forward and the Road Ahead - URL: https://payerset.com/post/price-transparency-q1-2024-update-strides-forward-and-the-road-ahead/ - Published: April 7, 2024 - Author: Thomas Miller - Section: Industry Insights As the first quarter of 2024 unfolds, we find ourselves navigating through an evolving landscape of price transparency. The commitment to enhancing the quality and availability of healthcare price information has yielded notable progress, alongside continued challenges. Here's a snapshot of where we stand: ## Enhanced Data Quality and Compliance The effort to publish valid, accurate data has seen considerable advancements. More payers are now delivering on their obligation to provide clear and comprehensive price transparency data. This improvement, however, is not uniform. While many are making genuine strides, a handful remain behind. Our observations suggest these discrepancies are less about reluctance and more about the technical and operational challenges involved. It's a journey that requires time, investment, and skill development, emphasizing the need for continued support and resources in this arena. ## Innovative Use Cases Emerging Our clients are at the forefront of translating this wealth of data into actionable insights. The ingenuity on display is remarkable, ranging from integrating payer data with Medicare information and claims volumes to better target negotiation efforts, to constructing detailed fee schedules for hospitals as a starting point for the new MRF requirements. These applications are opening new avenues for strategic decision-making and growth for institutional and professional healthcare organizations alike. ## Looking Forward The journey towards full price transparency is ongoing, marked by significant achievements and persistent challenges. The developments in early 2024 underscore a collective commitment to this goal, alongside a recognition of the hurdles that still lie ahead. As we continue to navigate these waters, the promise of price transparency to transform healthcare remains clear and compelling. We remain dedicated to pushing the boundaries of what's possible with price transparency data, supporting our clients in leveraging this information to drive strategic growth and operational excellence. Stay tuned for more updates as we continue to advance this important work. --- ## Navigating the Landscape of Oncology Diagnostic Pricing in the U.S. Northeast - URL: https://payerset.com/post/navigating-the-landscape-of-oncology-diagnostic-pricing-in-the-u-s-northeast/ - Published: April 4, 2024 - Author: Joseph Tollison - Section: Industry Insights The cost of cancer treatment in the United States is a pressing concern for patients, healthcare providers, and insurance companies alike. With the mandate from CMS (Centers for Medicare & Medicaid Services) on health plan price transparency, a new era of data availability promises a window into the previously opaque world of healthcare pricing. This post delves into an insightful study that uses the vast datasets provided by Payerset to shed light on the price variation for oncology diagnostics in the Northeastern U.S. ## The Critical Role of Cancer Diagnostics Cancer diagnostics play a pivotal role in the early detection, accurate diagnosis, and the formulation of personalized treatment plans. Technologies like mRNA diagnostics have revolutionized the way treatments are selected, offering hope for more effective and less invasive treatments. However, the cost of these diagnostic procedures can vary significantly, creating a labyrinth of pricing that patients and providers must navigate. ## The Study: A Deep Dive into Oncology Diagnostic Pricing Leveraging the "Cancer Diagnostics Negotiated Rates – Payerset Price Transparency" dataset, this study analyzes the contracted rates posted by major health insurers, focusing on providers specializing in oncology in the Northeast United States. The study zeroes in on the billing codes for key oncology diagnostics, including breast and prostate mRNA and gynecologic live tumor cell culture diagnostics. ## Conclusion: Empowering Providers with Price Transparency This study exemplifies how health plan price transparency data can be a powerful tool for healthcare providers. By understanding the landscape of negotiated rates, providers can enter negotiations armed with data, aiming to secure fair reimbursement rates that reflect the value of their services. As the healthcare industry continues to grapple with cost containment and value-based care, initiatives like this study not only illuminate the path towards more equitable pricing but also underscore the importance of transparency in fostering a sustainable healthcare ecosystem. --- ## Locations for Health Plan Transparency in Coverage Machine Readable Files Now Publicly Documented - URL: https://payerset.com/post/locations-for-health-plan-transparency-in-coverage-machine-readable-files-now-publicly-documented/ - Published: January 28, 2024 - Author: Joseph Tollison - Section: Parsing Payer MRFs Due to the Transparency in Coverage rules for health plans that began in July 2022, health insurance companies have been required to post their In-Network Rates for all covered items and services between the health plan and in-network providers. This includes both individual providers and organizations. Payerset has addressed numerous challenges in parsing these files. We've removed duplications, filtered out irrelevant services (since payers list rates for a service and provider even if the provider would never perform that service), and selected relevant health plans, thereby reducing noise and size, and making the data more accessible and insightful. An example of such an irrelevant service could be orthopedic surgery rates listed for a drama therapist. Another significant challenge, and the focus of this post, is the difficulty in locating the Machine Readable Files (MRFs) themselves. Often, they were not easily found or necessarily linked on the insurance companies' websites. To address this, we are now documenting the location of all MRFs in our public documentation at [docs.payerset.com](http://docs.payerset.com). Our goal is to enhance transparency compliance, as some health insurance companies have been remiss in posting their MRFs. Additionally, we hope this will serve as a valuable public resource for anyone interested in health plan price transparency. For regular updates and to access this vital information, check out our documentation with MRF locations. --- ## Uncovering the Future of Price Transparency: A 2023 Recap and 2024 Outlook - URL: https://payerset.com/post/uncovering-the-future-of-price-transparency-a-2023-recap-and-2024-outlook/ - Published: January 6, 2024 - Author: Joseph Tollison - Section: Industry Insights ## Price Transparency 2023 Recap As we step into 2024, it marks the third year of public health plan price transparency data being available. Reflecting on the past year, I would like to share some price transparency observations and learnings that we've gathered in 2023. ## Catalyzing Strategic Growth The year 2023 stood out as a pivotal moment for major health systems, including Northwell Health and Prisma Health, in utilizing Payerset's solutions for price transparency. The engagement of these health systems in using this data marks a significant market trend, especially considering that the early adopters of price transparency were primarily health tech, healthcare consulting, and actuarial firms. We haven't reached widespread democratization of price transparency yet, but there's evident progress in the right direction. Our customers are beginning to realize tangible benefits from the newfound financial clarity they have across markets and their peers. The data we provide has been instrumental for these organizations, supporting effective negotiations and strategic planning. Our solutions have been critical, whether it's in the context of payer negotiations, managing health systems, or offering consulting services. They have played a key role in fostering revenue growth and informed strategic decision-making. ## Significant Progress in Compliance and Data Accuracy The journey through 2023 was critical for achieving compliance in health plan price transparency. Our rigorous audit of every Machine-Readable File (MRF) from each payer revealed significant advancements: - **UnitedHealthcare's Full Compliance:** Achieved in August 2023, UnitedHealthcare addressed earlier discrepancies in their rate structures, providing clarity on actual rates. - **Improved Accessibility and Reliability:** The year saw a substantial improvement in the accessibility and reliability of large payers' MRF data. Issues like corrupted or inaccessible files, prevalent early in the year, were effectively resolved. - **Expanding Data Sets:** A testament to data completeness and continued growth is Aetna's files, which increased from 5,038 in August to 5,395 by November. This expansion reflects a richer repository of providers, rates, and codes. The highlight of the year was our ability to accurately link active contracted rates to the penny for major health systems in states like New York, Tennessee, Texas, Kentucky, Utah, and Indiana. This level of precision challenges the misconception that price transparency data is either unwieldy or inaccurate. ## 2024: A Year of Practical Application and Expansion The focus for 2024 is set to shift towards the practical application of this data. We anticipate innovative use cases emerging as early adopters integrate this valuable data into their operational workflows. Moreover, we expect a broader spectrum of organizations to begin leveraging this data, driving their strategic plans. The road ahead is filled with opportunities, and we at Payerset remain committed to our journey of democratizing price transparency data in healthcare. Looking forward to an impactful and transformative year! --- ## Peeling Back the Layers of Health Plan Price Transparency: A Journey Towards Democratized Data - URL: https://payerset.com/post/peeling-back-the-layers-of-health-plan-price-transparency-a-journey-towards-democratized-data/ - Published: November 20, 2023 - Author: Joseph Tollison - Section: Industry Insights Today, I'm sharing my thoughts on price transparency in healthcare, a topic that holds promise for making healthcare more affordable. The idea of making things open and clear to spread power and increase wealth isn't new. It's seen in how personal computers came about, and in the foundation of capitalist and democratic societies. I speak for our team at Payerset, who work with price transparency data daily, and from what we see, it's going to be a long ride. But, there's hope, as we're already seeing some positive changes on the horizon. When you first hear about price transparency data, it might sound like a way to peek into the secret deals on rates between payers and healthcare providers. And yes, the rates for the same services often vary a lot. But as we dig into this data, we find there's much more to be uncovered, things we didn't think of at the start of this journey to open up this information. **One big eye-opener is the messiness and complexity of the contracts themselves.** Our dive into the data shows that through messy deals or company mergers, there's no simple relationship between an organization (like Baylor Scott and White) and their rates for services. Usually, it's more like a puzzle. One organization, under one tax ID, with many provider IDs tied to that tax ID, and then multiple contracts tied to various provider IDs (contracts and rates might even be tied to small or unexpected facilities). And then, you need to piece it together because different billing codes are tied to different provider IDs. The mix of different negotiated rate types tied to facilities where you wouldn't expect them adds to the complexity. On top of this, we still see issues with payers meeting the rules. Just last week, we found a big payer missing major provider IDs in their data, flagged what was wrong, and opened a ticket with CMS. The customers we work with, who have been part of contract negotiations for years, confirm that **this messy picture actually reflects the real situation out there.** On the outpatient clinic side, it's interesting to see rates tied to individual providers. In one case, a single tax ID had 436 providers tied to it. What our customers might find is that this data is just duplicated over and over. We see many examples of "rate stuffing" where a payer will just copy the same rates under the provider IDs for the same tax ID. This is a way for the payer to follow the law, while making the data so big that it becomes almost impossible to work through and analyze (unless you are Payerset, of course). Seeing the complexity of these contracts in the industry has been a big part of understanding price transparency. Some organizations have everything under one contract while others have many contracts tied to different provider IDs. All this confusion is going to come into the light. What's important now is getting this information to people who understand contracts well, actuaries who understand rates well, and organizations like accounting firms and other healthcare consultants who want to use this information to help their clients. Like I said, it's going to be a long journey, but we're already seeing early movers and healthcare experts holding payers accountable for these messy and inaccurate contracts, and the big variations in service rates. Change is on the way! It's going to take a lot of hard work. But Payerset will open up this information and get it into as many hands as possible so that they can do good with it. Thank you all for your partnership and dedication to making healthcare better. Thank you for teaming up with us on this journey. Payerset is price transparency, simplified. --- ## November 2023: A Landmark Month in Health Plan Price Transparency - URL: https://payerset.com/post/november-2023-a-landmark-month-in-health-plan-price-transparency/ - Published: November 18, 2023 - Author: Joseph Tollison - Section: Parsing Payer MRFs November brought fascinating developments in the world of health plan price transparency. ## Unprecedented Growth in Data This month, we witnessed more data than we've ever seen before. This wasn't just a marginal increase; we're talking about huge growth. The surge was due to improved compliance, leading to an increase of codes, plans, and an accumulation of hundreds of billions more rows of data. ## Notable Highlights: Elevance and United A significant highlight was Elevance, a payer that has historically struggled with hundreds of corrupted Machine-Readable Files (MRFs). Impressively, they have now achieved a record of zero corrupted files. Meanwhile, United reported an increase of 200 billion rows in their data. ## Challenges Beyond the Surface However, this growth spurt in data brings to light a concerning aspect. The essence of price transparency was envisioned to simplify understanding healthcare costs. Yet, the reality is quite the opposite. Organizations that didn't invest heavily in R&D, teams, and infrastructure a year ago to parse this complex and massive data have now officially fallen behind. ## Elevance and United: A Closer Look As we mentioned before, every single file from Elevance was parsable without any signs of corruption, encompassing 10,105 distinct MRFs. Some individual Elevance files, even when compressed parquet, reached sizes as large as 150 GBs for a 4-field file. To put this in perspective, one such file can contain up to 30 billion rows from just one provider MRF. On the other hand, United had only six files that were unparsable. Two were listed but unavailable, and the other four suffered corruption due to JSON errors, which were rectifiable through our processes. ## Our Mission and Commitment Our proprietary Payer Parse technology easily handles these evolving challenges, including changes in schema and the significant increases in data volume. At Payerset, our mission is to democratize price transparency data. We are committed to continually enhancing our data parsing and storage processes. This commitment is not just about technological advancement; it's about making this data more accessible and affordable. We aim to lower costs and extend these savings to our customers. Let's harness the potential of this data for good. Until our next parsing adventure! --- ## A Turning Tide: How Major Payers are Stepping Up Their Data Game - URL: https://payerset.com/post/a-turning-tide-how-major-payers-are-stepping-up-their-data-game/ - Published: November 13, 2023 - Author: Thomas Miller - Section: Parsing Payer MRFs As we've previously explored on this blog, the landscape of healthcare price transparency is far from uniform. While some payers are more like fortresses with moats and firewalls, others are making strides in becoming veritable libraries of information. Today, we're shining a spotlight on a few industry leaders who are making life easier for everyone in the ecosystem. ## Aetna: The Old Guard Improves Yet Again Aetna has long been at the forefront of providing clean, accessible data. While their files are undeniably massive, they are providing everything required of them by CMS right on their monthly cadence as expected - truly a model in the price transparency space! ## United: A Comeback Story We've got to give credit where credit is due. United has made major progress in ensuring their data is both accessible and parseable. Gone are the days of blocked drives and firewall gymnastics. Today, their JSON files are (mostly) clean and accessible, meeting industry standards and making life that much easier for data engineers and analysts alike. ## Elevance: Growing Pains But Getting There Elevance (formerly Anthem) has been improving their data accessibility and cleanliness, though of the major payers, they are still laggards in terms of ensuring file availability. Recently, they upped the ante by dropping about 3 dozen files that are over 1 terabyte in size, each with more than 20 billion records. To be honest, it threw us for a loop initially, requiring a revamp of our parsing process and some additional compute/memory, but we managed to make it work with just about 30 extra hours of parsing time. ## Size Matters, but So Does Quality What we're seeing across the board is a trend toward not just more data, but better data. While the volumes are shooting up (requiring some extra computational muscle), so is the quality of the information. This isn't just a win for us at Payerset, but for businesses and consumers who can make more informed decisions faster. ## How Payerset Makes It Easier If this talk of terabytes and JSON files sounds intimidating, fret not. Payerset is designed to help you operationalize this ever-growing wealth of data swiftly and efficiently. Our technology leverages cloud computing and cutting-edge parsing algorithms to ensure you're never left in the data dust. The trend is clear: healthcare data is becoming more voluminous, but also cleaner and more useful than ever before. It's an exciting time for anyone invested in the democratization of price transparency data. --- ## Price Transparency Data: A Game-Changer for Health-Tech - URL: https://payerset.com/post/price-transparency-data-a-game-changer-for-health-tech/ - Published: November 6, 2023 - Author: Thomas Miller - Section: Industry Insights In an industry that's notoriously opaque about pricing, the growing trend towards price transparency data is nothing short of revolutionary. But what does this mean for health-tech companies aiming to empower consumers? Well, a lot actually. ## The Problem: Default Rates and Hidden Costs Let's start with a common issue faced by consumers: getting a hospital bill that seems disproportionately high for a procedure that wasn't covered by insurance. Hospitals have a default rate for services, and when insurance doesn't kick in, they bill you at this often-inflated rate. It's like paying the sticker price for a new car without any of the dealer incentives or discounts. ## The Power of Data Here's where price transparency data comes in. By having access to a detailed list of what insurance companies actually pay for procedures, health-tech companies can help consumers negotiate these bills down to a fair rate. This isn't just theoretical; we're seeing this happen in real-time. One company we've been in talks with (whose name must remain confidential for now) is actively using this data to help consumers reduce their hospital bills. ## How It Works Imagine you receive a bill for a procedure that wasn't covered by your insurance. The hospital says you owe them $5,000. With price transparency data, you can see that the negotiated rate between the hospital and insurance companies for that same procedure is typically around $1,500. Armed with this information, debt-relief health-tech companies can help consumers negotiate the bill down to this fair rate. ## The Role of Payerset Here at Payerset, we're making it easier for health-tech companies to tap into this valuable data source. Our platform provides an efficient way to operationalize these large data sets, enabling quicker insights and facilitating direct consumer benefits. ## The Bigger Picture Reducing individual medical bills is just the tip of the iceberg. The applications of price transparency data extend to various facets of healthcare, including identifying the most cost-effective providers for different procedures, creating more personalized insurance plans, and much more. As we see it, we're in the early stages of a significant shift towards more transparent and equitable healthcare. And for health-tech companies looking to make a meaningful impact, the opportunities are endless. --- ## From Data to Decisions: Payerset's Path in Demystifying Price Transparency - URL: https://payerset.com/post/from-data-to-decisions-payerset-s-path-in-demystifying-price-transparency/ - Published: October 24, 2023 - Author: Joseph Tollison - Section: Industry Insights There is a plethora of use cases for price transparency data, and we are merely at the beginning of discovering them all. The diverse perspectives people have when examining this data truly excites me, showcasing a landscape rich with possibilities. The process begins with Step 1: the creation of technology capable of processing and storing all this data swiftly and affordably. Step 2 follows: maintaining a historical record of the industries' prices. We at Payerset have proudly achieved both steps, and now the stage is set to make a substantial impact and demystify price transparency. Here's a glimpse of the feedback and insights we've gathered from our customers and industry conversations regarding the potential benefits of this data. ## Hospital Systems There's immense potential here to effect change rapidly, although the adoption rate might lag. When discussing rate variations, it's critical to also address the varying capabilities of financial leaders within health systems. We've encountered contracting teams well-versed in leveraging this data, adept at holding firm on their rates while making strategic adjustments during payer negotiations. This finesse of balancing potential savings of millions with adjustments in high volume or high-cost services, without becoming a target for payers, is akin to an expert ship captain steering a massive vessel with precision. Conversely, some financial leaders find themselves overwhelmed, akin to a deer caught in headlights, unsure of how to utilize this data. The trailblazers and change agents in this sphere will undoubtedly lay down the path for others to follow, although I ardently wish the pace of this transformation could be accelerated. The prevailing attitudes of fear, risk-aversion, and adherence to the status quo are significant roadblocks to addressing healthcare costs. ## Benefits Navigation Companies These orgs view the data through a distinct lens, developing workflows and automation to enhance provider recommendations and streamline the care journey for their members. With a solid grasp of their member's reporting plans, they aim to navigate rates based on the specific services needed, considering factors like location. This approach starkly contrasts with the rate benchmarking seen in hospital systems. ## Payers They are keen on leveraging this data to proactively engage in discussions with provider organizations and to gain a competitive advantage in RFP scenarios. It's worth noting that major payers have had access to this data or proxy data, which has been their competitive edge for years. ## Specialty Clinics Much like Health Systems, they employ this data to negotiate better rates. Additionally, they explore this data for market expansion, presenting an intriguing use case. --- The insights from these use cases are continually refining our products and services. We are extremely grateful and excited to be on this journey with our customers. Your partnership is invaluable to us. Our mission is to democratize this data, making it accessible to those who can drive positive change with it. Payerset is price transparency, simplified. --- ## The Parse Oscar Goes To... - URL: https://payerset.com/post/the-oscar-goes-to/ - Published: October 23, 2023 - Author: Thomas Miller - Section: Parsing Payer MRFs It was a hard-fought battle with many worthy companies working their hardest to publish their massive negotiated rates data out to the world so they could be in compliance with [Price Transparency laws](https://www.cms.gov/healthplan-price-transparency) by last July. Getting this data together, cleaning it up at scale, and publishing it to the world was no small task, especially when one considers the lengths these companies went to tread the line between compliance and obscurity so that the data was technically available, but virtually unusable. And we get it - if we had to open source our Payerset algorithms, which contain the intellectual property we have built to parse this data, we would probably make it pretty tough to use too. After all, that IP represents thousands of hours of time and many, many dollars invested into our platform to make it what it is today. Still, some of the techniques used by these companies like Elevance, Aetna, United Healthcare, are nothing short of impressive. And we thought that deserved some recognition. So without further ado... ## For Largest Individual Files, the Award Goes To... **Elevance!** Wow, did you have some big files, especially those Provider References and their many permutations, *chef's kiss*. Congratulations on all of your hard work to get your huge data out there! ## For Longest Time to Parse, Award Goes To... **Aetna!** It was neck-and-neck with United up until the last few hours, but you edged them out in the end with an impressive 204 hours of total parsing time. Way to go! ## For Overall Biggest PITA, the Award Goes To... **Humana** - you know what you did, and you should be proud. Your files required the most creative solution to scale parsing your nearly 11 million individual files. Thank goodness for serverless compute! You even managed to pop a random giant Cigna file into your table of contents for some reason, so extra points for that! ## Honorable Mentions Of course, some companies didn't win an award, but we still want to mention payers like Cigna, all the regional Blue Cross payers, and United Healthcare, who came so close on all of the categories. Remember, there's always next month! Well done everyone, congratulations! We look forward to the new challenges we will see now that we have published this blog post and informed these companies that they should change their strategy. --- ## And Then There Was Humana... - URL: https://payerset.com/post/and-then-there-was-humana/ - Published: May 27, 2023 - Author: Joseph Tollison - Section: Parsing Payer MRFs As the quest for price transparency in the healthcare industry continues, as we've discussed before on the blog, there are some insurance companies that fall short in providing open access to their price transparency data. A notable case is Humana, a giant in the health insurance sector. Humana presents its own unique set of challenges when it comes to accessing its price transparency files, hindering efforts for data extraction and analysis. In this blog post, we will delve into the intricate hurdles Humana sets up, thwarting web scraping technologies, and consequently, obstructing data accessibility for consumers and other stakeholders. ## 12... Million... Files Yep, that's right. Humana has provided its price transparency data in the form of nearly 12 million files that can be downloaded from its website. At first glance, this may not seem like that big of a deal, after all, can't computers process millions of files really quickly? Well, in some cases yes, but in most cases, especially when dealing with even relatively small JSON files, the challenges to parsing that data file up fast. Consider each file taking 2 minutes to process and store. That's 12,000,000 minutes = 400,000 hours. That's over 44 years. Not super convenient or helpful, in my opinion. Now of course, computers can process more than one file at a time, but there are conditions that have to be met for that to happen. Without getting too much into the weeds of RAM and compute requirements, each compressed file is ~5 megabytes, uncompressed they range between 30 and 50MB. Most modern PCs have at least 8GB of RAM, so that would equate to processing ~200 files at a time if you were doing nothing else with the computer. Great, we're down to 2,000 hours, or 83 days. **But the files are updated monthly, so by the time you finish, you're already 2 months behind!** This is where we start getting into needing large amounts of RAM and compute to process these files in a reasonable amount of time. Cloud to the rescue! Amazon, Microsoft, and Google (among others like Vultr and Liquid Web) rent high-powered computers by the hour, so we can effectively use these computers to process our code. This gets expensive quickly - the servers that Payerset uses to process the Humana data cost over $7/hour and it still takes a few days running continuously, so it's not cheap. But processing power isn't the only complication... ## Yet Another Web Scraping Challenge ### API Rate Limiting Humana utilizes rate limiting on their developer API, a technique that has many valid reasons for existing, not the least of which is to prevent attacks on systems, but one that also slows down web scraping ventures. This means restricting the number of requests a user can send within a defined period, thereby slowing the pace of data extraction or even bringing it to a standstill. With nearly 12 million files to parse through, rate limiting significantly inflates the time needed to obtain this vast amount of data, presenting a pretty big challenge. ## The Impact on Data Accessibility Humana's use of these mechanisms to foil web scraping and data processing efforts has severe implications on data accessibility for consumers and other stakeholders. By creating hurdles to download their price transparency files, **Humana effectively renders this information inaccessible for virtually all users.** While it may be unintentional, this lack of data accessibility goes against the spirit of data transparency laws which are designed to empower consumers to make informed healthcare decisions and stimulate competition in the industry. Without the ease of access to price transparency data, consumers are left navigating in obscurity, unable to compare costs and make knowledgeable choices regarding their healthcare. This is why we started Payerset - to make this data easier to access for everyone with the hope of reducing the cost of healthcare in the US. --- ## Payerset and Snowflake: Powering Data Transparency in Healthcare - URL: https://payerset.com/post/payerset-and-snowflake-powering-data-transparency-in-healthcare/ - Published: May 27, 2023 - Author: Joseph Tollison - Section: News ## Introduction We are thrilled to announce that Payerset, a pioneering solution for healthcare price transparency, is now officially listed on the Snowflake marketplace. This collaboration aims to make payer price datasets more accessible, fostering improved decision-making processes within the healthcare industry. Access our sample datasets for free in the [Snowflake Marketplace](https://app.snowflake.com/marketplace/listings/Payerset%20LLC). ## Payerset's Solution to an Industry Challenge Data transparency within the healthcare industry is more critical than ever. As we navigate an intricate landscape of costs and services, it is crucial to keep all stakeholders - consumers, health systems, and insurance companies alike - informed and empowered. Payerset simplifies the understanding of payer price datasets by provider, service, and payer, shining a light on a complex industry challenge. The confidential nature of "in-network" pricing agreements between health insurers and providers has been a longstanding norm, upheld by confidentiality stipulations and antitrust rules. However, a groundbreaking shift is underway. The CMS's unprecedented initiative towards health plan price transparency mandates the public revelation of negotiated "in-network" prices shared between healthcare providers and health plans. The introduction of new laws requiring insurance companies to publicly post all negotiated rates with providers for each billing code is a significant move towards data transparency. This shift opens up a myriad of opportunities and benefits for all players within the healthcare ecosystem. ## Benefits of Data Transparency - **Fostering Competition:** Data transparency levels the playing field for healthcare providers. It allows smaller hospitals and providers to negotiate better rates, fostering healthy competition that leads to better services, more affordable prices, and improved patient outcomes. - **Promoting Accountability:** Making pricing and billing information publicly available makes it easier to identify and address instances of significant price variation leading to a more efficient and ethical healthcare system. - **Encouraging Innovation and Collaboration:** As more information becomes available, stakeholders can identify trends, areas for improvement, and new opportunities for growth, fostering the development of innovative products and services. Payerset is excited to be a part of this new wave of innovation. ## Collaboration with Snowflake The partnership between Payerset and Snowflake elevates the importance and impact of data transparency within the healthcare industry. With Payerset's availability on Snowflake's platform, we're providing an accessible and efficient means for stakeholders to utilize and benefit from the price transparency data. This is a game-changer for insurance companies seeking to foster trust, health systems aiming to increase efficiency, and most importantly, consumers making critical healthcare decisions. As we continue to enhance our solutions for an increasingly data-driven healthcare industry, we are excited to invite everyone to experience the benefits of our new collaboration with Snowflake. ## Conclusion The future of healthcare lies in the effective use of transparent data. As we take a giant leap in this direction, we're thrilled to see the transformative impact Payerset will have on improving the healthcare experience for all. We look forward to welcoming you on this journey toward a more open, equitable, and efficient healthcare system. Check out Payerset on the Snowflake marketplace today! --- ## Aetna's Price Transparency & Thwarting Web Scraping to Keep Data Under Wraps - URL: https://payerset.com/post/aetna-s-price-transparency-thwarting-web-scraping-to-keep-data-under-wraps/ - Published: March 2, 2023 - Author: Thomas Miller - Section: Parsing Payer MRFs As the demand for data transparency in the healthcare industry grows, some insurance companies have been less than forthcoming in making their price transparency data easily accessible. Aetna, one of the leading health insurance providers, is an example of a company that has made its price transparency files extremely difficult to download. In this blog post, we will explore the various techniques Aetna employs to block web scraping technologies, hindering data accessibility for consumers and other stakeholders. ## Techniques to Block Web Scraping Technologies ### Limiting Request Rates Aetna has also employed rate limiting to hinder web scraping efforts. By limiting the number of requests a user can make within a specific time frame, the company can effectively slow down or halt the data extraction process. This makes it much more difficult for users to download large amounts of data and significantly increases the time required to obtain the necessary information. ### IP Blocking and User-Agent Analysis To further complicate web scraping efforts, Aetna may use IP blocking and user-agent analysis to identify and block suspicious activity. By analyzing a user's IP address and the information their browser sends to the server, Aetna can identify and block users or bots that exhibit scraping behavior. This adds another layer of difficulty for those attempting to access the price transparency data. ### Obscuring Data Through JavaScript and AJAX Aetna has also been known to obscure its data using JavaScript and AJAX techniques. By dynamically loading content on their web pages, they make it more difficult for web scrapers to locate and extract the desired information. This requires more advanced scraping techniques and additional resources, creating further barriers for users trying to access the data. ## The Impact on Data Accessibility Aetna's efforts to block web scraping technologies have a significant impact on data accessibility for consumers and other stakeholders. By making it difficult to download their price transparency files, Aetna effectively keeps this vital information out of reach for many users. This lack of data accessibility undermines the goals of data transparency laws, which aim to empower consumers to make informed healthcare decisions and foster competition within the industry. Without easy access to price transparency data, consumers are left in the dark, unable to compare costs and make informed choices about their healthcare. Aetna's use of multiple techniques to block web scraping technologies highlights the challenges faced in the pursuit of data transparency in the healthcare industry. While the company may have legitimate reasons for employing these tactics, the overall impact on data accessibility is concerning. To ensure that the goals of data transparency laws are met, it is essential for stakeholders to continue advocating for increased access to information and hold companies like Aetna accountable for their actions. --- ## Anthem Blue Cross Blue Shield's Data Obfuscation: The 180GB Table of Contents - URL: https://payerset.com/post/anthem-blue-cross-blue-shield-s-data-obfuscation-the-180gb-table-of-contents/ - Published: February 10, 2023 - Author: Joseph Tollison - Section: Parsing Payer MRFs As the healthcare industry navigates the complexities of costs and services, data transparency has become an increasingly important aspect. However, not all insurance companies have embraced this change with open arms. In this blog post, we will discuss how Anthem Blue Cross Blue Shield (BCBS) made their table of contents, which is merely a list of files containing price transparency data, over 180GB uncompressed, and the techniques they employed to replicate the same data repeatedly, making it more difficult to crunch and process. ## The 180GB Table of Contents: A Barrier to Data Accessibility Under the new law requiring insurance payers to publicly post their negotiated rates with providers for each billing code, Anthem BCBS has gone to great lengths to create a table of contents that presents a significant challenge for data accessibility. Instead of offering a concise, easy-to-navigate list of files, the company has produced a massive 180GB uncompressed table of contents. This sheer volume of data is overwhelming for most users and requires powerful hardware to process and analyze. By employing this tactic, Anthem BCBS has effectively created a barrier to entry for consumers and other stakeholders who lack the resources to access and understand the information contained within. ## Replicating Data to Obfuscate Information Anthem BCBS's approach to data obfuscation extends beyond the size of its table of contents. The company has also employed techniques to replicate the same data over and over, further complicating the process of extracting meaningful information. This tactic not only increases the overall volume of data but also creates confusion for users attempting to decipher the information. The replication of data can make it challenging to identify the relevant files and extract the desired information. Users must sift through countless duplicates to find the correct data, a task that is both time-consuming and resource-intensive. This deliberate obfuscation serves as an additional barrier, discouraging users from accessing and utilizing the price transparency data. ## Understanding the Implications By creating an unwieldy table of contents and replicating data, Anthem BCBS has effectively limited the accessibility of its price transparency data, despite technically adhering to the new law. This approach raises concerns about the company's commitment to transparency and the potential impact on consumers and other stakeholders. As we've discussed in previous blog posts, data transparency is crucial for empowering consumers to make informed healthcare decisions, fostering competition, and promoting collaboration within the healthcare industry. When companies like Anthem BCBS employ tactics that hinder data accessibility, they undermine these goals and perpetuate existing disparities within the healthcare system. Anthem Blue Cross Blue Shield's approach to data transparency, specifically their 180GB uncompressed table of contents and replication techniques, serves as a cautionary tale within the healthcare industry. As we continue to advocate for increased data transparency, it is vital to remain vigilant and hold companies accountable for their actions. By doing so, we can work towards a more transparent and equitable healthcare system that benefits consumers, health systems, and insurance companies alike. --- ## Navigating the Maze: How Insurance Companies Found Loopholes in Data Transparency Laws - URL: https://payerset.com/post/navigating-the-maze-how-insurance-companies-found-loopholes-in-data-transparency-laws/ - Published: January 3, 2023 - Author: Thomas Miller - Section: Industry Insights In recent years, there has been a growing call for transparency in the healthcare industry, with the aim of increasing competition and empowering consumers to make more informed decisions. One such effort is the new law that requires insurance payers to publicly post all their negotiated rates with providers for each billing code. While the intent behind this law is commendable, the reality is that several insurance companies have found ways to technically adhere to the requirements without providing meaningful access to the data. In this blog post, we will explore how they managed to do this and discuss why they might have chosen this path. ## Circumventing Transparency Requirements It is important to recognize that the law does set certain standards and requirements for insurance companies to follow. However, some insurance payers have reportedly invested significant resources into making the data they publish difficult to access and use. The techniques employed to achieve this include duplicating content millions of times and creating massive JSON files that can only be opened and processed by the most powerful hardware available. As a result, the information becomes virtually inaccessible to the average user. ## Why Insurance Companies Choose This Path While the tactics employed by these insurance companies may seem questionable, it is essential to understand their motivations. The healthcare industry is a complex, high-stakes environment, and companies are driven to protect their interests. By making the data difficult to access, they can maintain a competitive edge and continue to negotiate favorable rates with providers. At the same time, the current system allows these companies to technically comply with the law, thus avoiding penalties and maintaining their public image. The financial incentives and potential consequences of non-compliance are likely significant factors in their decision to skirt the rules. ## The Impact on Consumers and Stakeholders The primary concern with these tactics is the impact they have on consumers and other stakeholders in the healthcare industry. The intended purpose of the law is to promote competition and empower patients to make informed decisions. However, when insurance companies publish unusable data, consumers are left in the dark, unable to compare rates or understand the costs associated with their care. Additionally, this lack of transparency can perpetuate existing disparities within the healthcare system. Smaller providers and hospitals may struggle to negotiate favorable rates without access to the same information as their larger competitors. ## Moving Forward: Encouraging Transparency and Collaboration Although the situation may seem bleak, it is not without hope. It is vital that we, as a society, continue to push for transparency and data accessibility in the healthcare industry. This can be achieved by refining existing legislation, increasing penalties for non-compliance, and promoting the development of user-friendly tools to help consumers navigate the information. Furthermore, fostering collaboration between insurance companies, providers, and regulators is crucial to create a system that is fair and beneficial for all parties involved. Only by working together can we overcome the challenges posed by the current landscape and create a healthcare system that truly serves the needs of its users. The new law requiring insurance companies to publish their negotiated rates is a step in the right direction toward increased transparency in the healthcare industry. However, the tactics employed by some insurance payers to circumvent these requirements highlight the need for ongoing vigilance, collaboration, and refinement. By understanding the motivations behind these actions, we can work towards creating a more transparent and equitable healthcare system for all. --- ## The Power of Data Transparency: Unlocking Benefits for Consumers, Health Systems, and Insurance Companies - URL: https://payerset.com/post/the-power-of-data-transparency-unlocking-benefits-for-consumers-health-systems-and-insurance-comp/ - Published: December 7, 2022 - Author: Thomas Miller - Section: Industry Insights ## The Power of Data Transparency for Payer Pricing Data transparency has become a crucial aspect of the healthcare industry as we navigate the complexities of costs and services in a rapidly evolving landscape. A new law requiring insurance companies to publicly post all of their negotiated rates with providers for each billing code is a significant step towards achieving this goal. In this blog post, we will delve into the importance of data transparency laws and how they can benefit consumers, health systems, and insurance companies alike. ## The Importance of Data Transparency Laws ### Empowering Consumers: Informed Decision-Making Data transparency laws enable consumers to access vital information about healthcare costs and services. With increased access to information, individuals can make informed decisions about their healthcare options, understanding the financial implications of their choices, and seeking out the best value for their specific needs. This level of transparency can ultimately lead to a more engaged and empowered consumer base. ### Fostering Competition: A Fair-Playing Field By requiring insurance companies to disclose their negotiated rates, data transparency laws help level the playing field for healthcare providers. Smaller hospitals and providers can use this information to negotiate better rates and compete with larger institutions more effectively. This healthy competition can lead to better services, more affordable prices, and improved patient outcomes. ### Promoting Accountability and Reducing Fraud Data transparency laws can also play a vital role in promoting accountability and reducing fraud within the healthcare system. By making pricing and billing information publicly available, these laws make it easier for regulators and watchdog organizations to identify and address potential instances of fraud, waste, and abuse. This increased level of oversight can lead to a more efficient and ethical healthcare system. ### Encouraging Innovation and Collaboration Data transparency can also serve as a catalyst for innovation and collaboration within the healthcare industry. As more information becomes available, stakeholders can identify trends, areas for improvement, and new opportunities for growth. This can lead to the development of innovative products and services, as well as collaborative efforts between healthcare providers, insurance companies, and other industry players to improve the overall healthcare experience for consumers. ## How Data Transparency Benefits All Stakeholders ### Benefits for Consumers For consumers, data transparency means having access to essential information about the costs and services associated with their healthcare. This enables them to make informed decisions about their care, leading to better health outcomes and more efficient use of resources. ### Benefits for Health Systems Health systems stand to benefit from data transparency through increased competition and collaboration. With access to pricing and billing information, health systems can identify opportunities for improvement and work together to develop innovative solutions that improve patient care and reduce costs. ### Benefits for Insurance Companies Insurance companies can also benefit from data transparency laws by fostering trust with their customers and maintaining a competitive edge. By providing consumers with clear information about their services and pricing, insurance companies can build trust and brand loyalty. Additionally, transparency can help insurance companies identify areas where they can improve their offerings and better serve their customers. Data transparency laws play a crucial role in promoting fairness, accountability, and innovation within the healthcare industry. By making pricing and billing information publicly available, these laws empower consumers, encourage competition, and foster collaboration between various stakeholders. As we continue to push for increased transparency in the healthcare system, we can look forward to a brighter future where consumers, health systems, and insurance companies all reap the benefits of a more open and equitable system.